Loading...

334 posters, 125 sessions, 831 authors, 236 institutions

ePostersLive by SciGen Technologies S.A. All rights reserved.

4100

Sarcoidosis and 30-Day Perioperative Cardiovascular Complications: A Retrospective Comparative Cohort Analysis
Part of Topic

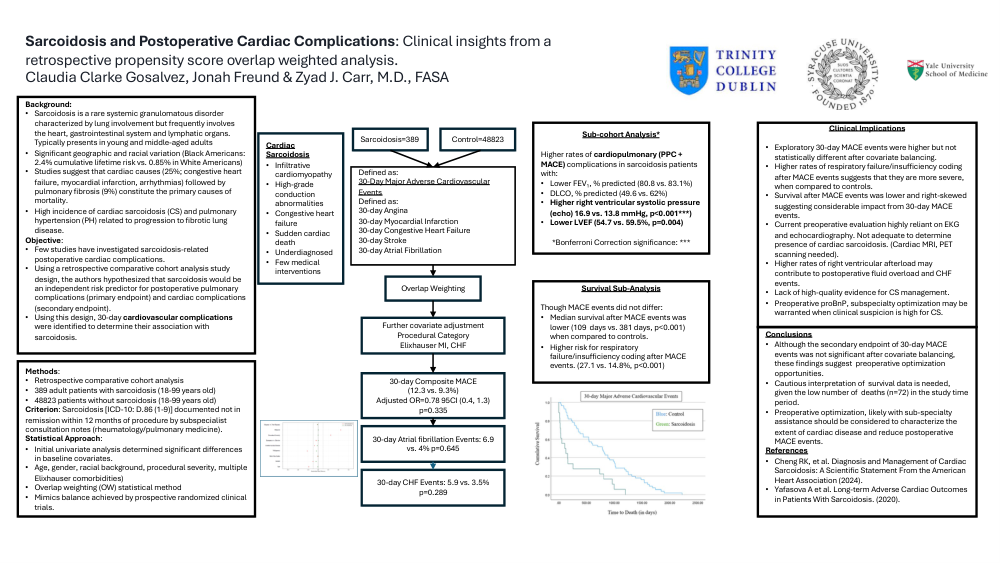
Sarcoidosis and Postoperative Cardiac Complications: Clinical insights from a retrospective propensity score overlap weighted analysis.

Claudia Clarke Gosalvez, Jonah Freund & Zyad J. Carr, M.D., FASA


Background: 

•Sarcoidosis is a rare systemic granulomatous disorder characterized by lung involvement but frequently involves the heart, gastrointestinal system and lymphatic organs. Typically presents in young and middle-aged adults
•Significant geographic and racial variation (Black Americans: 2.4% cumulative lifetime risk vs. 0.85% in White Americans)
•Studies suggest that cardiac causes (25%; congestive heart failure, myocardial infarction, arrhythmias) followed by pulmonary fibrosis (9%) constitute the primary causes of mortality.
•High incidence of cardiac sarcoidosis (CS) and pulmonary hypertension (PH) related to progression to fibrotic lung disease.

Objective: 

•Few studies have investigated sarcoidosis-related postoperative cardiac complications.
•Using a retrospective comparative cohort analysis study design, the authors hypothesized that sarcoidosis would be an independent risk predictor for postoperative pulmonary complications (primary endpoint) and cardiac complications (secondary endpoint). 
•Using this design, 30-day cardiovascular complications were identified to determine their association with sarcoidosis. 

Methods: 

•Retrospective comparative cohort analysis
•389 adult patients with sarcoidosis (18-99 years old)
•48823 patients without sarcoidosis (18-99 years old)

Criterion: Sarcoidosis [ICD-10: D.86 (1-9)] documented not in remission within 12 months of procedure by subspecialist consultation notes (rheumatology/pulmonary medicine).

Statistical Approach: 

•Initial univariate analysis determined significant differences in baseline covariates.
•Age, gender, racial background, procedural severity, multiple Elixhauser comorbidities)
•Overlap weighting (OW) statistical method
•Mimics balance achieved by prospective randomized clinical trials.

Cardiac Sarcoidosis

•Infiltrative cardiomyopathy
•High-grade conduction abnormalities
•Congestive heart failure
•Sudden cardiac death
•Underdiagnosed
•Few medical interventions

Defined as: 

30-Day Major Adverse Cardiovascular Events

Defined as:

30-day Angina 

30-day Myocardial Infarction

30-day Congestive Heart Failure

30-day Stroke

30-day Atrial Fibrillation


Further covariate adjustment

Procedural Category

Elixhauser MI, CHF


30-day Composite MACE

(12.3 vs. 9.3%)

Adjusted OR=0.78 95CI (0.4, 1.3) p=0.335


30-day Atrial fibrillation Events: 6.9 vs. 4% p=0.645


30-day CHF Events: 5.9 vs. 3.5% p=0.289


Sub-cohort Analysis*


Higher rates of cardiopulmonary (PPC + MACE) complications in sarcoidosis patients with:

•Lower FEV1, % predicted (80.8 vs. 83.1%)
•DLCO, % predicted (49.6 vs. 62%)
•Higher right ventricular systolic pressure (echo) 16.9 vs. 13.8 mmHg, p<0.001***)
•Lower LVEF (54.7 vs. 59.5%, p=0.004)


*Bonferroni Correction significance: ***


Survival Sub-Analysis


Though MACE events did not differ:

•Median survival after MACE events was lower (109  days vs. 381 days, p<0.001) when compared to controls.
•Higher risk for respiratory failure/insufficiency coding after MACE events. (27.1 vs. 14.8%, p<0.001)


Clinical Implications


•Exploratory 30-day MACE events were higher but not statistically different after covariate balancing.
•Higher rates of respiratory failure/insufficiency coding after MACE events suggests that they are more severe, when compared to controls.
•Survival after MACE events was lower and right-skewed suggesting considerable impact from 30-day MACE events.
•Current preoperative evaluation highly reliant on EKG and echocardiography. Not adequate to determine presence of cardiac sarcoidosis. (Cardiac MRI, PET scanning needed).
•Higher rates of right ventricular afterload may contribute to postoperative fluid overload and CHF events.
•Lack of high-quality evidence for CS management.
•Preoperative proBnP, subspecialty optimization may be warranted when clinical suspicion is high for CS.


Conclusions

•Although the secondary endpoint of 30-day MACE events was not significant after covariate balancing, these findings suggest  preoperative optimization opportunities.
•Cautious interpretation of  survival data is needed, given the low number of  deaths (n=72) in the study time period.
•Preoperative optimization, likely with sub-specialty assistance should be considered to characterize the extent of cardiac disease and reduce postoperative MACE events.

References

•Cheng RK, et al. Diagnosis and Management of Cardiac Sarcoidosis: A Scientific Statement From the American Heart Association (2024).
•Yafasova A et al. Long-term Adverse Cardiac Outcomes in Patients With Sarcoidosis. (2020).


78th Annual PostGraduate Assembly in Anesthesiology (PGA78) 2024 » banner
Copyright © 2015-2026, ePostersLive® SciGen is a registered trademark of SciGen Technologies S.A. Patent pending.

This website and third-party tools we use rely on cookies for the best user experience. By selecting "I agree", you agree to cookie usage as described in our Privacy Policy.
