145 posters, 12 topics, 25 sessions, 145 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
UCSF 2023 Inquiry Symposium
10 May | University of San Francisco

P059
The Gut Microbiota's Metabolism of Allopurinol
Poster Presenter
Authors
Part of Topic
Biomedical Sciences
Resulting from hyperuricemia and the deposition of urate crystals in joints, gout has a prevalence of about 3.9% among adults in the United States and is one of the most common forms of arthritis. Certain medications, including allopurinol, reduce the frequency of gout flares by interfering with the body’s synthesis of uric acid, thereby decreasing serum urate levels. Despite being one of the most common first-line medications in lowering serum urate, allopurinol varies in its efficacy, as patients require widely different doses of the medication before achieving the same desired decrease in serum urate concentrations. While researchers have considered differences in absorption, metabolism, and excretion between humans as possible causes of this variation, little research has yet to consider differences in metabolism by the gut microbiota as a contributory factor. Prior research has already shown that, by enzymatically altering a drug’s structure, the gut microbiota can influence an individual’s response to dozens of medications, spanning different pharmacological classes. As a result, I hypothesize that the gut microbiota is capable of metabolizing allopurinol, and the aims of this project consist of (1) developing a method of extracting and detecting allopurinol from a bacterial growth culture (2) and measuring changes in allopurinol concentrations after incubating different bacterial fecal communities with the medication.
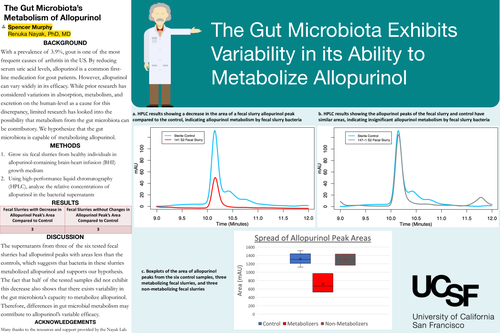
The first step in this project was creating reliable methods for extracting allopurinol from brain-heart infusion (BHI) growth medium and measuring the concentration of allopurinol with high-performance liquid chromatography (HPLC). I then grew six fecal bacterial communities from previously collected stool samples from healthy individuals in allopurinol-containing BHI in an anaerobic chamber at 37 °C. The BHI for these fecal slurry samples contained allopurinol at a concentration of 0.525 mM. In addition, I had three different controls for each fecal slurry. These controls consisted of BHI-only, 0.525 mM allopurinol in BHI, and the fecal slurry in BHI. The bacterial cultures and controls spent 2.5 days in the anaerobic chamber. Afterwards, I removed the bacterial cultures and controls from the chamber, centrifuged them, and separated the supernatants from any bacterial pellets that formed. Using the protocols that I had previously developed, I then extracted allopurinol from the supernatants and used HPLC to measure the relative concentrations of the medication in the samples.
The developed HPLC-protocol detects allopurinol at ~10.200 minutes. The areas of the allopurinol peaks of the six 0.525 mM allopurinol in BHI controls had a range of 1120.86 – 1516.42 mAU and an average of 1319.09 mAU (SD: 136.7 mAU & 95% CI: 1319.09 +/- 109.38 mAU). In three of the six tested fecal slurries, the allopurinol peaks of the samples containing bacteria and 0.525 mM allopurinol in BHI had smaller areas compared to the 95% CI of the average control area. These fecal slurries had allopurinol peaks with areas of 670.22 mAU, 970.51 mAU, 526.57 mAU. The average allopurinol peak area of these fecal slurry samples is 722.43 mAU (SD: 226.53 mAU). The 0.525 mM allopurinol in BHI with bacteria samples for these fecal slurries did not generate any new prominent nonallopurinol peaks that were not also present on the respective BHI and fecal slurry controls.
For the other three fecal slurries, the areas of the allopurinol peaks were within the control range with the values of 1436.7 mAU, 1167.74 mAU, and 1307.37 mAU. The average allopurinol peak area of these samples is 1303.94 mAU (SD: 134.31 SD).
The developed protocols were able to consistently extract and detect allopurinol dissolved in BHI. For their 0.525 mM allopurinol in BHI with bacteria samples, three of the six tested fecal slurries had allopurinol peaks with areas in the range generated by the 0.525 mM allopurinol in BHI controls, indicating that little to no metabolism of allopurinol occurred. In contrast, the other three fecal slurries had a significant decrease in the areas of the allopurinol peaks compared to the controls, suggesting that the bacteria in these fecal slurries did metabolize the allopurinol. It is not known, however, what metabolites of allopurinol the bacteria in these fecal slurries produced. The 0.525 mM allopurinol in BHI with bacteria samples for the metabolizing fecal slurries did not produce prominent peaks at the retention times of known metabolites of allopurinol. They also did not produce any prominent new peaks that were not present on the BHI and bacteria controls. These findings suggest that the current extraction and HPLC protocols are not capable of clearly detecting the allopurinol metabolites produced in these samples. Regardless, these results not only support the hypothesis that the gut microbiota can metabolize allopurinol but also show that there is variability in the gut microbiota’s metabolism of allopurinol.
Further investigation can be performed to better understand the gut microbiota’s metabolism of allopurinol and the clinical impact this may have. Sequencing the bacteria in the fecal slurries used in this project would identify the species the comprise these different fecal communities. This experimental set-up could then be repeated using these individual species in allopurinol-containing BHI to discover which bacterial species were responsible for allopurinol’s metabolism and/or if the interactions between certain species is required for metabolism to occur. Research can also focus on whether there is a compositional difference of the gut microbiota between gout patients who require low doses of allopurinol and those who require higher doses, and, if so, whether the compositional difference is associated with a difference in the metabolism of allopurinol. If research does show that the gut microbiota influences the efficacy of allopurinol, then testing and altering the gut microbiota can be considered for methods to better predict and improve the responses that gout patients have to allopurinol.