167 posters, 28 videos, 9 topics, 12 sessions, 337 authors, 160 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2023 Annual Meeting
31 May - 3 June, 2023 | Boston, MA

PC88
Valve-in-valve Tavi With Stent Frame Fracture In A Degenerated Rapid Deployment Valve
Poster Presenter
Part of Topic
Valve - Transcatheter Therapies
VALVE-IN-VALVE TAVI WITH STENT FRAME FRACTURE IN A DEGENERATED RAPID DEPLOYMENT VALVE
Objective: Valve-in-valve (ViV) TAVI has become a strategy todeal with degenerated aorticbioprosthesis. A benefit is theavoidance of the higher surgicalrisks of re-do cases, whichhowever is limited by a higherrisk of a valvular patientprosthesis mismatch. Interventional stent frame fractureduring ViV implantation couldreduce this risk. However, in rapid deployment valves, there isa lack of data for this procedure.
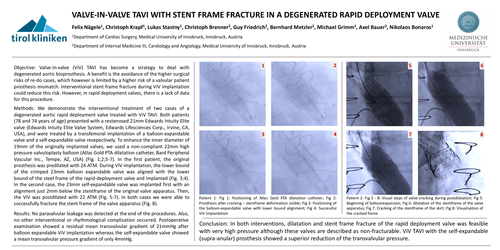
Methods: We demonstrate theinterventional treatment of twocases of a degenerated aorticrapid deployment valve treatedwith ViV TAVI. Both patients (78 and 74 years of age) presentedwith a restenosed 21mm Edwards Intuity Elite valve (Edwards Intuity Elite Valve System, Edwards Lifesciences Corp., Irvine, CA, USA), and weretreated by a transfemoralimplantation of a balloon-expandable valve and a self-expandable valve resepectively. To enhance the inner diameter of19mm of the originally implantedvalves, we used a non-compliant22mm high pressurevalvuloplasty balloon (Atlas Gold PTA dilatation catheter, Bard Peripheral Vascular Inc., Tempe, AZ, USA) (Fig. 1;2;5-7). In thefirst patient, the original prosthesis was predilated with 24 ATM. During ViV implantation, the lower bound of the crimped23mm balloon expandable valvewas aligned with the lower boundof the steel frame of the rapid-deployment valve and implanted(Fig. 3;4). In the second case, the23mm self-expandable valve was implanted first with an alignmentjust 2mm below the stentframe ofthe original valve apparatus. Then, the ViV was postdilatedwith 22 ATM (Fig. 5-7). In bothcases we were able tosuccessfully fracture the stentframe of the valve apparatus (Fig. 8).
Results: No paravalvular leakagewas detected at the end of theprocedures. Also, no otherinterventional or rhythmologicalcomplication occurred. Postoperative examinationshowed a residual meantransvalvular gradient of21mmHg after balloonexpandable ViV implantationwhereas the self-expandablevalve showed a meantransvalvular pressure gradient ofonly 4mmHg.
Conclusion: In bothinterventions, dilatation and stent frame fracture of therapid deployment valve was feasible with very high pressure although thesevalves are described as non-fracturable. ViV TAVI withthe self-expandable (supra-anular) prosthesis showed a superior reduction of thetransvalvular pressure.