477 posters, 14 topics, 2,065 authors, 1,055 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
The Joint EBJIS-MSIS 2026 Conference
17 - 19 September, 2026 | Porto, Portugal

EP181
Risk factors, synovial fluid culture positivity and recurrence in septic arthritis in native joints
Part of Topic
Microbiology
BACKGROUND & AIM
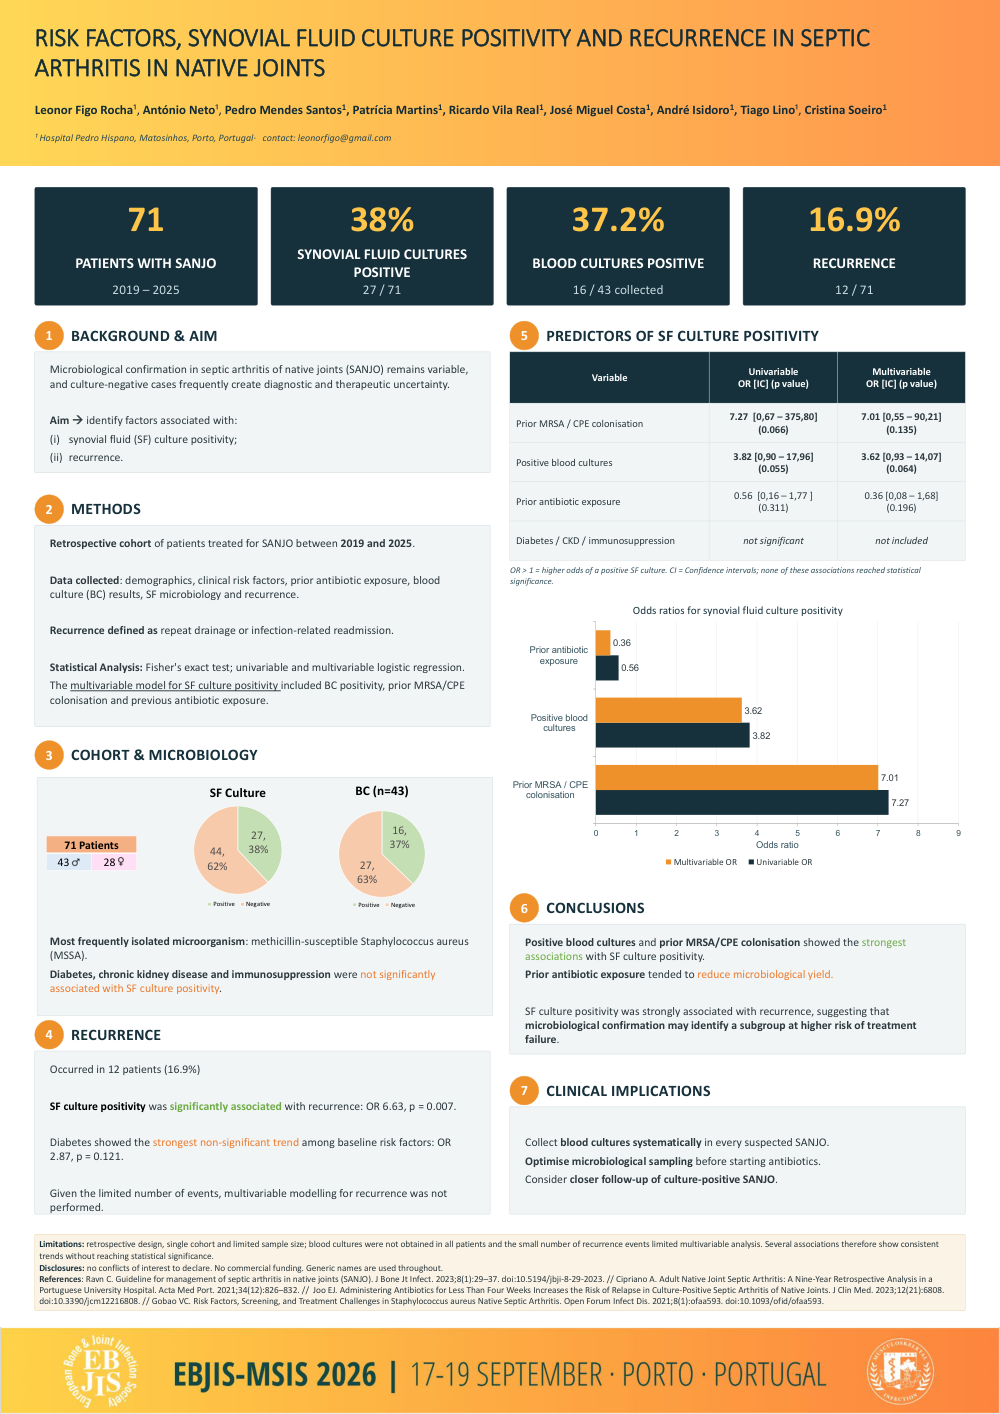
Microbiological confirmation in septic arthritis of native joints (SANJO) remains variable,
and culture-negative cases frequently create diagnostic and therapeutic uncertainty.
Aim→identify factors associated with: (i) synovial fluid (SF) culture positivity; (ii) recurrence.
METHODS
Retrospective cohort of patients treated for SANJO between 2019 and 2025.
Data collected: demographics, clinical risk factors, prior antibiotic exposure, blood culture (BC) results, SF microbiology and recurrence.
Recurrence defined as repeat drainage or infection-related readmission.
Statistical Analysis: Fisher's exact test; univariable and multivariable logistic regression.
The multivariable model for SF culture positivity included BC positivity, prior MRSA/CPE colonisation and previous antibiotic exposure.
COHORT & MICROBIOLOGY
Most frequently isolated microorganism: methicillin-susceptible Staphylococcus aureus (MSSA).
Diabetes, chronic kidney disease and immunosuppression were not significantly associated with SF culture positivity.
RECURRENCE Occurred in 12 patients (16.9%)
SF culture positivity was significantly associated with recurrence: OR 6.63, p = 0.007. Diabetes showed the strongest non-significant trend among baseline risk factors: OR
2.87, p = 0.121.
Given the limited number of events, multivariable modelling for recurrence was not performed.
CONCLUSIONS
Positive blood cultures and prior MRSA/CPE colonisation showed the strongest associations with SF culture positivity.
Prior antibiotic exposure tended to reduce microbiological yield.
SF culture positivity was strongly associated with recurrence, suggesting that
microbiological confirmation may identify a subgroup at higher risk of treatment failure.
CLINICAL IMPLICATIONS
Collect blood cultures systematically in every suspected SANJO. Optimise microbiological sampling before starting antibiotics. Consider closer follow-up of culture-positive SANJO.