501 posters, 2 videos, 1 audios, 8 topics, 37 sessions, 395 authors, 307 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
23rd Annual Pain Medicine Meeting 2024
November 21-23, 2024 | Caesars Palace, Las Vegas, Nevada

6192
IMPORTANCE OF UTILIZING ULTRASOUND FOR DIAGNOSIS & TREATMENT OF ACUTE RLE PAIN AND FOOT DROP DUE TO PERONEAL NERVE CYST
Poster Presenter
Authors
Affiliations
Part of Topic
Scientific Abstracts > Acute Pain
Introduction
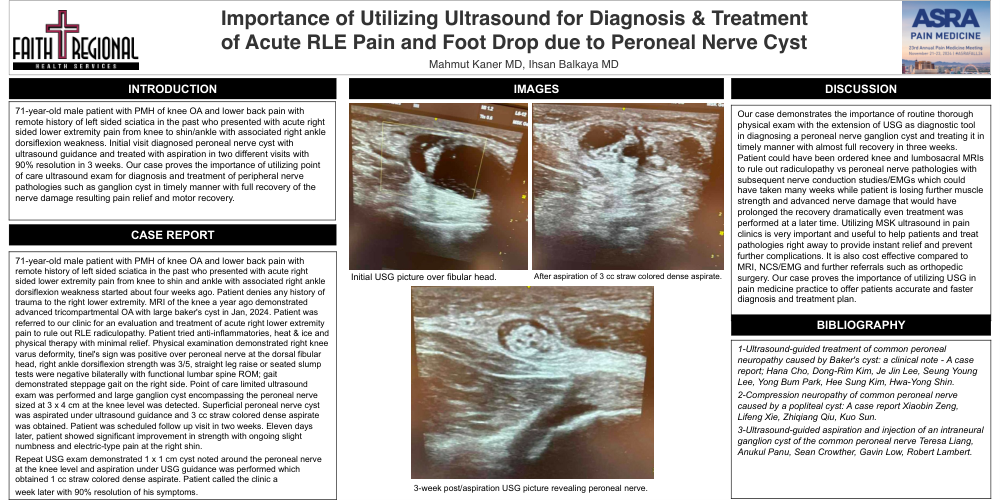
71-year old male patient with PMH of knee OA and lower back pain with remote history of left sided
sciatica in the past who presented with acute right sided lower extremity pain from knee to shin/ankle
with associated right ankle dorsiflexion weakness. Initial visit diagnosed peroneal nerve cyst with
ultrasound guidance and treated with aspiration in two different visits with 90% resolution in 3 weeks.
Our case proves the importance of utilizing point of care ultrasound exam for diagnosis and treatment
of peripheral nerve pathologies such as ganglion cyst in timely manner with full recovery of the nerve
damage resulting pain relief and motor recovery.
Materials and Methods
As the case report is devoid of patient identifiable information, it is exempt from IRB review requirements as per Faith
Regional Health Services policy.
Results/Case Report
71-year-old male patient with PMH of knee OA and lower back pain with remote history of left sided sciatica in the past
who presented with acute right sided lower extremity pain from knee to shin and ankle with associated right ankle
dorsiflexion weakness started about four weeks ago. Patient denies any history of trauma to the right lower extremity.
MRI of the knee a year ago demonstrated advanced tricompartmental OA with large baker's cyst in Jan, 2024. Patient
was referred to our clinic for an evaluation and treatment of acute right lower extremity pain to rule out RLE
radiculopathy. Patient tried anti-inflammatories, heat & ice and physical therapy with minimal relief. Physical
examination demonstrated right knee varus deformity, tinel's sign was positive over peroneal nerve at the dorsal
fibular head, right ankle dorsiflexion strength was 3/5, straight leg raises or seated slump tests were negative
bilaterally with functional lumbar spine ROM; gait demonstrated steppage gait on the right side. Point of care limited
ultrasound exam was performed and large ganglion cyst encompassing the peroneal nerve sized at 3 x 4 cm at the
knee level was detected. Superficial peroneal nerve cyst was aspirated under ultrasound guidance and 3 cc straw
colored dense aspirate was obtained. Patient was scheduled follow up visit in two weeks. Eleven days later, patient
showed significant improvement in strength with ongoing slight numbness and electric-type pain at the right shin.
Repeat USG exam demonstrated 1 x 1 cm cyst noted around the peroneal nerve at the knee level and aspiration
under USG guidance was performed which obtained 1 cc straw colored dense aspirate. Patient called the clinic a
week later with 90% resolution of his symptoms.
Discussion
Our case demonstrates the importance of diagnosing a peroneal nerve ganglion cyst and treating it in
timely manner with almost full recovery in three weeks. Patient could have been ordered knee and
lumbosacral MRIs to rule out radiculopathy vs peroneal nerve pathologies with subsequent nerve
conduction studies/EMGs which could have taken many weeks while patient is losing further muscle
strength and advanced nerve damage that would have prolonged the recovery dramatically even
treatment was performed at a later time.
Utilizing MSK ultrasound in pain clinics is very important and useful to help patients and treat
pathologies right away to provide instant relief and prevent further complications. It is also cost effective
compared to MRI, NCS/EMG and further referrals such as orthopedic surgery. Our case proves the
importance of utilizing USG in pain medicine practice to offer patients accurate and faster diagnosis and
treatment plan.
References
1-Ultrasound-guided treatment of common peroneal neuropathy caused by Baker's cyst: a clinical note -
A case report; Hana Cho, Dong-Rim Kim, Je Jin Lee, Seung Young Lee, Yong Bum Park, Hee Sung Kim,
Hwa-Yong Shin.
2-Compression neuropathy of common peroneal nerve caused by a popliteal cyst: A case report
Xiaobin Zeng, Lifeng Xie, Zhiqiang Qiu, Kuo Sun.
3-Ultrasound-guided aspiration and injection of an intraneural ganglion cyst of the common peroneal
nerve Teresa Liang, Anukul Panu, Sean Crowther, Gavin Low, Robert Lambert.