501 posters, 2 videos, 1 audios, 8 topics, 37 sessions, 395 authors, 307 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
23rd Annual Pain Medicine Meeting 2024
November 21-23, 2024 | Caesars Palace, Las Vegas, Nevada

6136
ABRUPT KYPHOTIC COLLAPSE IN SETTING OF OSTEOMYELITIS PRESENTING AS SEVERE BACK PAIN
Poster Presenter
Authors
Affiliations
Part of Topic
Scientific Abstracts > Acute Pain
Abrupt Kyphotic Collapse in Setting of Osteomyelitis Presenting as Severe Back Pain
Abhishek Shrinet MD, Eric Xu DO
Department of Physical Medicine and Rehabilitation at Temple University Hospital and Good Shepherd Rehabilitation Hospital
INTRO
•Vertebral osteomyelitis is a rare infectious disease with 4.8 cases per 100,000 in the US
•Intravenous drug users are at increased risk of osteomyelitis
•Axial back pain is the most common symptom
•Presentation is highly variable and may include constitutional symptoms or neurologic deficits
•Complications include systemic sepsis, spinal instability with or without spinal cord compression
•38% of patients will develop neurological complications including neuropathy, motor weakness, or paralysis
•Conservative treatment does not always prevent advanced vertebral destruction that can result in acute spinal deformities such as kyphosis or subluxation requiring surgical stabilization
CASE REPORT
•42-year-old female with past medical of intravenous drug abuse who presented to hospital with severe back pain and acute bilateral paraplegia
•She was recently diagnosed with thoracic spine osteomyelitis with a large phlegmon abutting her descending aorta extending from T5-T10 and methicillin-sensitive staphylococcus aureus bacteremia but left against medical advice
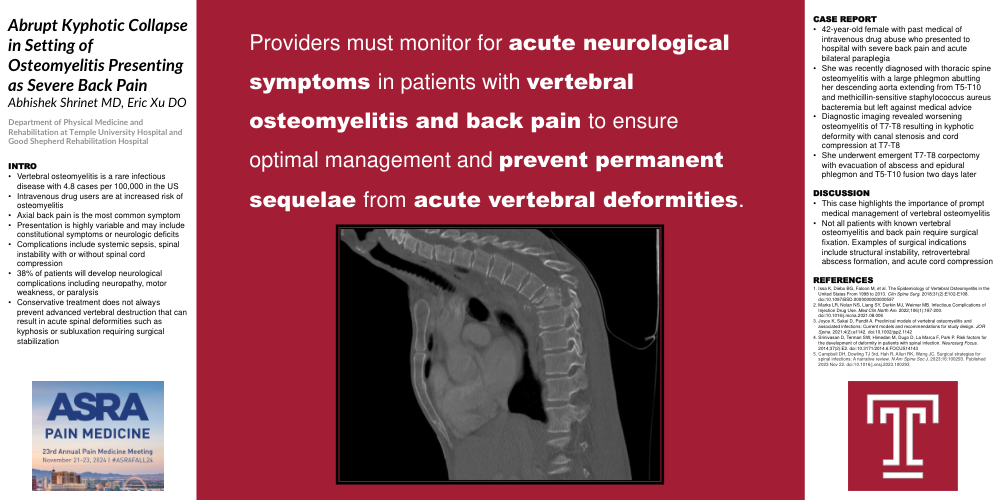
•Diagnostic imaging revealed worsening osteomyelitis of T7-T8 resulting in kyphotic deformity with canal stenosis and cord compression at T7-T8
•She underwent emergent T7-T8 corpectomy with evacuation of abscess and epidural phlegmon and T5-T10 fusion two days later
DISCUSSION
•This case highlights the importance of prompt medical management of vertebral osteomyelitis
•Not all patients with known vertebral osteomyelitis and back pain require surgical fixation. Examples of surgical indications include structural instability, retrovertebral abscess formation, and acute cord compression
Providers must monitor for acute neurological symptoms in patients with vertebral osteomyelitis and back pain to ensure optimal management and prevent permanent sequelae from acute vertebral deformities.
REFERENCES
1.Issa K, Diebo BG, Faloon M, et al. The Epidemiology of Vertebral Osteomyelitis in the United States From 1998 to 2013. Clin Spine Surg. 2018;31(2):E102-E108. doi:10.1097/BSD.0000000000000597
2.Marks LR, Nolan NS, Liang SY, Durkin MJ, Weimer MB. Infectious Complications of Injection Drug Use. Med Clin North Am. 2022;106(1):187-200. doi:10.1016/j.mcna.2021.08.006
3.Joyce K, Sakai D, Pandit A. Preclinical models of vertebral osteomyelitis and associated infections: Current models and recommendations for study design. JOR Spine. 2021;4(2):e1142. doi:10.1002/jsp2.1142
4.Srinivasan D, Terman SW, Himedan M, Dugo D, La Marca F, Park P. Risk factors for the development of deformity in patients with spinal infection. Neurosurg Focus. 2014;37(2):E2. doi:10.3171/2014.6.FOCUS14143
5.Campbell DH, Dowling TJ 3rd, Hah R, Alluri RK, Wang JC. Surgical strategies for spinal infections: A narrative review. N Am Spine Soc J. 2023;16:100293. Published 2023 Nov 22. doi:10.1016/j.xnsj.2023.100293