1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

CLL - 693
BTK Inhibitors Are Associated With Significantly Lower Hospitalization and Reduced Cardiovascular Morbidity Compared With Venetoclax-Based Regimens in CLL/SLL: A Propensity Score-Matched, Real-World Analysis
Poster Presenter
Authors
Part of Topic
Chronic Lymphocytic Leukemia (CLL)
Introduction
Covalent BTK inhibitors and venetoclax-based regimens are the dominant treatment paradigms for chronic lymphocytic leukemia/small lymphocytic lymphoma (CLL/SLL). They differ fundamentally in structure: BTK inhibitors are continuous oral monotherapy, whereas venetoclax and anti-CD20 antibody regimens are fixed-duration, infusion-dependent, and require ramp-up with tumor lysis syndrome monitoring. These differences plausibly translate into divergent healthcare utilization. BTK inhibitors additionally carry a recognized atrial arrhythmia signal, while comparative data on other cardiovascular endpoints remain sparse. No randomized trial has compared these strategies across hospitalization and cardiovascular morbidity.
Aim
To compare all-cause hospitalization, mortality, and incident cardiovascular morbidity between BTK inhibitor monotherapy and venetoclax/anti-CD20-containing regimens in CLL/SLL, using a large federated real-world network with propensity score matching.
Methods
Data: TriNetX Research Network (111 HCOs). Adults with CLL/SLL diagnosed 2016–2023.
Cohorts: BTKi — ibrutinib, acalabrutinib, or zanubrutinib (n=8,661) vs. venetoclax, rituximab, or obinutuzumab (n=9,823); mutually exclusive.
Matching: 1:1 propensity score matching on demographics, cardiovascular comorbidities, medications, and labs → 6,456 pairs.
Endpoints: all-cause hospitalization and mortality; incident AF, heart failure, CAD, hypertension, and aortic stenosis over 730 days.
Analysis: risk ratios with 95% CIs; Kaplan-Meier with log-rank testing.
Results
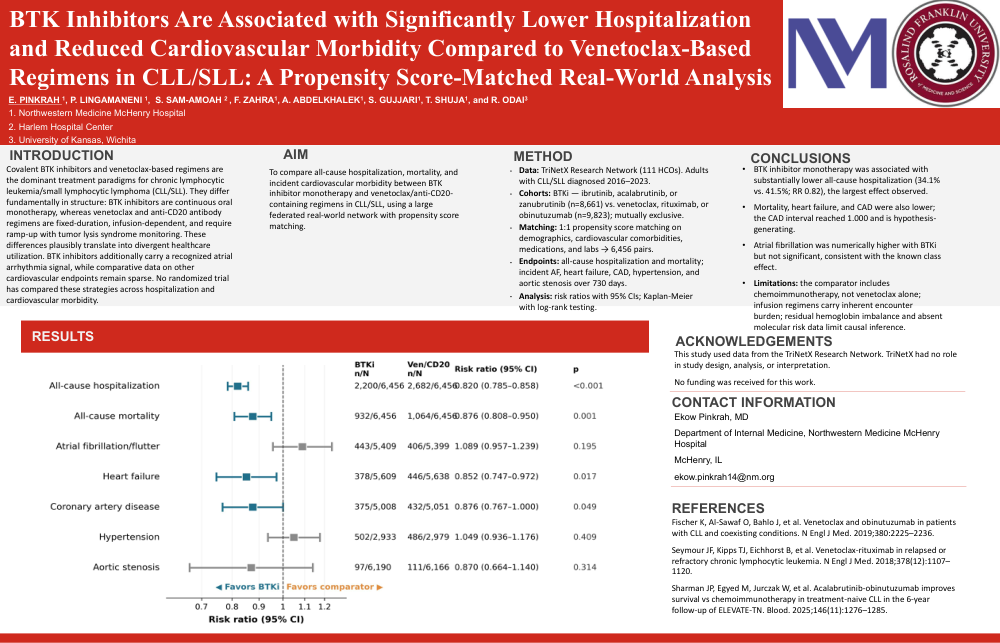
BTKi-treated patients had asignificantly lower rate of all-cause hospitalization(34.1% vs. 41.5%; Risk Ratio [RR] 0.82; p<0.001), representing the most substantial difference observed. All-cause mortality was also significantly reduced in theBTKicohort (14.4% vs. 16.5%; RR 0.876; 95% CI 0.808–0.950; p=0.001; 2-year survival 83.5% vs. 81.7%). New-onset HF was lower withBTKi(6.7% vs. 7.9%; RR 0.852; p=0.017), as was incident CAD (7.5% vs. 8.6%; RR 0.876; p=0.049). New-onsetAFibrates were numerically higher withBTKibut did not reach statistical significance (8.2% vs. 7.5%; p=0.195). No significant between-group differences were observed for new-onset HTN or aortic stenosis.
Conclusion
BTK inhibitor monotherapy was associated with substantially lower all-cause hospitalization (34.1% vs. 41.5%; RR 0.82), the largest effect observed.
Mortality, heart failure, and CAD were also lower; the CAD interval reached 1.000 and is hypothesis-generating.
Atrial fibrillation was numerically higher with BTKi but not significant, consistent with the known class effect.
Limitations: the comparator includes chemoimmunotherapy, not venetoclax alone; infusion regimens carry inherent encounter burden; residual hemoglobin imbalance and absent molecular risk data limit causal inference.