1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

CML - 090
Real-World Data on Clinical Profile, Treatment Strategies, and Feto-Maternal Outcomes of Pregnancies Among Patients With Chronic Myeloid Leukemia in a Resource-Constrained Setting: A 5-Year Single-Center Retrospective Cohort Study
Poster Presenter
Authors
Part of Topic
Chronic Myeloid Leukemia (CML)
Real-World Data on Clinical Profile, Treatment Strategies, and Feto-Maternal Outcomes of Pregnancies Among Patients with Chronic Myeloid Leukemia in a Resource-Constrained Setting: A 5-year Single-Center Retrospective Cohort Study
Caryn Louise D. Gutierrez, M.D.1, Rowel David D. Yap, M.D.1, Anne Kristine H. Quero-Taggaoa, M.D.2
1Post-Residency Fellow, Department of Internal Medicine - Division of Hematology, Philippine General Hospital
2Consultant, Department of Internal Medicine - Division of Hematology, Philippine General Hospital
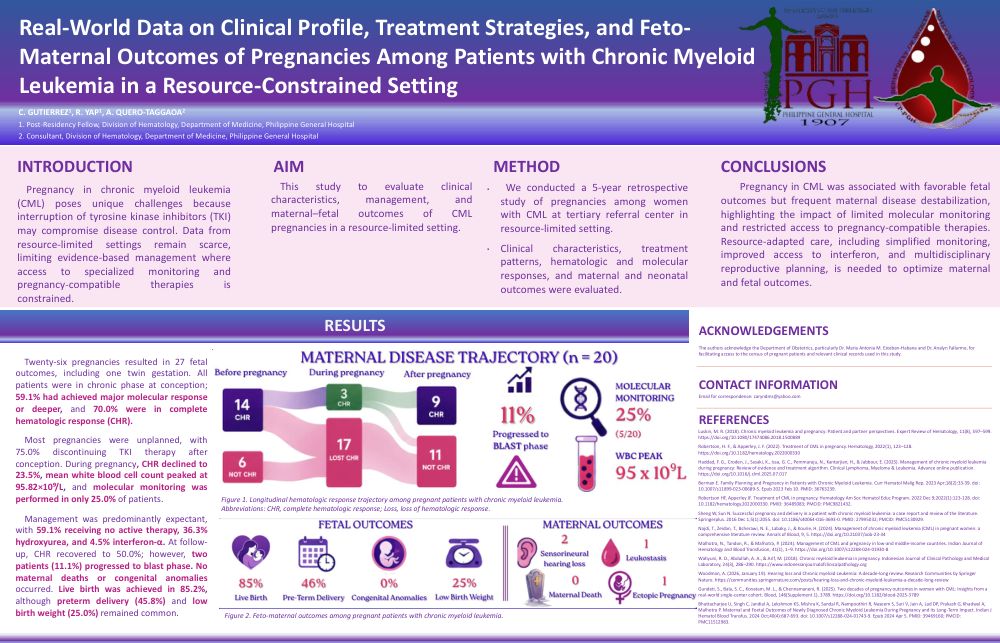
Background. Pregnancy in chronic myeloid leukemia (CML) poses unique challenges because interruption of tyrosine kinase inhibitors (TKI) may compromise disease control. Data from resource-limited settings remain scarce, limiting evidence-based management where access to specialized monitoring and pregnancy-compatible therapies is constrained.
Methodology. We conducted a 5-year retrospective study of pregnancies among women with CML at tertiary referral center in resource-limited setting. Clinical characteristics, treatment patterns, hematologic and molecular responses, and maternal and neonatal outcomes were evaluated.
Results. Twenty-six pregnancies resulted in 27 fetal outcomes, including one twin gestation. All patients were in chronic phase at conception; 59.1% had achieved major molecular response or deeper, and 70.0% were in complete hematologic response (CHR). Most pregnancies were unplanned, with 75.0% discontinuing TKI therapy after conception. During pregnancy, CHR declined to 23.5%, mean white blood cell count peaked at 95.82×10⁹/L, and molecular monitoring was performed in only 25.0% of patients. Management was predominantly expectant, with 59.1% receiving no active therapy, 36.3% hydroxyurea, and 4.5% interferon-α. At follow-up, CHR recovered to 50.0%; however, two patients (11.1%) progressed to blast phase. No maternal deaths or congenital anomalies occurred. Live birth was achieved in 85.2%, although preterm delivery (45.8%) and low birth weight (25.0%) remained common.
Conclusion. Pregnancy in CML was associated with favorable fetal outcomes but frequent maternal disease destabilization, highlighting the impact of limited molecular monitoring and restricted access to pregnancy-compatible therapies. Resource-adapted care, including simplified monitoring, improved access to interferon, and multidisciplinary reproductive planning, is needed to optimize maternal and fetal outcomes.