2,281 posters, 63 videos, 56 audios, 43 topics, 18 sessions, 6,174 authors, 2,323 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2025
June 23 - 25, 2025 | ExCeL London, UK
EP.1665
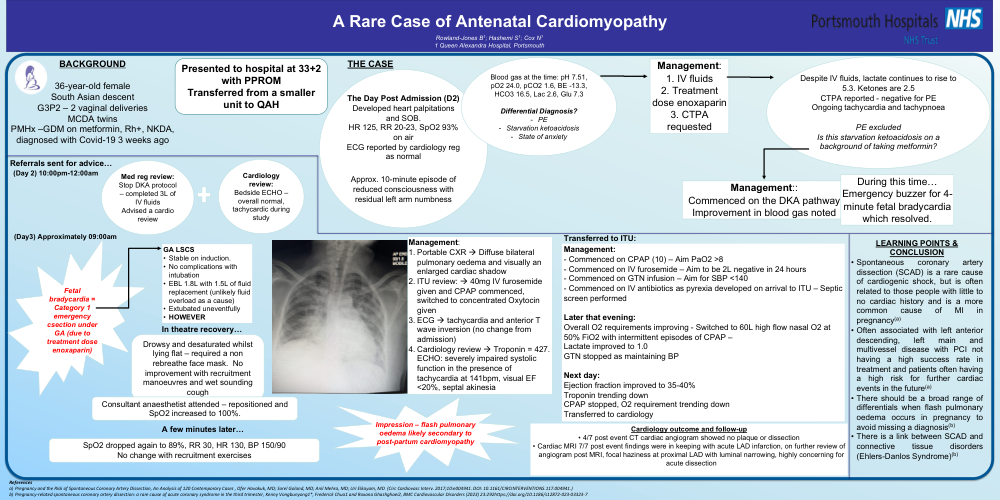
A rare case of antenatal cardiomyopathy
Poster Presenter
Authors
Affiliations
Part of Topic
Maternal medicine
A Rare Case of Antenatal Cardiomyopathy.
Rowland-Jones B1; Hashemi S1; Cox N1. 1 Queen Alexandra Hospital, Portsmouth.
BACKGROUND
36-year-old female
South Asian descent
G3P2 – 2 vaginal deliveries
MCDA twins
PMHx –GDM on metformin, Rh+, NKDA, diagnosed with Covid-19 3 weeks ago
Presented to hospital at 33+2 with PPROM. Transferred from a smaller unit to QAH.
The case:
The Day Post Admission (D2)
Developed heart palpitations and SOB.
HR 125, RR 20-23, SpO2 93% on air
ECG reported by cardiology reg as normal
Approx. 10-minute episode of reduced consciousness with residual left arm numbness.
Blood gas at the time: pH 7.51, pO2 24.0, pCO2 1.6, BE -13.3, HCO3 16.5, Lac 2.6, Glu 7.3
Differential Diagnosis?
Management:
1. IV fluids
2. Treatment dose enoxaparin
3. CTPA requested
Despite IV fluids, lactate continues to rise to 5.3. Ketones are 2.5
CTPA reported - negative for PE
Ongoing tachycardia and tachypnoea
PE excluded
Is this starvation ketoacidosis on a background of taking metformin?
Management::
Commenced on the DKA pathway
Improvement in blood gas noted
During this time…
Emergency buzzer for 4-minute fetal bradycardia which resolved.
Referrals sent for advice…
(Day 2) 10:00pm-12:00am
Med reg review:
Stop DKA protocol – completed 3L of IV fluids
Advised a cardio review
Cardiology review:
Bedside ECHO – overall normal, tachycardic during study
(Day3) Approximately 09:00am
Fetal bradycardia = Category 1 emergency csection under GA (due to treatment dose enoxaparin)
GA LSCS
In theatre recovery…
Drowsy and desaturated whilst lying flat – required a non rebreathe face mask. No improvement with recruitment manoeuvres and wet sounding cough
Consultant anaesthetist attended – repositioned and SpO2 increased to 100%.
A few minutes later…
SpO2 dropped again to 89%, RR 30, HR 130, BP 150/90
No change with recruitment exercises
Management:
Impression – flash pulmonary oedema likely secondary to post-partum cardiomyopathy
Transferred to ITU:
Management:
- Commenced on CPAP (10) – Aim PaO2 >8
- Commenced on IV furosemide – Aim to be 2L negative in 24 hours
- Commenced on GTN infusion – Aim for SBP <140
- Commenced on IV antibiotics as pyrexia developed on arrival to ITU – Septic screen performed
Later that evening:
Overall O2 requirements improving - Switched to 60L high flow nasal O2 at 50% FiO2 with intermittent episodes of CPAP –
Lactate improved to 1.0
GTN stopped as maintaining BP
Next day:
Ejection fraction improved to 35-40%
Troponin trending down
CPAP stopped, O2 requirement trending down
Transferred to cardiology
Cardiology outcome and follow-up
LEARNING POINTS & CONCLUSION
References