2,281 posters, 63 videos, 56 audios, 43 topics, 18 sessions, 6,174 authors, 2,323 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2025
June 23 - 25, 2025 | ExCeL London, UK
EP.1658
Hypertriglyceridemia-induced acute pancreatitis in pregnancy: A case report
Poster Presenter
Authors
Affiliations
Part of Topic
Maternal medicine
Hypertriglyceridemia-induced acute pancreatitis in pregnancy: A case report - Dr. TANG Yuen Chung, Dr. KWONG Lee Ting
Tuen Mun Hospital, Hong Kong SAR, China Correspondence to: rexchung07@gmail.com
Objective:
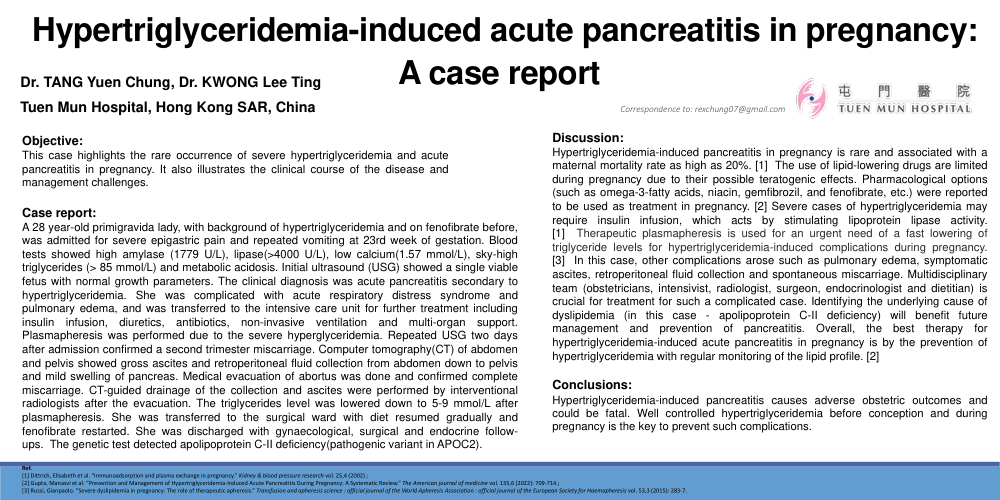
This case highlights the rare occurrence of severe hypertriglyceridemia and acute pancreatitis in pregnancy. It also illustrates the clinical course of the disease and management challenges.
Case report:
A 28 year-old primigravida lady, with background of hypertriglyceridemia and on fenofibrate before, was admitted for severe epigastric pain and repeated vomiting at 23rd week of gestation. Blood tests showed high amylase (1779 U/L), lipase(>4000 U/L), low calcium(1.57 mmol/L), sky-high triglycerides (> 85 mmol/L) and metabolic acidosis. Initial ultrasound (USG) showed a single viable fetus with normal growth parameters. The clinical diagnosis was acute pancreatitis secondary to hypertriglyceridemia. She was complicated with acute respiratory distress syndrome and pulmonary edema, and was transferred to the intensive care unit for further treatment including insulin infusion, diuretics, antibiotics, non-invasive ventilation and multi-organ support. Plasmapheresis was performed due to the severe hyperglyceridemia. Repeated USG two days after admission confirmed a second trimester miscarriage. Computer tomography(CT) of abdomen and pelvis showed gross ascites and retroperitoneal fluid collection from abdomen down to pelvis and mild swelling of pancreas. Medical evacuation of abortus was done and confirmed complete miscarriage. CT-guided drainage of the collection and ascites were performed by interventional radiologists after the evacuation. The triglycerides level was lowered down to 5-9 mmol/L after plasmapheresis. She was transferred to the surgical ward with diet resumed gradually and fenofibrate restarted. She was discharged with gynaecological, surgical and endocrine follow-ups. The genetic test detected apolipoprotein C-II deficiency(pathogenic variant in APOC2).
Discussion:
Hypertriglyceridemia-induced pancreatitis in pregnancy is rare and associated with a maternal mortality rate as high as 20%. [1] The use of lipid-lowering drugs are limited during pregnancy due to their possible teratogenic effects. Pharmacological options (such as omega-3-fatty acids, niacin, gemfibrozil, and fenofibrate, etc.) were reported to be used as treatment in pregnancy. [2] Severe cases of hypertriglyceridemia may require insulin infusion, which acts by stimulating lipoprotein lipase activity. [1] Therapeutic plasmapheresis is used for an urgent need of a fast lowering of triglyceride levels for hypertriglyceridemia-induced complications during pregnancy. [3] In this case, other complications arose such as pulmonary edema, symptomatic ascites, retroperitoneal fluid collection and spontaneous miscarriage. Multidisciplinary team (obstetricians, intensivist, radiologist, surgeon, endocrinologist and dietitian) is crucial for treatment for such a complicated case. Identifying the underlying cause of dyslipidemia (in this case - apolipoprotein C-II deficiency) will benefit future management and prevention of pancreatitis. Overall, the best therapy for hypertriglyceridemia-induced acute pancreatitis in pregnancy is by the prevention of hypertriglyceridemia with regular monitoring of the lipid profile. [2]
Conclusions:
Hypertriglyceridemia-induced pancreatitis causes adverse obstetric outcomes and could be fatal. Well controlled hypertriglyceridemia before conception and during pregnancy is the key to prevent such complications.
Ref.
[1] Dittrich, Elisabeth et al. “Immunoadsorption and plasma exchange in pregnancy.” Kidney & blood pressure research vol. 25,4 (2002) ;
[2] Gupta, Manasvi et al. “Prevention and Management of Hypertriglyceridemia-Induced Acute Pancreatitis During Pregnancy: A Systematic Review.” The American journal of medicine vol. 135,6 (2022): 709-714.;
[3] Russi, Gianpaolo. “Severe dyslipidemia in pregnancy: The role of therapeutic apheresis.” Transfusion and apheresis science : official journal of the World Apheresis Association : official journal of the European Society for Haemapheresis vol. 53,3 (2015): 283-7.