191 posters, 5 topics, 20 sessions, 393 authors, 116 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
Obstetric Anaesthesia Annual Scientific Meeting 2023
18 - 19 May, 2023 | EICC Edinburgh

5808909
Impact of offsite teams on anaesthetic time and decision to delivery interval in category one caesarean deliveries
Poster Presenter
Authors
Affiliations
Part of Topic
Service Evaluation
Impact of offsite teams on anaesthetic time and decision to delivery interval in category one caesarean deliveries
Background
•Category 1 caesareans (Cat1LSCS) require expedited delivery due to an urgent threat to the life or health of a woman or foetus1.
•Our audit standard is “decision-to-delivery interval” (DDI) ≤30mins for Cat1LSCS2.
•We utilise offsite teams, with no anaesthetic doctors, operating theatre (OT) nurses nor obstetric consultant on site.
•Off site teams were utilised from 6pm-07:30am on weekdays, weekends and public holidays.
Aim
•This audit reviews the impact of offsite teams on Cat1LSCS DDI and the amount of time attributable to anaesthesia (arrival in OT à Anaesthesia administered).
Method
•A retrospective audit of all Cat1LSCS was conducted from 1 January 2019 to 31 December 2019 and 1 January 2021 to 31 December 2021.
•The two groups were pre and during covid. Anaesthesia onset was spinal dose insertion, last epidural top-up or induction of general anaesthesia (GA).
•Differences were considered significant at p<0.05.
Results
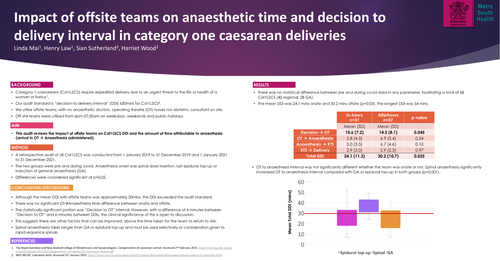
•There was no statistical difference between pre and during covid data in any parameter, facilitating a total of 68 Cat1LSCS (40 regional, 28 GA).
•The mean DDI was 24.1 mins onsite and 30.2 mins offsite (p=0.03). The longest DDI was 54 mins.
•OT to anaesthesia interval was not significantly different whether the team was onsite or not. Spinal anaesthesia significantly increased OT to anaesthesia interval compared with GA or epidural top-up in both groups (p<0.001).
Conclusion/Discussion
•Although the mean DDI with offsite teams was approximately 30mins, the DDI exceeded the audit standard.
•There was no significant OTàAnaesthesia time difference between onsite and offsite.
•The statistically significant portion was “Decision to OT” interval. However, with a difference of 4 minutes between “Decision to OT” and 6 minutes between DDIs, the clinical significance of this is open to discussion.
•This suggests there are other factors that can be improved; above the time taken for the team to return to site.
•Spinal anaesthesia takes longer than GA or epidural top-up and must be used selectively or consideration given to rapid sequence spinals.