477 posters, 14 topics, 2,052 authors, 1,056 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
The Joint EBJIS-MSIS 2026 Conference
17 - 19 September, 2026 | Porto, Portugal
EP113
The use of antibiotic-impregnated cancellous bone grafts in one-stage surgery for fracture related infections
Poster Presenter
Part of Topic
Fracture-Related Infections
AIM
The use of cancellous bone allograft is a technique in bone reconstruction surgery, but its use is avoided in the presence of infection. Bone grafts impregnated with antibiotics (ABIG) have shown their effectiveness as a local antibiotic delivery system.
This study evaluates the clinical and radiographic outcomes of fracture-related infections (FRI) with use of ABIG in a one-stage treatment.
METHOD
Retrospective consecutive case series retrieved from the AIBG database at a level 1 trauma centre.
FRI treated from December 2016 till July 2024 in a single stage with AIBG (vancomycin or tobramycin). The minimum follow up of was 9 months.
RESULTS
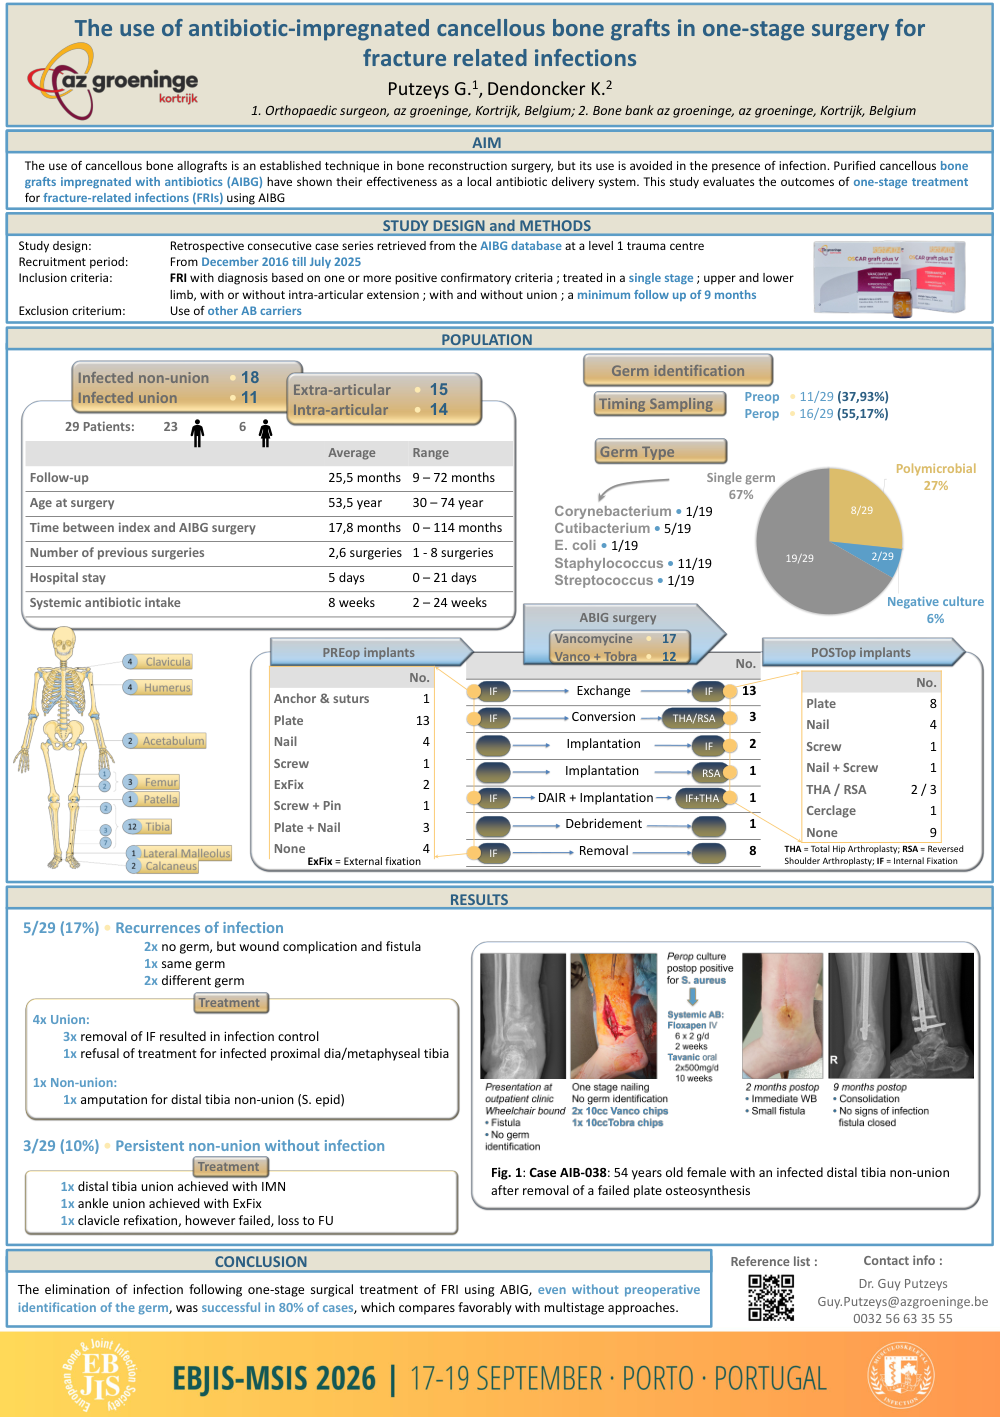
A total of 27 patients (21 men, 6 women; mean age 52.5 years) underwent single-stage surgery for FRI, including 17 with infected non-union and two articular FRIs. Preoperatively, in 24 cases internal fixation implants were present; postoperatively, in 20 cases implants were in place (8 plates, 5 nails, 2 screws, 1 cerclage, and 4 prostheses), including 16 implant exchanges, 1 DAIR, and 3 new implants. Deep tissue cultures identified a single microorganism in 17 cases, polymicrobial infection in 8, and negative cultures in 2.
In 15 out of 25 cases, the infection was only diagnosed postoperatively based on intraoperative cultures. In the remaining 10 cases, pathogens had been detected a mean of 52 days preoperatively.
In 5 of the 15 postoperatively diagnosed cases there was a strong intraoperative suspicion of infection. These cases received a higher volume (more than 30cc) of ABIG with vancomycin and/or tobramycin. This group included two infected osteosynthesis of an acetabulum fracture for which a prosthesis was placed, one according to a DAIR protocol and one after the plates were removed at the same time, two infected tibia fractures for which the plates were removed given their consolidation and one infected femur nonunion for which a plate exchange.
After a mean follow-up of 26.9 months, 5 patients had recurrent infection requiring further surgery; in 3 of these, the fracture was healed and osteosynthesis material was removed resulting in control of the infection with systemic AB. One case resulted in distal tibial amputation for an infected distal tibia nonunion and one case with healing of FRI at the ankle level but recurrent infection at the proximal tibia of the same side. Four non-unions with successful control of infection required secondary stabilization.
CONCLUSION
Elimination of infection following one stage surgical treatment of FRI with the use of ABIG even when there was a postoperative diagnosis of FRI was successful in 80% of cases comparing favourably with multistage approaches.