1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

AML - 591
Acute Organ Dysfunction Burden as a Predictor of In-Hospital Mortality in Leukemia Hospitalizations: A National Inpatient Sample Analysis (2018-2023)
Poster Presenter
Authors
Part of Topic
Acute Myeloid Leukemia (AML)
-
Patients hospitalized with leukemia may develop acute organ dysfunction from infection, treatment toxicity, and systemic complications.
The national impact of accumulating organ dysfunction on inpatient mortality is not well characterized.
-
We evaluated whether increasing acute organ dysfunction burden independently predicts in-hospital mortality.
Design: Retrospective cohort study using the National Inpatient Sample Analysis (2018-2023)
-
Population: Adult hospitalizations (age > 18 years old) with AML (C92.0), CML (C92.1) or CLL (C91.10-C91.12) were identified using ICD-10 codes.
Acute Organ Dysfunction Examples: Sepsis, Acute Kidney Injury, Liver Failure, and Acute Stroke
Burden Score: Sum of acute organ dysfunctions present (range 0-4)
Primary Outcome: In-Hospital Mortality
Survey-weighted multivariate logistic regression adjusted for demographics, leukemia subtype, hospital characteristics, and baseline comorbidities.
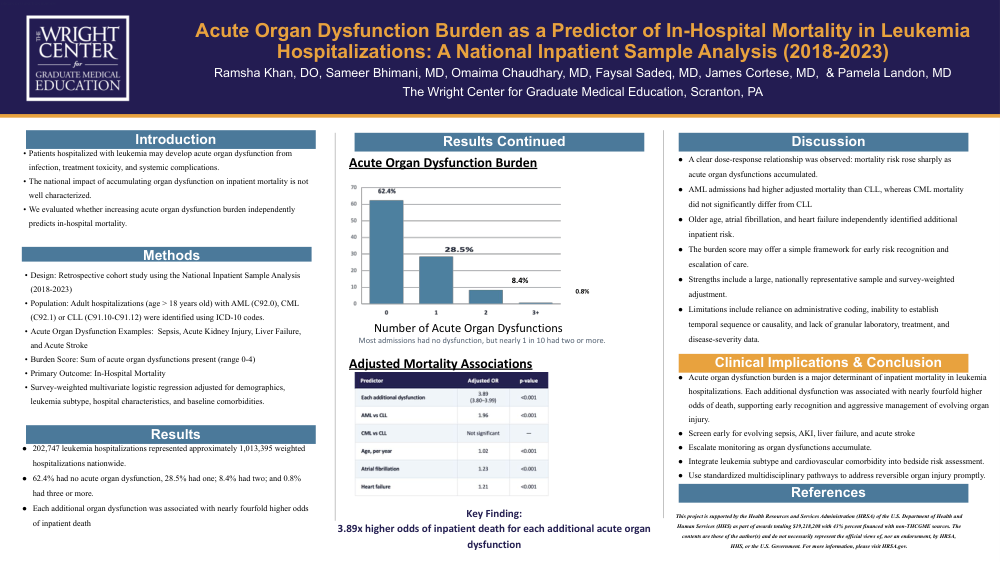
202,747 leukemia hospitalizations represented approximately 1,013,395 weighted hospitalizations nationwide.
62.4% had no acute organ dysfunction, 28.5% had one; 8.4% had two; and 0.8% had three or more.
Each additional organ dysfunction was associated with nearly fourfold higher odds of inpatient death
A clear dose-response relationship was observed: mortality risk rose sharply as acute organ dysfunctions accumulated.
AML admissions had higher adjusted mortality than CLL, whereas CML mortality did not significantly differ from CLL
Older age, atrial fibrillation, and heart failure independently identified additional inpatient risk.
The burden score may offer a simple framework for early risk recognition and escalation of care.
Strengths include a large, nationally representative sample and survey-weighted adjustment.
Limitations include reliance on administrative coding, inability to establish temporal sequence or causality, and lack of granular laboratory, treatment, and disease-severity data.
Acute organ dysfunction burden is a major determinant of inpatient mortality in leukemia hospitalizations. Each additional dysfunction was associated with nearly fourfold higher odds of death, supporting early recognition and aggressive management of evolving organ injury.
Screen early for evolving sepsis, AKI, liver failure, and acute stroke
Escalate monitoring as organ dysfunctions accumulate.
Integrate leukemia subtype and cardiovascular comorbidity into bedside risk assessment.
Use standardized multidisciplinary pathways to address reversible organ injury promptly.