1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

CT - 177
Outcomes of Allogeneic HSCT in Patients With Paroxysmal Nocturnal Hemoglobinuria in Resource-Constrained Settings
Poster Presenter
Authors
Part of Topic
Cellular Therapy (CT)
Background: Paroxysmal Nocturnal Hemoglobinuria (PNH) is a rare, acquired clonal hematopoietic stem cell disorder caused by a mutation in the PIG-A gene, leading to deficiency of glycosylphosphatidylinositol (GPI)-anchored proteins (CD55, CD59). This results in complement-mediated intravascular hemolysis, thrombosis, and bone marrow failure.
Objectives: Our study aims to determine the transplant outcomes in PNH patients in terms of overall survival (OS) and progression-free survival (PFS).
Materials and Methods: A total of 54 patients were diagnosed with PNH in Shifa International Hospitals from 1st January 2016 to 31stDecember 2024, out of which 19 underwent allogeneic HSCT. We conducted a retrospective study of 19 patients (Median age 29 years) who underwent Allogeneic HSCT in the Bone marrow transplant center of Shifa International Hospital from 1st January 2016 to 31stDecember 2024. The observed parameters included age and gender of the patients, type of PNH, history of thrombosis, conditioning regimen used, source of stem cells, donor type, median day of engraftment, complications of transplant, rates of graft versus host disease, overall survival, and progression-free survival.
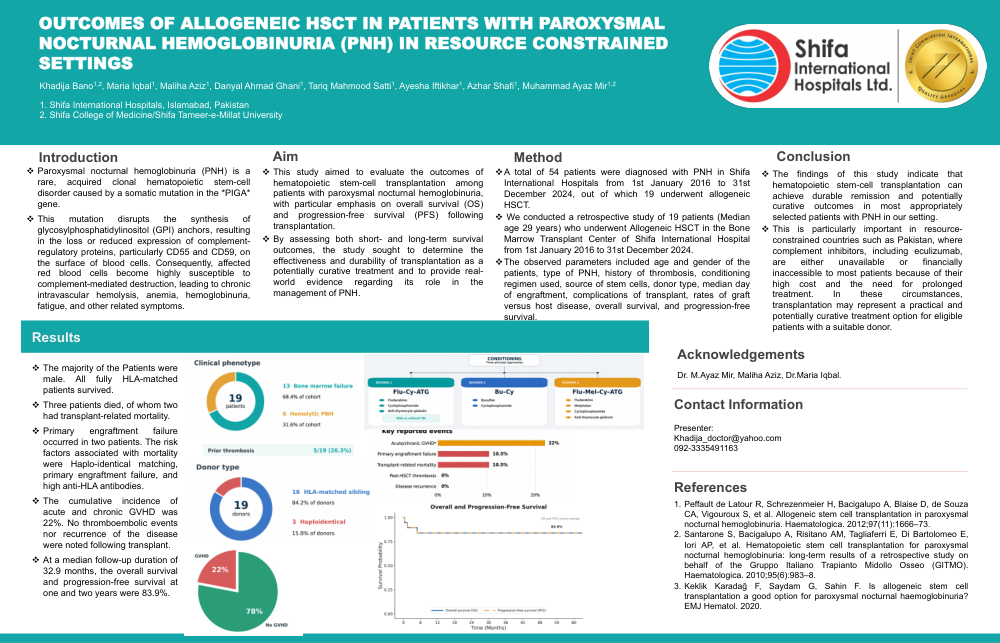
Results: The majority of the Patients were male. Thirteen patients had bone marrow failure syndrome, while six patients had hemolytic PNH. Five patients had a history of thrombosis. Sixteen donors were fully HLA-matched siblings, and three were haplo-identical matched. Engraftment was noted at a median of 13 days. The main conditioning regimens used were Flu-Cy-ATG with or without TBI, Bu-Cy, and Flu-Mel-Cy-ATG. . All fully HLA-matched patients survived. Three patients died, out of which two had transplant related mortality. Primary engraftment failure occurred in twopatients. The risk factors associated with mortality were Haplo-identical matching, primar engraftment failure and high anti HLA antibodies. The cumulative incidence of acute and chronic GVHD was 22%. No thromboembolic events nor recurrence of the disease were noted following transplant. At a median follow-up duration of 32.9 months, the overall survival and progression-free survival at one and two years were 83.9%.
Conclusion: The findings of this study confirm that most patients with PNH can be cured with hematopoietic stem cell transplantation in our settings as Complement inhibitors like Eculizumab is not available and unaffordable for our patients.
Keywords: Allogeneic HSCT, PNH, GVHD