516 posters, 59 topics, 63 sessions, 1,127 authors, 352 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
2026 SOAP Annual Meeting
April 29 - May 3, 2026 | Montreal, Quebec Canada

2339155
When Pain Relief Causes Pain: Morphine-Induced Sphincter of Oddi Spasm During Preterm Labor
Part of Topic
Challenging Blocks
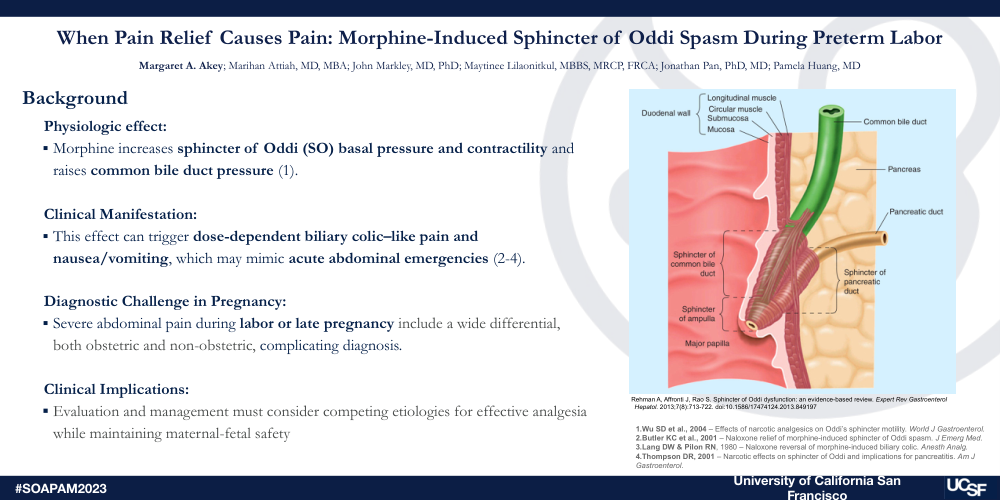
Background
Physiologic effect:
-
Morphine increases sphincter of Oddi (SO) basal pressure and contractility and raises common bile duct pressure (1).
Clinical Manifestation:
-
This effect can trigger dose-dependent biliary colic–like pain and nausea/vomiting, which may mimic acute abdominal emergencies (2-4).
Diagnostic Challenge in Pregnancy:
-
Severe abdominal pain during labor or late pregnancyinclude a wide differential, both obstetric and non-obstetric, complicating diagnosis.
Clinical Implications:
-
Evaluation and management must consider competing etiologies for effective analgesia while maintaining maternal-fetal safety
EKG: normal sinus rhythm
OB US: Growth ~34 weeks. No obvious abnormality concerning for abruption.Normal amniotic fluid.
Obstetric: Placental abruption, uterine rupture, preeclampsia/HELLP
Surgical: Post-Roux-en-Y gastric bypass complications, appendicitis
Medical: Pancreatitis, gastritis, medication-induced sphincter of Oddi spasmClinical Recognition
-
Rare complication of morphine administration
-
Presents with acute biliary-type pain, potentially mimicking obstetric or surgical emergencies
Diagnosis
-
Temporal relationship between morphine administration and symptom onset ~20 min post administration (2)
-
Exclusion of other causes (e.g. placental abruption, uterine rupture, surgical abdomen)
Risk Factors
-
Prior cholecystectomy reported as a risk factor in several studies and case report (5-7)
Management
-
Naloxone may relieve symptoms (2-3)
-
Use minimum effective dose to avoid opioid withdrawal and loss of labor analgesia
-
FDA reports possible risk with neuraxial morphine administration. No clinical cases reported. (8)