2,281 posters, 63 videos, 56 audios, 43 topics, 18 sessions, 6,174 authors, 2,323 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2025
June 23 - 25, 2025 | ExCeL London, UK
EP.0838
Giant Rapidly Expanding Ovarian Mass in a Multimorbid Patient: A Case Report
Poster Presenter
Authors
Affiliations
Warwick Medical School, Division of Biomedical Sciences, Clinical Sciences Research Laboratories, Warwick Medical School, University of Warwick, Coventry CV2 2DX, United Kingdom University Hospitals Coventry & Warwickshire, Coventry CV2 2DX, United Kingdom, University Hospitals Coventry & Warwickshire, Coventry CV2 2DX, United Kingdom Pan-Birmingham Gynaecological Cancer Centre, Sandwell and West Birmingham NHS Trust
Part of Topic
Gynaecological oncology
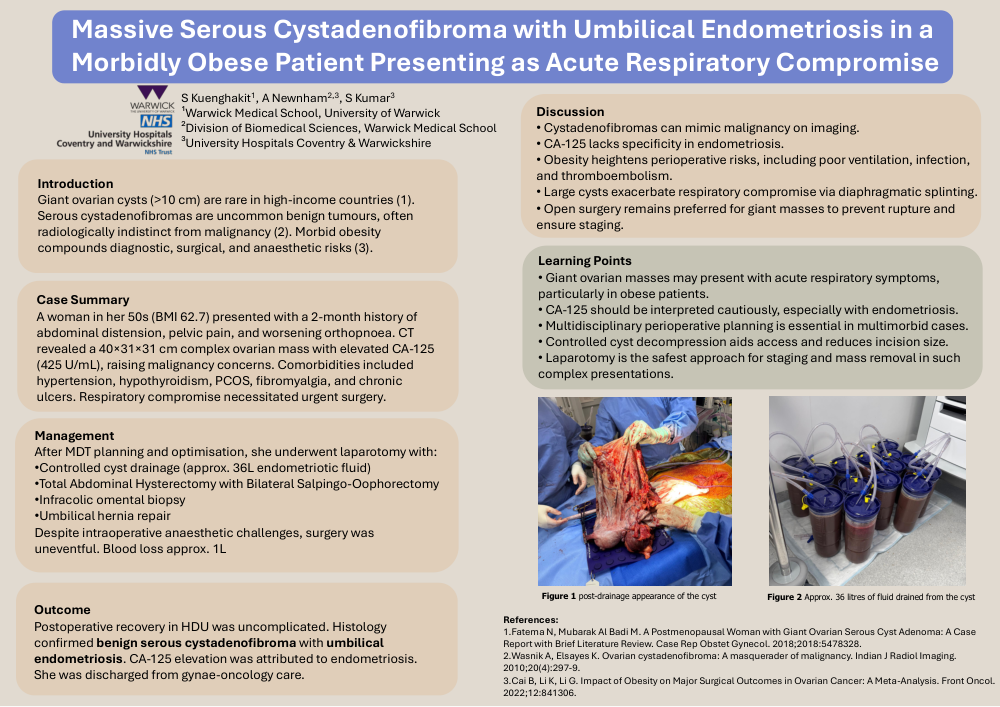
Massive Serous Cystadenofibroma with Umbilical Endometriosis in a Morbidly Obese Patient Presenting as Acute Respiratory Compromise
S Kuenghakit1, A Newnham2,3, S Kumar3
¹Warwick Medical School, University of Warwick
²Division of Biomedical Sciences, Warwick Medical School
³University Hospitals Coventry & Warwickshire
Introduction
Giant ovarian cysts (>10 cm) are rare in high-income countries (1). Serous cystadenofibromas are uncommon benign tumours, often radiologically indistinct from malignancy (2). Morbid obesity compounds diagnostic, surgical, and anaesthetic risks (3).
Case Summary
A woman in her 50s (BMI 62.7) presented with a 2-month history of abdominal distension, pelvic pain, and worsening orthopnoea. CT revealed a 40×31×31 cm complex ovarian mass with elevated CA-125 (425 U/mL), raising malignancy concerns. Comorbidities included hypertension, hypothyroidism, PCOS, fibromyalgia, and chronic ulcers. Respiratory compromise necessitated urgent surgery.
Management
After MDT planning and optimisation, she underwent laparotomy with:
Despite intraoperative anaesthetic challenges, surgery was uneventful. Blood loss approx. 1L
Outcome
Postoperative recovery in HDU was uncomplicated. Histology confirmed benign serous cystadenofibroma with umbilical endometriosis. CA-125 elevation was attributed to endometriosis. She was discharged from gynae-oncology care.
Discussion
Learning Points
Figure 1 post-drainage appearance of the cyst
Figure 2 Approx. 36 litres of fluid drained from the cyst
References: