2,281 posters, 63 videos, 56 audios, 43 topics, 18 sessions, 6,174 authors, 2,323 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2025
June 23 - 25, 2025 | ExCeL London, UK
EP.0816
HIGH GRADE (HGCIN) LESIONS AMONG HPV VACCINATED WOMEN
Poster Presenter
Authors
Affiliations
Part of Topic
Gynaecological oncology
HIGH GRADE (HGCIN) LESIONS AMONG HPV VACCINATED WOMEN
Miss G Majeed Guys and St Thomas NHS Foundation Trust
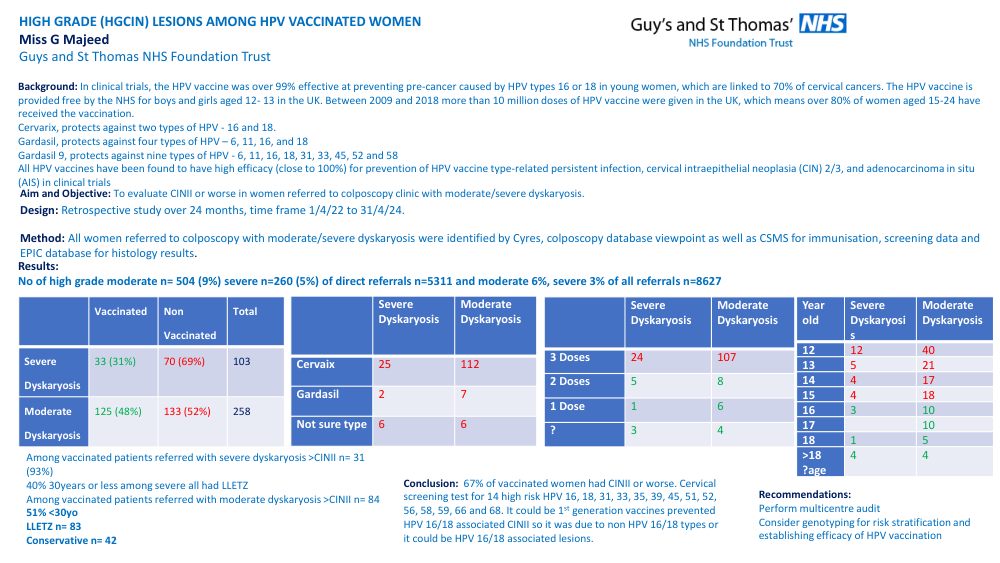
Background: In clinical trials, the HPV vaccine was over 99% effective at preventing pre-cancer caused by HPV types 16 or 18 in young women, which are linked to 70% of cervical cancers. The HPV vaccine is provided free by the NHS for boys and girls aged 12- 13 in the UK. Between 2009 and 2018 more than 10 million doses of HPV vaccine were given in the UK, which means over 80% of women aged 15-24 have received the vaccination.
Cervarix, protects against two types of HPV - 16 and 18.
Gardasil, protects against four types of HPV – 6, 11, 16, and 18
Gardasil 9, protects against nine types of HPV - 6, 11, 16, 18, 31, 33, 45, 52 and 58
All HPV vaccines have been found to have high efficacy (close to 100%) for prevention of HPV vaccine type-related persistent infection, cervical intraepithelial neoplasia (CIN) 2/3, and adenocarcinoma in situ (AIS) in clinical trials
Aim and Objective: To evaluate CINII or worse in women referred to colposcopy clinic with moderate/severe dyskaryosis. Design: Retrospective study over 24 months, time frame 1/4/22 to 31/4/24.
Method: All women referred to colposcopy with moderate/severe dyskaryosis were identified by Cyres, colposcopy database viewpoint as well as CSMS for immunisation, screening data and EPIC database for histology results. Results: No of high grade moderate n= 504 (9%) severe n=260 (5%) of direct referrals n=5311 and moderate 6%, severe 3% of all referrals n=8627
Conclusion: 67% of vaccinated women had CINII or worse. Cervical screening test for 14 high risk HPV 16, 18, 31, 33, 35, 39, 45, 51, 52, 56, 58, 59, 66 and 68. It could be 1st generation vaccines prevented HPV 16/18 associated CINII so it was due to non HPV 16/18 types or it could be HPV 16/18 associated lesions.
Recommendations:
Perform multicentre audit
Consider genotyping for risk stratification and establishing efficacy of HPV vaccination