2,281 posters, 63 videos, 56 audios, 43 topics, 18 sessions, 6,174 authors, 2,323 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2025
June 23 - 25, 2025 | ExCeL London, UK
EP.0813
Analysis of MRI and histopathology congruence and MMR status in endometrial cancer
Poster Presenter
Authors
Affiliations
Part of Topic
Gynaecological oncology
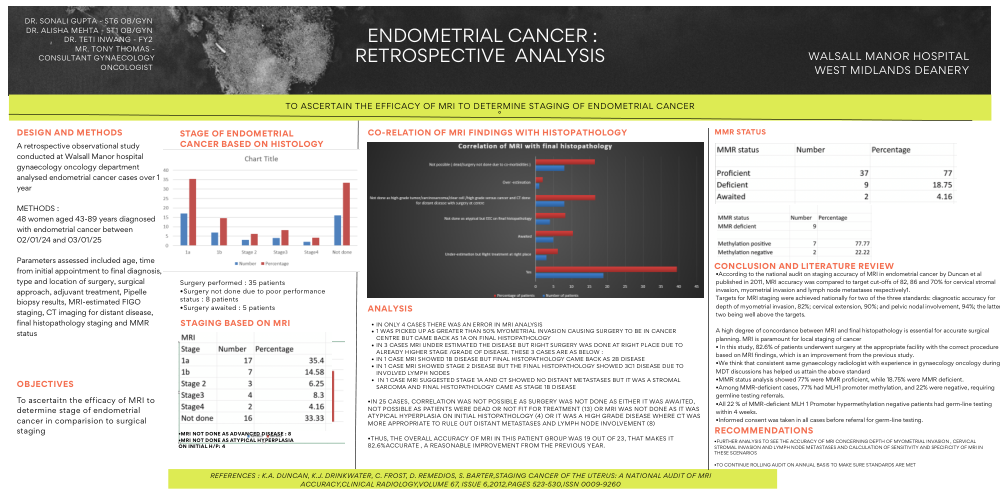
Endometrial cancer : retrospective analysis
According to the national audit on staging accuracy of MRI in endometrial cancer by Duncan et al published in 2011, MRI accuracy was compared to target cut-offs of 82, 86 and 70% for cervical stromal invasion, myometrial invasion and lymph node metastases respectively1.
Targets for MRI staging were achieved nationally for two of the three standards: diagnostic accuracy for depth of myometrial invasion, 82%; cervical extension, 90%; and pelvic nodal involvement, 94%; the latter two being well above the targets.
Statistical analysis demonstrated no significant difference in the use of intravenous contrast medium but did show some evidence of increasing accuracy in assessing the depth of myometrial invasion with growing caseload.
NICE Guidance G42 says that all patients with endometrial cancer should be offered testing on IHC for MMR status
If IHC is abnormal with loss of MLH1, or loss of both MLH1 and PMS2 protein expression, do MLH1 promoter hypermethylation testing of tumour DNA. If MLH1 promoter hypermethylation is not detected, offer germline genetic testing to confirm Lynch syndrome.
If IHC is abnormal with loss of MSH2, MSH6 or isolated PMS2 protein expression, offer germline genetic testing to confirm Lynch syndrome.