2,281 posters, 63 videos, 56 audios, 43 topics, 18 sessions, 6,174 authors, 2,323 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2025
June 23 - 25, 2025 | ExCeL London, UK
EP.1786
Addressing potential challenges in postoperative management of transverse vaginal septum
Poster Presenter
Authors
Affiliations
Part of Topic
Paediatric & adolescent gynaecology
Objective:Transverse vaginal septum(TVS) is a rare Mullerian anamoly with incidence 1/2100-1/7200.Variability in the position, thickness,and orientation of TVS poses diagnostic and maagement challenges.
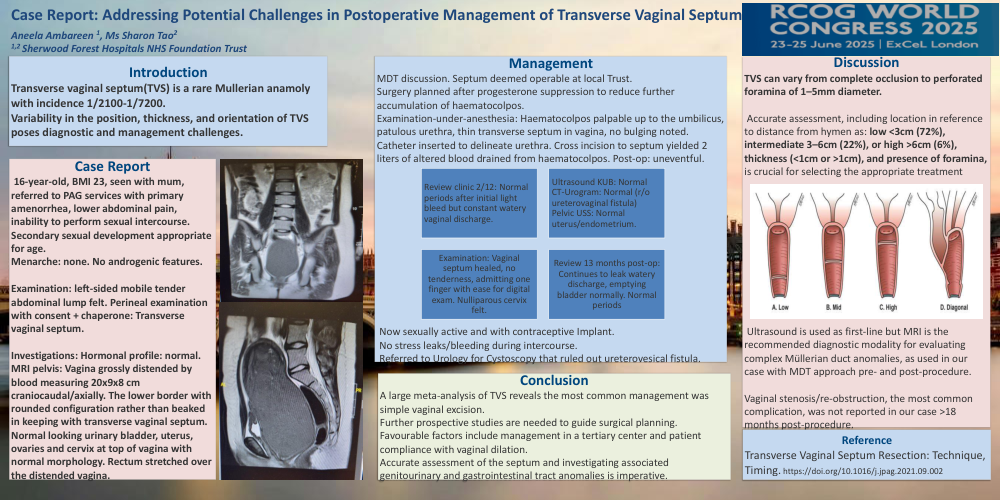
Case report:16yrsold,BMI23,seen with mum,referred to PAG services with primary amenorrhea,lower abdominal pain,inability to perform sexual intercourse.Secondary sexual development:Appropriate for age,Menarche:None.No androgenic features.Upon-examination:left-sided mobile tender abdominal lump felt.Perineal examination with consent+chaperone:Transverse vaginal septum.Hormonal profile:normal.MRI pelvis:Vagina grossly distended by blood measuring 20x9x8cm crano-caudal/axially.The lower border with rounded configuration rather than beaked in keeping with transverse vaginal septum. Normal looking urinary bladder,uterus,ovaries and cervix at top of vagina normal morphology.Rectum stretched over the distended vagina.Septum deemed operable at local Trust after
MDT discussion.Surgery planned after progesterone suppression to further accumulation of haematocolpos.Examination-under-anesthesia:Hamematocolpos palpable upto the umbilicus,patulous urethera,thin transverse septum in vagina,no bulging noted.Catheter inserted to delineate urethera.Cross incision to septum yielded 2 liters of altered blood drained from haematocolpos.Review clinic 2/12.Reported normal periods after initial light bleed but constant watery vaginal discharge of concern.Ultrasound KUB and CT-Urogram requested to assess for ureterovaginal fistula and review in clinic.Both investigations normal.Pelvic USS:Normal uterus/endometrium.Examination:Vaginal septum healed,no tenderness,admitting one finger with ease for digital exam.Nulliparous cervix felt.Impression:Likely mucus secondary to massive hematometra.Follow-up13 months post-op:Continues to leak watery discharge,emptying bladder normally.Normal periods.Now sexually active and with contraceptive Implant.No stress leaks/bleeding during intercourse.Referred to Urology for Cystoscopy that ruled out ureterovesical fistula.Ongoing discussion at Urogynae MDT:For moon cap testing of vaginal fluid.
Discussion:TVS can vary from complete occlusion to perforated foramina of 1–5mm diameter.Accurate assessment,including location in reference to distance from hymen as low <3cm(72%),intermediate 3-6cm(22%),or high>6cm (6%),thickness(<1cm or>1cm),and presence of foramina,is crucial for selecting the appropriate treatment.Ultrasound used as first-line but MRI is the recommended diagnostic modality for evaluating complex Müllerian duct anomalies as used in our case with MDT approach pre&post-procedure.Vaginal stenosis/re-obstruction as the commonest complication,was not reported in our case >18months post procedure.
Conclusion:A large metanalysis of TVS reveals the most common management was simple vaginal excision.Further prospective studies are needed to guide surgical planning.Favourable factors are management in a tertiary center and patient-compliance with vaginal dilation.Accurate assessment of the septum and investigating associated genitourinary and gastrointestinal tract anomalies isimperative.https://doi.org/10.1016/j.jpag.2021.09.002Transverse Vaginal Septum Resection:Technique,Timing,