301 posters, 50 videos, 13 topics, 13 sessions, 734 authors, 193 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2026 Annual Meeting
10 - 13 June, 2026 | Miami, Florida

D173
Sixteen Years Of Experience In Performing Midcab Procedure
Poster Presenter
Authors
Part of Topic
Coronary Revascularization
Sixteen Years Of Experience In Performing MIDCAB Procedure
Vadim A. Popov, Kirill A. Kozirin, Maksim M. Anishenko, Egor S. Malyshenko, Amiran Sh. Revishvili
A.V. Vishnevsky National Medical Research Center of Surgery, Moscow, Russian Federation.
Objective: To analyze results of MIDCAB procedure in patients with isolated LAD stenosis for 16 years.
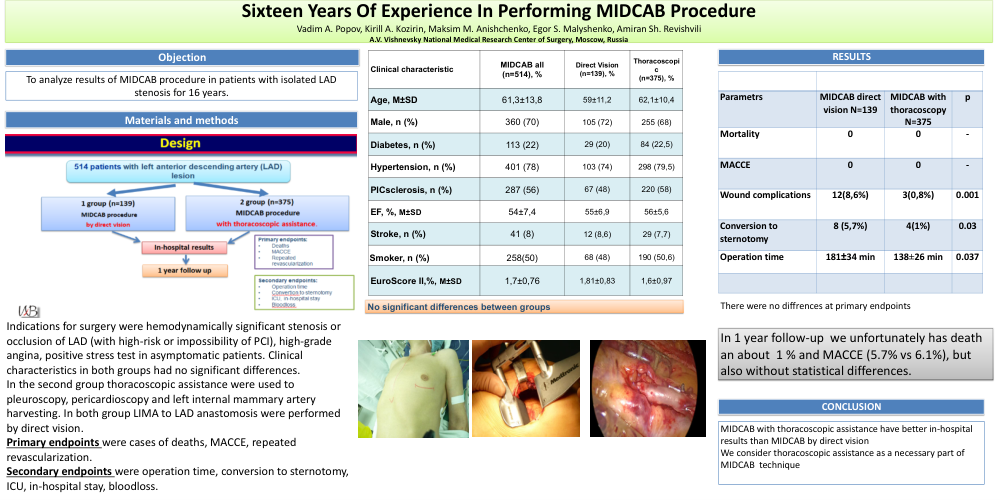
Methods: In a retrospective study of a cohort of 514 patients with isolated LAD lesion, we compared the standard MIDCAB procedure in a group of 139 patients and MIDCAB in a group of 375 patients with thoracoscopic assistance. Indications for surgery were hemodynamically significant stenosis or occlusion of LAD (with high-risk or impossibility of PCI), high-grade angina, positive stress test in asymptomatic patients. Clinical characteristics in both groups had no significant differences. In the second group thoracoscopic assistance were used to pleuroscopy, pericardioscopy and left internal mammary artery harvesting. In both group LIMA to LAD anastomosis were performed by direct vision. Primary endpoints were cases of deaths, MACCE, repeated revascularization. Secondary endpoints were operation time, conversion to sternotomy, ICU, in-hospital stay, bloodloss.
Results. There were no cases of deaths, MACCE, repeated revascularization in the in-hospital period. The average in-hospital stay was 7 or 8 days, blood loss was 240±57ml, ICU stay-6 ± 3.9 hrs. There were no differences at primary endpoints, but our results has demonstrate statistical differences in in-hospital and 1-month follow up results: operation time in the 2nd group was shorter -181±34 min in the 1st group and 138±26 min in the 2nd group.
In-hospital stay the incidence of wound complications were 12(8.6%) cases in the 1st group (caused by retraction injury) and 3(0,8%) cases in the 2nd group (p=0,001). There were 8(5.7%) conversions to sternotomy in the 1st group, mainly because of LIMA damage, and 4(1%) conversions in the 2nd group. We supposed that the difference in conversions rate were caused by better thoracoscopic visualization. In 1 year follow-up we unfortunately has death an about 1 % and MACCE (5.7% vs 6.1%), but also without statistical differences.
Conclusions: MIDCAB with thoracoscopic assistance have better in-hospital results than MIDCAB by only direct vision.