301 posters, 50 videos, 13 topics, 13 sessions, 734 authors, 193 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2026 Annual Meeting
10 - 13 June, 2026 | Miami, Florida

P120
Fibrillatory Arrest Vs. Cardioplegic Arrest In Redo Mitral Surgery
Poster Presenter
Authors
Affiliations
Part of Topic
Valve � Surgical Valves
Fibrillatory Arrest vs. Cardioplegic Arrest in Redo Mitral Surgery: A Propensity-Matched Comparative Analysis
Objective
To compare outcomes of redo mitral valve surgery performed using fibrillatory arrest versus conventional cardioplegic arrest through unmatched, 1:1, and 1:2 propensity-matched analyses.
Methods
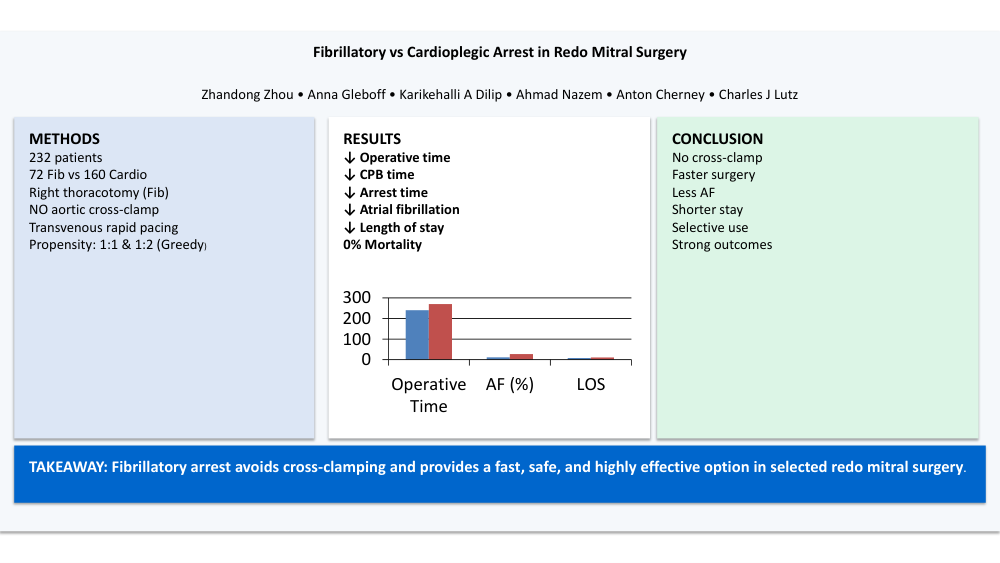
We reviewed 232 patients undergoing redo mitral valve surgery over five years at a single center. Seventy-two patients underwent surgery with fibrillatory arrest (Fib group) and 160 with cardioplegic arrest (Non-Fib group). Fibrillatory arrest was achieved via transvenous rapid pacing, avoiding aortic cross-clamping, and all procedures were performed through a minimally invasive right thoracotomy. Most cardioplegic cases used repeat sternotomy. Propensity score matching (1:1 and 1:2) was performed using Greedy nearest-neighbor matching with a caliper of 0.2 on the propensity score. Matching variables included age, sex, BMI, predicted risk of mortality, and CPB time. Outcomes were compared using chi-square and unpaired t-tests.
Results
In the unmatched cohort, the Fib group had shorter Operative Times (242 Vs 267 mins, P=0.14), CPB times (132 vs 145 min, P=0.049), Heart arrest times (87.9 vs 96.5 min, P=0.029), and hospital stay (8.3 vs 11.0 days, P=0.040), less atrial fibrillation (12.5% vs 27.1%, P=0.030) but a higher pacemaker rate (8.3% vs 2.0%, P=0.027).
In the 1:1 matched cohort, the Fib group showed reduced Operative times (239 vs 280 min, P=0.0025), CPB times (131 vs 147 min, P=0.0569), heart arrest times (87.1 vs 96.5 min, P=0.067), lower atrial fibrillation (10.3% vs 27.9%, P=0.0165), with comparable mortality and complications.
The 1:2 matched analysis confirmed these findings: shorter procedure times (242 vs 264 min, P=0.0295), CPB times (132 vs 144 min, P=0.0587), heart arrest times (88 Vs 97 mins, P=0,027) lower atrial fibrillation (12.5% vs 27.1%, P=0.024).
The higher pacemaker rate in the Fib group reflects pre-existing conduction disease rather than procedural injury.
Conclusions
Redo mitral surgery using fibrillatory arrest via transvenous rapid pacing and minimally invasive thoracotomy—without aortic cross-clamping—offers reduced operative time, bypass duration, heart arrest time, CPB time, atrial fibrillation, and hospital stay. These advantages, demonstrated across unmatched and matched comparisons, support fibrillatory arrest as a safe, efficient strategy for re operative mitral patients.