301 posters, 50 videos, 13 topics, 13 sessions, 734 authors, 193 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2026 Annual Meeting
10 - 13 June, 2026 | Miami, Florida

D102
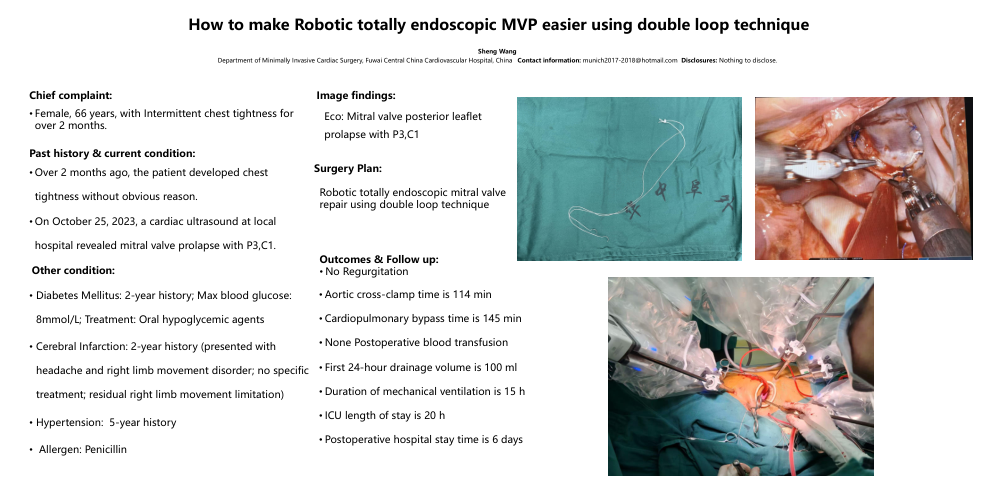
How To Make Robotic Totally Endoscopic Mvp Easier Using Double Loop Technique
Poster Presenter
Authors
Affiliations
Part of Topic
Valve � Surgical Valves
Video
How to make Robotic totally endoscopic MVP easier using double loop technique(Sheng Wang Department of Minimally Invasive Cardiac Surgery, Fuwai Central China Cardiovascular Hospital, China Contact information: munich2017-2018@hotmail.com)
Chief complaint:
Female, 66 years, with Intermittent chest tightness for over 2 months.
Past history & current condition:
Over 2 months ago, the patient developed chest tightness without obvious reason. On October 25, 2023, a cardiac ultrasound at local hospital revealed mitral valve prolapse with P3,C1.
Other condition:
Diabetes Mellitus: 2-year history; Max blood glucose: 8mmol/L; Treatment: Oral hypoglycemic agents Cerebral Infarction: 2-year history (presented with headache and right limb movement disorder; no specific treatment; residual right limb movement limitation) Hypertension: 5-year history Allergen: Penicillin
Image findings:
Eco: Mitral valve posterior leaflet prolapse with P3,C1
Surgery Plan:
Robotic totally endoscopic mitral valve repair using double loop technique
Outcomes & Follow up:
No Regurgitation
Aortic cross-clamp time is 114 min Cardiopulmonary bypass time is 145 min None Postoperative blood transfusion First 24-hour drainage volume is 100 ml Duration of mechanical ventilation is 15 h ICU length of stay is 20 h Postoperative hospital stay time is 6 days