301 posters, 50 videos, 13 topics, 13 sessions, 734 authors, 193 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2026 Annual Meeting
10 - 13 June, 2026 | Miami, Florida

P115
An Innovative Minimally Invasive Electroseptal Myectomy For Obstructive Hypertrophic Cardiomyopathy With A Small Aortic Root
Poster Presenter
Part of Topic
Valve � Surgical Valves
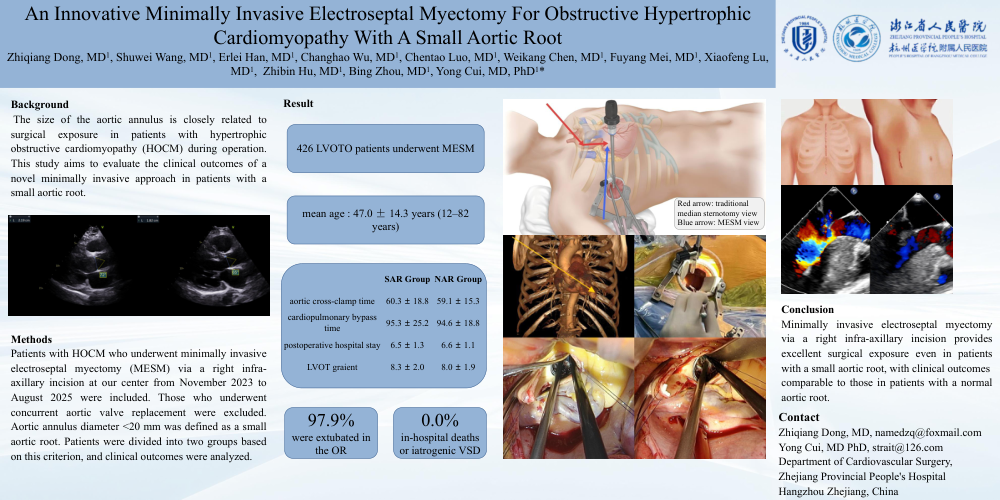
Background: The size of the aortic annulus is closely related to surgical exposure in patients with hypertrophic obstructive cardiomyopathy (HOCM) during operation. This study aims to evaluate the clinical outcomes of a novel minimally invasive approach in patients with a small aortic root.
Methods: Patients with HOCM who underwent minimally invasive electroseptal myectomy (MESM) via a right infra-axillary incision at our center from November 2023 to August 2025 were included. Those who underwent concurrent aortic valve replacement were excluded. Aortic annulus diameter <20 mm was defined as a small aortic root. Patients were divided into two groups based on this criterion, and clinical outcomes were analyzed.
Results: A total of 426 patients were included, with a mean age of 47.0 ± 14.3 years (range 12–82 years). All procedures were successfully completed via a 4–5 cm right infra-axillary incision without conversion to sternotomy. Seventy-one patients with an aortic annulus <20 mm were assigned to the small aortic root (SAR) group. No significant differences were observed between the SAR group and the normal aortic root (NAR) group in mean aortic cross-clamp time (60.3 ± 18.8 vs. 59.1 ± 15.3 minutes, P = 0.63), cardiopulmonary bypass time (95.3 ± 25.2 vs. 94.6 ± 18.8 minutes, P = 0.81), or postoperative hospital stay (6.5 ± 1.3 vs. 6.6 ± 1.1 days, P = 0.37). Immediate extubation in the operating room was achieved in 417 patients (97.9%), including all 71 patients in the SAR group (P = 0.18). Mitral valve replacement was performed in 14 patients (3.3%). Complete relief of obstruction was achieved in all patients. The mean postoperative left ventricular outflow tract gradient was 8.3 ± 2.0 mmHg in the SAR group and 8.0 ± 1.9 mmHg in the NAR group (P = 0.16). Systolic anterior motion of the mitral valve was completely resolved. There were no in-hospital deaths or procedure-related ventricular septal defects.
Conclusion: Minimally invasive electroseptal myectomy via a right infra-axillary incision provides excellent surgical exposure even in patients with a small aortic root, with clinical outcomes comparable to those in patients with a normal aortic root.