293 posters, 56 videos, 24 topics, 13 sessions, 658 authors, 215 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2025 Annual Meeting
28 - 31 May, 2025 | Istanbul, Turkey

D156
3-d Endoscopic Mitral Valve Repair In A Patient With Mitral Regurgitation Caused By Papillary Muscle Rupture After Acute Myocardial Infarction
Poster Presenter
Authors
Affiliations
null,
Part of Topic
Valve – Surgical Valves
3-d Endoscopic Mitral Valve Repair In A Patient With Mitral Regurgitation Caused By Papillary Muscle Rupture After Acute Myocardial Infarction
Sheng Wang1; Zhao Li1; Guoqing Lu1
1Fuwai Central China Cardiovascular Hospital (Central China Fuwai Hospital of Zhengzhou University), Zhengzhou, China
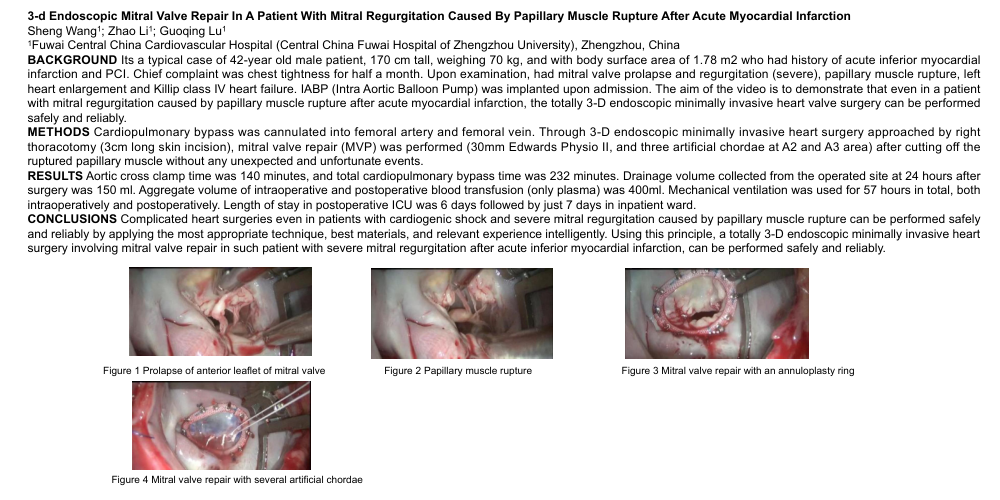
BACKGROUND Its a typical case of 42-year old male patient, 170 cm tall, weighing 70 kg, and with body surface area of 1.78 m2 who had history of acute inferior myocardial infarction and PCI. Chief complaint was chest tightness for half a month. Upon examination, had mitral valve prolapse and regurgitation (severe), papillary muscle rupture, left heart enlargement and Killip class IV heart failure. IABP (Intra Aortic Balloon Pump) was implanted upon admission. The aim of the video is to demonstrate that even in a patient with mitral regurgitation caused by papillary muscle rupture after acute myocardial infarction, the totally 3-D endoscopic minimally invasive heart valve surgery can be performed safely and reliably.
METHODS Cardiopulmonary bypass was cannulated into femoral artery and femoral vein. Through 3-D endoscopic minimally invasive heart surgery approached by right thoracotomy (3cm long skin incision), mitral valve repair (MVP) was performed (30mm Edwards Physio II, and three artificial chordae at A2 and A3 area) after cutting off the ruptured papillary muscle without any unexpected and unfortunate events.
RESULTS Aortic cross clamp time was 140 minutes, and total cardiopulmonary bypass time was 232 minutes. Drainage volume collected from the operated site at 24 hours after surgery was 150 ml. Aggregate volume of intraoperative and postoperative blood transfusion (only plasma) was 400ml. Mechanical ventilation was used for 57 hours in total, both intraoperatively and postoperatively. Length of stay in postoperative ICU was 6 days followed by just 7 days in inpatient ward.
CONCLUSIONS Complicated heart surgeries even in patients with cardiogenic shock and severe mitral regurgitation caused by papillary muscle rupture can be performed safely and reliably by applying the most appropriate technique, best materials, and relevant experience intelligently. Using this principle, a totally 3-D endoscopic minimally invasive heart surgery involving mitral valve repair in such patient with severe mitral regurgitation after acute inferior myocardial infarction, can be performed safely and reliably.