225 posters, 34 videos, 18 topics, 14 sessions, 251 authors, 55 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2024 Annual Meeting
29 May - 1 June, 2024 | Athens, Greece

PC.60
Midterm Outcomes For Funnel Evar: Practical, Effective And Safe
Poster Presenter
Authors
Part of Topic
Endovascular and Aortic Surgery
Abstract
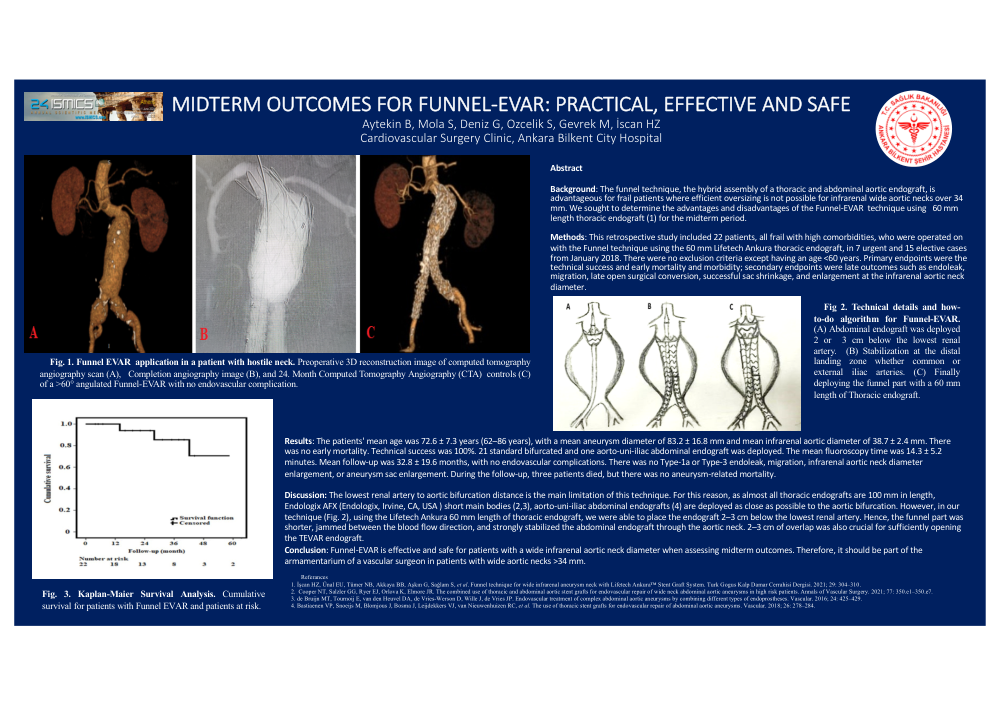
Background: The funnel technique, the hybrid assembly of a thoracic and abdominal aortic endograft, is advantageous for frail patients where efficient oversizing is not possible for infrarenal wide aortic necks over 34 mm. We sought to determine the advantages and disadvantages of the Funnel-EVAR technique using 60 mm length thoracic endograft (1) for the midterm period.
Methods: This retrospective study included 22 patients, all frail with high comorbidities, who were operated on with the Funnel technique using the 60 mm Lifetech Ankura thoracic endograft, in 7 urgent and 15 elective cases from January 2018. There were no exclusion criteria except having an age <60 years. Primary endpoints were the technical success and early mortality and morbidity; secondary endpoints were late outcomes such as endoleak, migration, late open surgical conversion, successful sac shrinkage, and enlargement at the infrarenal aortic neck diameter.
Results: The patients' mean age was 72.6 ± 7.3 years (62–86 years), with a mean aneurysm diameter of 83.2 ± 16.8 mm and mean infrarenal aortic diameter of 38.7 ± 2.4 mm. There was no early mortality. Technical success was 100%. 21 standard bifurcated and one aorto-uni-iliac abdominal endograft was deployed. The mean fluoroscopy time was 14.3 ± 5.2 minutes. Mean follow-up was 32.8 ± 19.6 months, with no endovascular complications. There was no Type-1a or Type-3 endoleak, migration, infrarenal aortic neck diameter enlargement, or aneurysm sac enlargement. During the follow-up, three patients died, but there was no aneurysm-related mortality.
Discussion: The lowest renal artery to aortic bifurcation distance is the main limitation of this technique. For this reason, as almost all thoracic endografts are 100 mm in length, Endologix AFX (Endologix, Irvine, CA, USA ) short main bodies (2,3), aorto-uni-iliac abdominal endografts (4) are deployed as close as possible to the aortic bifurcation. However, in our technique (Fig. 2), using the Lifetech Ankura 60 mm length of thoracic endograft, we were able to place the endograft 2–3 cm below the lowest renal artery. Hence, the funnel part was shorter, jammed between the blood flow direction, and strongly stabilized the abdominal endograft through the aortic neck. 2–3 cm of overlap was also crucial for sufficiently opening the TEVAR endograft.
Conclusion: Funnel-EVAR is effective and safe for patients with a wide infrarenal aortic neck diameter when assessing midterm outcomes. Therefore, it should be part of the armamentarium of a vascular surgeon in patients with wide aortic necks >34 mm.