225 posters, 34 videos, 18 topics, 14 sessions, 251 authors, 55 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2024 Annual Meeting
29 May - 1 June, 2024 | Athens, Greece

D.113
First Reported Series Of Endoscopic Transposition Of The Anterior Mitral Leaflet As A Patch For Posterior Annular Mac Debridement
Poster Presenter
Authors
Part of Topic
Valve - Surgical Valves
Video
First Reported Series Of Endoscopic Transposition Of The Anterior Mitral Leaflet As A Patch For Posterior Annular Mac Debridement Author Block: Mario Castillo-Sang, Mickey Ising, George Christensen.
St. Elizabeth Healthcare, Edgewood, KY, USA.
Abstract:
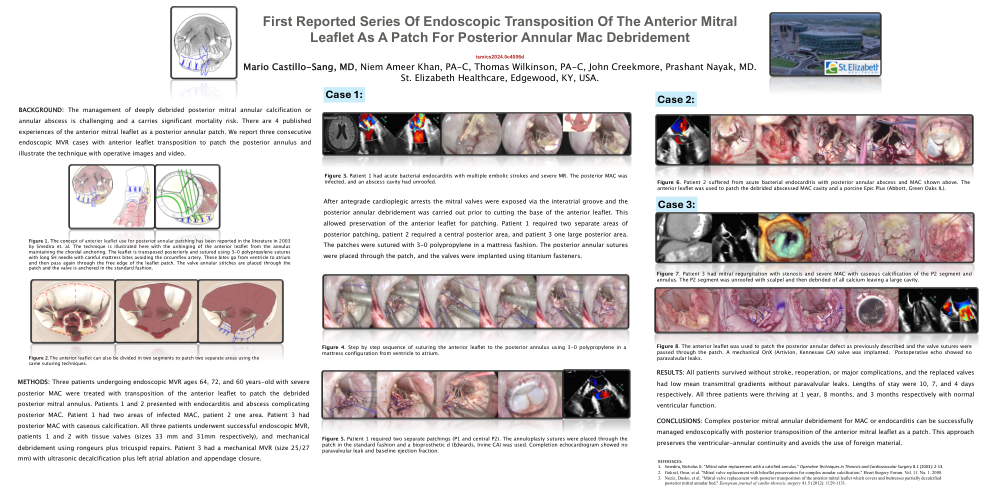
BACKGROUND: The management of deeply debrided posterior mitral annular calcification or annular abscess is challenging and a carries significant mortality risk. There are 4 published experiences of the anterior mitral leaflet as a posterior annular patch. We report three consecutive endoscopic MVR cases with anterior leaflet transposition to patch the posterior annulus and illustrate the technique with operative images and video. METHODS: Three patients undergoing endoscopic MVR ages 64, 72, and 60 years-old with severe posterior MAC were treated with transposition of the anterior leaflet to patch the debrided posterior mitral annulus. Patients 1 and 2 presented with endocarditis and abscess complicating posterior MAC. Patient 1 had two areas of infected MAC, patient 2 one area. Patient 3 had posterior MAC with caseous calcification. All three patients underwent successful endoscopic MVR, patients 1 and 2 with tissue valves (sizes 33 mm and 31mm respectively), and mechanical debridement using rongeurs plus tricuspid repairs. Patient 3 had a mechanical MVR (size 25/27 mm) with ultrasonic decalcification plus left atrial ablation and appendage closure. After antegrade cardioplegic arrests the mitral valves were exposed via the interatrial groove and the posterior annular debridement was carried out prior to cutting the base of the anterior leaflet. This allowed preservation of the anterior leaflet for patching. Patient 1 required two separate areas of posterior patching, patient 2 required a central posterior area, and patient 3 one large posterior area. The patches were sutured with 3-0 polypropylene in a mattress fashion. The posterior annular sutures were placed through the patch, and the valves were implanted using titanium fasteners. RESULTS: All patients survived without stroke, reoperation, or major complications, and the replaced valves had low mean transmitral gradients without paravalvular leaks. Lengths of stay were 10, 7, and 4 days respectively. All three patients were thriving at 1 year, 8 months, and 3 months respectively with normal ventricular function. CONCLUSIONS:Complex posterior mitral annular debridement for MAC or endocarditis can be successfully managed endoscopically with posterior transposition of the anterior mitral leaflet as a patch. This approach preserves the ventricular-annular continuity and avoids the use of foreign material.
Figure 1. The concept of anterior leaflet use for posterior annular patching has been reported in the literature in 2003 by Smedira et. al. The technique is illustrated here with the unhinging of the anterior leaflet from the annulus maintaining the chordal anchoring. The leaflet is transposed posteriorly and sutured using 3-0 polypropylene sutures with long SH needle with careful mattress bites avoiding the circumflex artery. These bites go from ventricle to atrium and then pass again through the free edge of the leaflet patch. The valve annular stitches are placed through the patch and the valve is anchored in the standard fashion.
Figure 2.The anterior leaflet can also be divided in two segments to patch two separate areas using the same suturing techniques.
Figure 3. Patient 1 had acute bacterial endocarditis withmultiple embolic strokes and severe MR. The posterior MAC was infected, and an abscess cavity had unroofed.
Figure 4. Step by step sequence of suturing the anterior leaflet to the posterior annulus using 3-0 polypropylene in a mattress configuration from ventricle to atrium.
Figure 5. Patient 1 required two separate patchings (P1 and central P2). The annuloplasty sutures were placed through the patch in the standard fashion and a bioprosthetic d (Edwards, Irvine CA) was used. Completion echocardiogram showed no paravalvular leak and baseline ejection fraction.
Figure 6. Patient 2 suffered from acute bacterial endocarditis with posterior annular abscess and MAC shown above. The anterior leaflet was used to patch the debrided abscessed MAC cavity and a porcine Epic Plus (Abbott, Green Oaks IL).
Figure 7. Patient 3 had mitral regurgitation with stenosis and severe MAC with caseous calcification of the P2 segment and annulus. The P2 segment was unroofed with scalpel and then debrided of all calcium leaving a large cavity.
Figure 8. The anterior leaflet was used to patch the posterior annular defect as previously described and the valve sutures were passed through the patch. A mechanical OnX (Artivion, Kennesaw GA) valve was implanted. Postoperative echo showed no paravalvular leaks.
REFERENCES: