225 posters, 34 videos, 18 topics, 14 sessions, 251 authors, 55 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2024 Annual Meeting
29 May - 1 June, 2024 | Athens, Greece

D.102
Minithoracotomy Approach For Mitral Valve Redo Surgery
Poster Presenter
Authors
Part of Topic
Valve - Surgical Valves
Minithoracotomy approach for mitral valve REDO surgery
Objective: Redo cardiac surgery through median sternotomy still represents a challenge procedure due to the high risk of graft injuries, the presence of dense adhesions and complex valve exposure. The use of a minithoracotomy approach may reduce the surgical complexity. We report our experience performing redo mitral valve surgery through a right-sided mini-thoracotomy.
Methods: From march 2010 to November 2023, 64 patients (Median age 68 years (IQR 56-76) and 39% females) underwent redo mitral valve surgery through right anterior thoracotomy at our institution. Median EuroSCORE II was 3.83 (IQR 2.53-7.22).
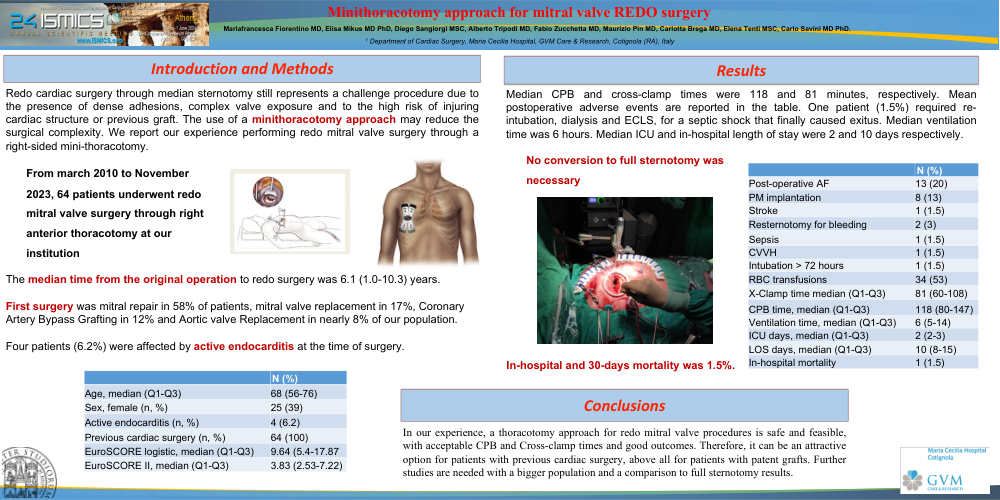
Results: The median time from the original operation to redo surgery was 6.1 (1.0-10.3) years. First surgery was mitral repair in 58% of patients, mitral valve replacement in 17%, Coronary Artery Bypass Grafting in 12% and Aortic valve Replacement in nearly 8% of our population. Four patients (6.2%) were affected by active endocarditis at the time of surgery. Median cardiopulmonary bypass and cross-clamp times were 118 (IQR 80-147) minutes and 81 (IQR 60-108) minutes, respectively. No conversion to full sternotomy was necessary. Thirty-four (53%) required transfusions with packed blood cells. Post-operative atrial fibrillation was observed in 13 patients (20%) and 8 patient (13%) required Pace-maker implantation due to third degree AV block. Moreover, we observed 2 rethoracotomy for bleeding (3%), and 1 stroke (1.5%). One patient (1.5%) required re-intubation, dialysis and Extracorporeal Life Support, for a septic shock that finally caused exitus. Median ventilation time was 6 hours (IQR 5-14). Median ICU and in-hospital length of stay were 2 (IQR 2-3) days and 10 (IQR 8-15) days respectively. In-hospital and 30-days mortality was 1.5%.
Conclusions: In our experience, a thoracotomy approach for redo mitral valve procedures is safe and feasible, with acceptable CPB and Cross-clamp times and good outcomes. Therefore, it can be an attractive option for patients with previous cardiac surgery, above all for patients with patent grafts. Further studies are needed with a bigger population and a comparison to full sternotomy results.