501 posters, 2 videos, 1 audios, 8 topics, 37 sessions, 395 authors, 307 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
23rd Annual Pain Medicine Meeting 2024
November 21-23, 2024 | Caesars Palace, Las Vegas, Nevada

5975
RESCUE BLOCK WITH INTERCOSTAL NERVE BLOCK FOLLOWING SERRATUS ANTERIOR PLANE BLOCK FOR MULTIPLE RIB FRACTURES
Poster Presenter
Authors
Affiliations
Part of Topic
Medically Challenging Cases
Rescue Block with Intercostal Nerve Block Following Serratus Anterior Plane Block for Multiple Rib Fractures
Andrew Ryu, M.D. 1, Jin Yoo, M.D.1, Oktay Shuminov, M.D. 1
1Northwell Health, Bay Shore, NY, 11706
Background
Multimodal management of rib fracture pain has become the gold standard of care in many institutions to optimize pain analgesia as well as to avoid the overuse of opioid medications. Patients with rib fractures can receive analgesia via various regional anesthetic procedures, including thoracic epidural, paravertebral block, erector spinae plane, serratus anterior plane (SAP), and intercostal nerve (ICN) block.
An SAP block is a relatively safe procedure that serves to block multilevel intercostal nerves along the angle of the rib. However, there is a paucity of prospective studies on its efficacy in multiple rib fractures. The SAP block is done with the patient in supine position with abduction of the arm. The needle can be inserted at the mid-axillary line targeting the rib under the serratus anterior.
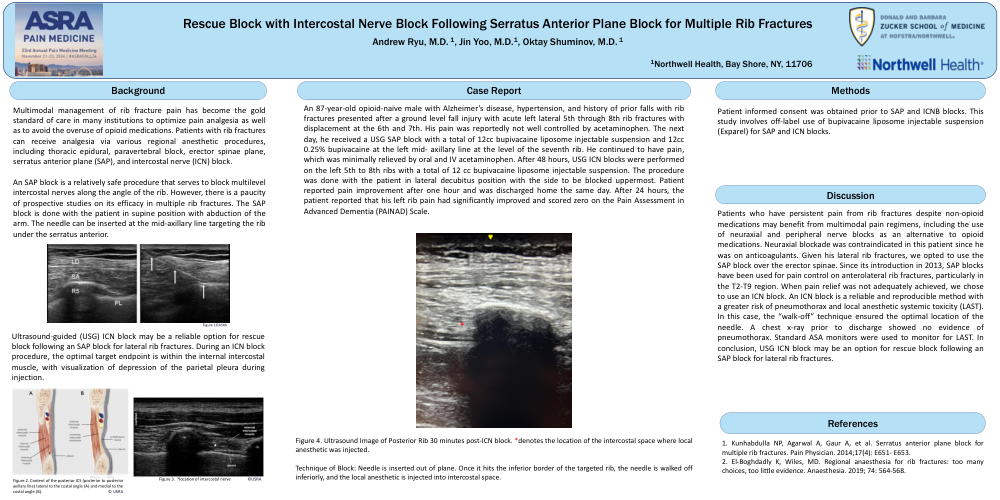
Ultrasound-guided (USG) ICN block may be a reliable option for rescue block following an SAP block for lateral rib fractures. During an ICN block procedure, the optimal target endpoint is within the internal intercostal muscle, with visualization of depression of the parietal pleura during injection.
Case Report
An 87-year-old opioid-naive male with Alzheimer’s disease, hypertension, and history of prior falls with rib fractures presented after a ground level fall injury with acute left lateral 5th through 8th rib fractures with displacement at the 6th and 7th. His pain was reportedly not well controlled by acetaminophen. The next day, he received a USG SAP block with a total of 12cc bupivacaine liposome injectable suspension and 12cc 0.25% bupivacaine at the left mid- axillary line at the level of the seventh rib. He continued to have pain, which was minimally relieved by oral and IV acetaminophen. After 48 hours, USG ICN blocks were performed on the left 5th to 8th ribs with a total of 12 cc bupivacaine liposome injectable suspension. The procedure was done with the patient in lateral decubitus position with the side to be blocked uppermost. Patient reported pain improvement after one hour and was discharged home the same day. After 24 hours, the patient reported that his left rib pain had significantly improved and scored zero on the Pain Assessment in Advanced Dementia (PAINAD) Scale.
Technique of Block: Needle is inserted out of plane. Once it hits the inferior border of the targeted rib, the needle is walked off inferiorly, and the local anesthetic is injected into intercostal space.
Methods
Patient informed consent was obtained prior to SAP and ICNB blocks. This study involves off-label use of bupivacaine liposome injectable suspension (Exparel) for SAP and ICN blocks.
Discussion
Patients who have persistent pain from rib fractures despite non-opioid medications may benefit from multimodal pain regimens, including the use of neuraxial and peripheral nerve blocks as an alternative to opioid medications. Neuraxial blockade was contraindicated in this patient since he was on anticoagulants. Given his lateral rib fractures, we opted to use the SAP block over the erector spinae. Since its introduction in 2013, SAP blocks have been used for pain control on anterolateral rib fractures, particularly in the T2-T9 region. When pain relief was not adequately achieved, we chose to use an ICN block. An ICN block is a reliable and reproducible method with a greater risk of pneumothorax and local anesthetic systemic toxicity (LAST). In this case, the “walk-off” technique ensured the optimal location of the needle. A chest x-ray prior to discharge showed no evidence of pneumothorax. Standard ASA monitors were used to monitor for LAST. In conclusion, USG ICN block may be an option for rescue block following an SAP block for lateral rib fractures.
References
1. Kunhabdulla NP, Agarwal A, Gaur A, et al. Serratus anterior plane block for multiple rib fractures. Pain Physician. 2014;17(4): E651- E653.
2. El-Boghdadly K, Wiles, MD. Regional anaesthesia for rib fractures: too many choices, too little evidence. Anaesthesia. 2019; 74: 564-568.