1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

MM - 1660
Impact of Moderate-to-Severe Chronic Kidney Disease on Outcomes After CAR T-Cell Therapy in Multiple Myeloma: A Real-World Propensity Score-Matched Analysis
Poster Presenter
Authors
Part of Topic
Multiple Myeloma (MM)
Abstract
Background
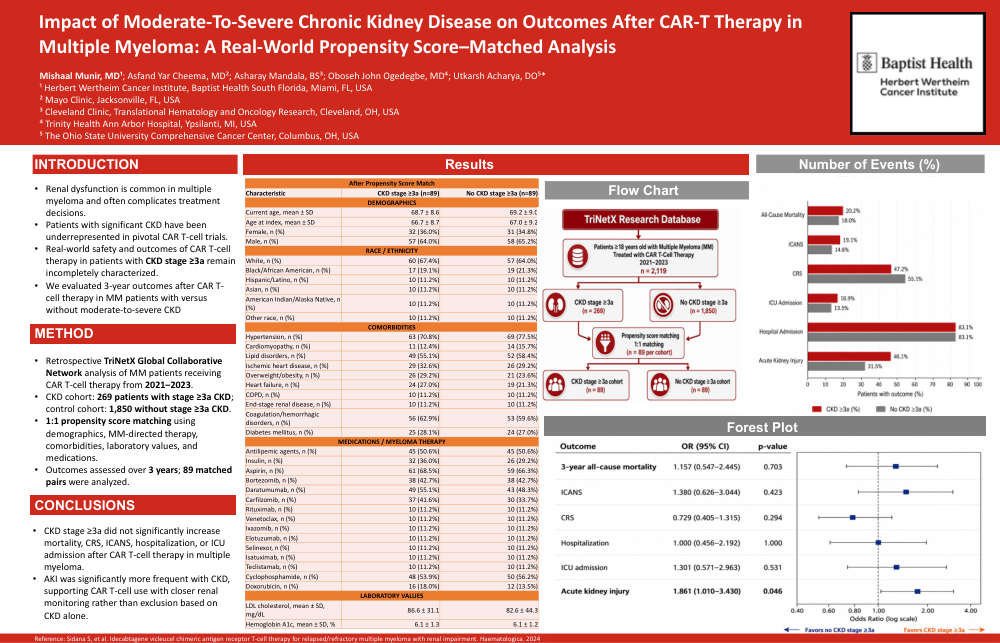
Renal dysfunction is common in multiple myeloma (MM) and often complicates treatment decisions. Although chimeric antigen receptor T-cell (CAR-T) therapy has transformed outcomes in relapsed/refractory MM, patients with clinically significant chronic kidney disease (CKD) have been underrepresented in pivotal trials due to renal eligibility criteria. As a result, the real-world safety of CAR-T therapy in patients with MM who have CKD remains unclear. We evaluated outcomes after CAR-T therapy among patients with MM and concomitant CKD stage ≥3a, compared with matched patients without CKD stage ≥3a.
Methods
We performed a retrospective propensity score–matched cohort study using the TriNetX database, including patients with MM treated with CAR-T therapy who had preexisting CKD stage ≥3a (n=269) versus control patients without CKD stage ≥3a (n=1850) from 2021 to 2023. Propensity score matching (1:1 ratio) was performed using a greedy nearest-neighbor method with a caliper of 0.1 pooled SD, adjusting for demographics, MM-directed therapy, comorbidities, laboratory values, and medications. Primary outcomes were all-cause mortality, ICANS, and cytokine release syndrome (CRS). Secondary outcomes included hospitalizations, ICU admissions, and acute kidney injury (AKI). Odds ratios (ORs) with 95% confidence intervals (CIs) over 3 years were calculated.
Results
After matching, 89 pairs were analyzed. Mean age was 68.7±8.6 years in the CKD stage ≥3a group and 63.9±9.0 years in the controls; 36% of patients were female in both groups. CKD stage ≥3a was not associated with significantly different odds of all-cause mortality (OR, 1.157; 95% CI, 0.547–2.445; P=0.703), ICANS (OR, 1.380; 95% CI, 0.626–3.044; P=0.423), CRS (OR, 0.729; 95% CI, 0.405–1.315; P=0.294), hospitalization (OR, 1.000; 95% CI, 0.456–2.192; P=1.000), or ICU admission (OR, 1.301; 95% CI, 0.571–2.963; P=0.531). However, CKD stage ≥3a was associated with significantly higher odds of AKI after CAR-T therapy (OR, 1.861; 95% CI, 1.010–3.430; P=0.046).
Conclusion
In this real-world matched cohort, CKD stage ≥3a was not associated with increased mortality or immune-mediated toxicities after CAR-T therapy in MM. Notwithstanding the limited sample size and paucity of granular clinical context pertaining to patient/disease characteristics and therapeutic nuances, these findings compel the exploration of liberalizing renal inclusion criteria among CAR-T therapy prospects with moderate-to-severe CKD.
ICANS: immune effector cell–associated neurotoxicity syndrome, ICU: intensive care unit, SD: standard deviation
Keywords
MM, chronic kidney disease, CAR-T therapy, cytokine release syndrome, acute kidney injury, propensity score matching