1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

AML - 677
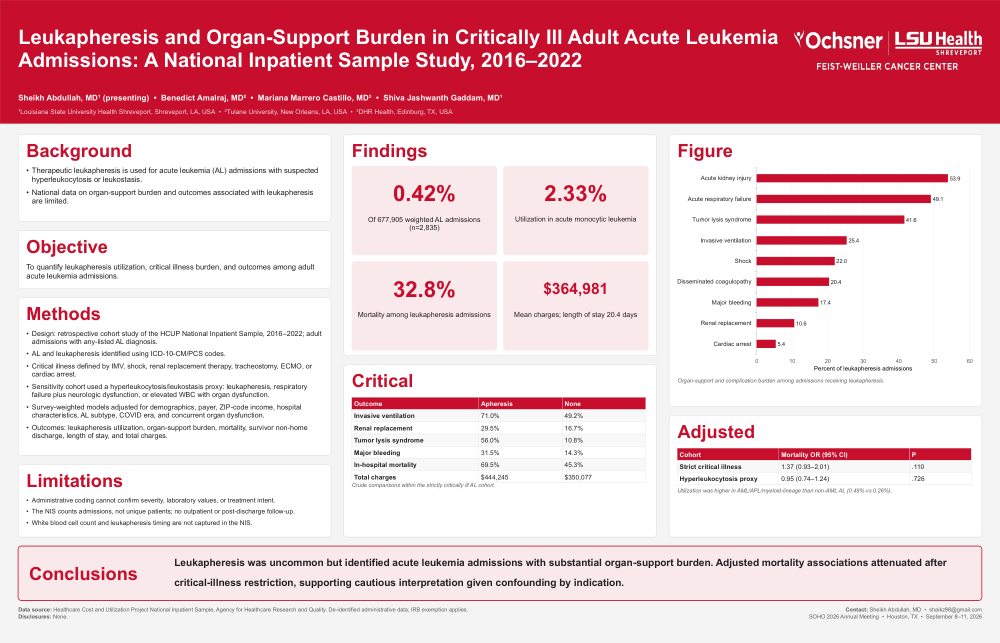
Leukapheresis and Organ-Support Burden in Critically Ill Adult Acute Leukemia Admissions: A National Inpatient Sample Study, 2016-2022
Poster Presenter
Authors
Part of Topic
Acute Myeloid Leukemia (AML)
Background
- Therapeutic leukapheresis is used for acute leukemia (AL) admissions with suspected hyperleukocytosis or leukostasis.
- National data on organ-support burden and outcomes associated with leukapheresis are limited.
Objective
To quantify leukapheresis utilization, critical illness burden, and outcomes among adult acute leukemia admissions.
Methods
- Design: retrospective cohort study of the HCUP National Inpatient Sample, 2016-2022; adult admissions with any-listed AL diagnosis.
- AL and leukapheresis identified using ICD-10-CM/PCS codes.
- Critical illness defined by IMV, shock, renal replacement therapy, tracheostomy, ECMO, or cardiac arrest.
- Sensitivity cohort used a hyperleukocytosis/leukostasis proxy: leukapheresis, respiratory failure plus neurologic dysfunction, or elevated WBC with organ dysfunction.
- Survey-weighted models adjusted for demographics, payer, ZIP-code income, hospital characteristics, AL subtype, COVID era, and concurrent organ dysfunction.
- Outcomes: leukapheresis utilization, organ-support burden, mortality, survivor non-home discharge, length of stay, and total charges.
Limitations
- Administrative coding cannot confirm severity, laboratory values, or treatment intent.
- The NIS counts admissions, not unique patients; no outpatient or post-discharge follow-up.
- White blood cell count and leukapheresis timing are not captured in the NIS.
Findings
- 0.42% | Of 677,905 weighted AL admissions (n=2,835)
- 2.33% | Utilization in acute monocytic leukemia
- 32.8% | Mortality among leukapheresis admissions
- $364,981 | Mean charges; length of stay 20.4 days
Critical (table: Outcome / Apheresis / None)
Invasive ventilation 71.0% vs 49.2% · Renal replacement 29.5% vs 16.7% · Tumor lysis syndrome 56.0% vs 10.8% · Major bleeding 31.5% vs 14.3% · In-hospital mortality 69.5% vs 45.3% · Total charges $444,245 vs $350,077
Crude comparisons within the strictly critically ill AL cohort.
Adjusted (table: Cohort / Mortality OR, 95% CI / P)
Strict critical illness 1.37 (0.93-2.01), .110 · Hyperleukocytosis proxy 0.95 (0.74-1.24), .726
Utilization was higher in AML/APL/myeloid-lineage than non-AML AL (0.49% vs 0.26%).
Figure caption
Organ-support and complication burden among admissions receiving leukapheresis.
Conclusions
Leukapheresis was uncommon but identified acute leukemia admissions with substantial organ-support burden. Adjusted mortality associations attenuated after critical-illness restriction, supporting cautious interpretation given confounding by indication.