1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

AML - 676
Acute Respiratory Failure and Invasive Mechanical Ventilation in Adult Acute Leukemia Admissions: National Trends and COVID-Era Outcomes, 2016-2022
Poster Presenter
Authors
Part of Topic
Acute Myeloid Leukemia (AML)
Background
- Acute respiratory failure and invasive mechanical ventilation (ARF/IMV) are high-risk complications in acute leukemia (AL).
- Contemporary national estimates of ARF/IMV incidence, COVID-era changes, and resource use are limited.
Objective
To evaluate national trends and inpatient outcomes associated with ARF/IMV among adults hospitalized with acute leukemia.
Methods
- Design: retrospective cohort study of the HCUP National Inpatient Sample, 2016-2022; adult admissions with any-listed AL diagnosis.
- AL categorized as AML/APL/myeloid-lineage versus non-AML AL.
- ARF/ARDS, intubation, IMV, tracheostomy, ECMO, and renal replacement therapy identified by ICD-10-CM/PCS codes.
- Survey weights, strata, and hospital clusters generated national estimates; resource use assessed with total charges.
- Multivariable survey models adjusted for demographics, payer, ZIP-code income quartile, hospital characteristics, AL subtype, COVID era, and concurrent complications (sepsis, shock, AKI, DIC, TLS, neutropenic fever).
- Outcomes: ARF/IMV incidence, mortality, survivor non-home discharge, length of stay, charges, and advanced organ support.
Limitations
- Administrative coding cannot confirm severity, laboratory values, or treatment intent.
- The NIS counts admissions, not unique patients; no outpatient or post-discharge follow-up.
- Charges reflect billed amounts rather than delivered costs of care.
Findings (four callouts)
- 677,905 | Weighted AL admissions (approximately 96,844 per year)
- 13.8% | Admissions with ARF/IMV (IMV alone, 4.8%)
- 11.0 to 16.3% | ARF/IMV, 2016 to 2022 (aOR 1.08 per year)
- 9.08 | Adjusted odds of in-hospital mortality with ARF/IMV
Outcomes (table: Outcome / ARF/IMV / No ARF/IMV)
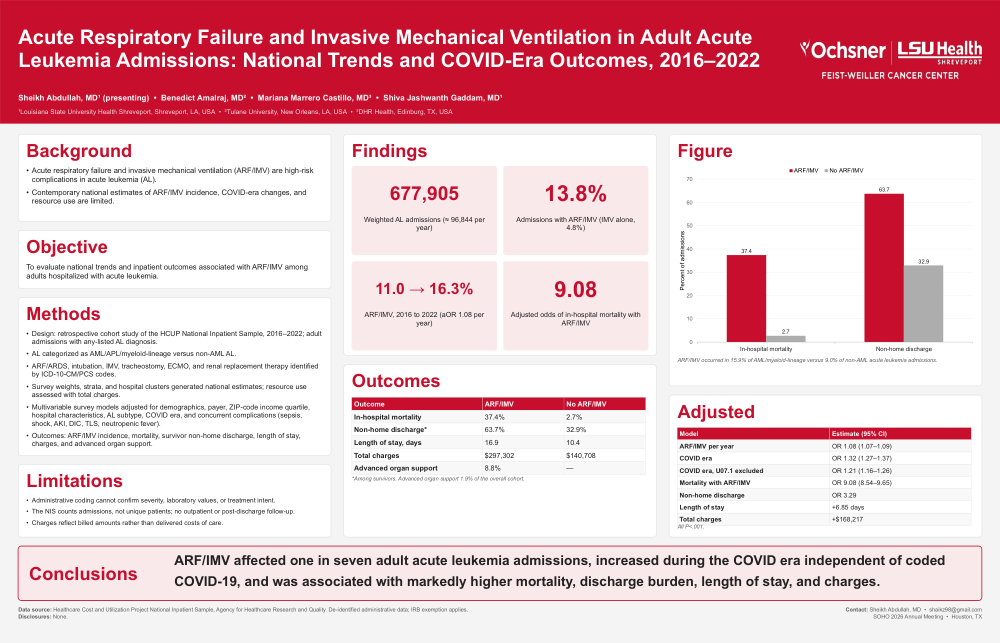
In-hospital mortality 37.4% vs 2.7% · Non-home discharge* 63.7% vs 32.9% · Length of stay, days 16.9 vs 10.4 · Total charges $297,302 vs $140,708 · Advanced organ support 8.8% vs not applicable
*Among survivors. Advanced organ support 1.9% of the overall cohort.
Adjusted (table: Model / Estimate, 95% CI)
ARF/IMV per year OR 1.08 (1.07-1.09) · COVID era OR 1.32 (1.27-1.37) · COVID era, U07.1 excluded OR 1.21 (1.16-1.26) · Mortality with ARF/IMV OR 9.08 (8.54-9.65) · Non-home discharge OR 3.29 · Length of stay +6.85 days · Total charges +$168,217
All P<.001.
Figure caption
ARF/IMV occurred in 15.9% of AML/myeloid-lineage versus 9.0% of non-AML acute leukemia admissions.
Conclusions
ARF/IMV affected one in seven adult acute leukemia admissions, increased during the COVID era independent of coded COVID-19, and was associated with markedly higher mortality, discharge burden, length of stay, and charges.