1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

CT - 649
Ciltacabtagene autoleucel immune effector cell enterocolitis is a clonal CAR+ lymphoproliferative disorder
Poster Presenter
Authors
Part of Topic
Cellular Therapy (CT)
Background
Ciltacabtagene autoleucel (cilta-cel) is an autologous BCMA-targeting CAR-T currently approved in 2L+ setting in multiple myeloma.
•Unique structure with two camelid VHH chains, allowing for camelid IHC staining.
•Cilta-cel can lead to durable response but can be associated with significant toxicity.
Immune effector cell-associated enterocolitis (IEC-EC) is an emerging toxicity that can develop after cilta-cel, often presenting with profuse, watery diarrhea, and abdominal pain.
•IEC-EC may develop from post-CAR T-cell lymphoproliferation, with some cases driven by clonal CAR+ T-cell infiltration into GI tissues.
•Cases can have high morbidity and mortality and are often treatment-refractory.
•The incidence, outcomes, and optimal management of IEC-EC remain poorly defined.
Objectives
•Describe incidence, clinical characteristics, treatment approaches and outcomes of all observed cases of IEC-EC at a single tertiary cancer center.
•Investigate the pathologic features of IEC-EC and evaluate clonality with anti-camelid immunohistochemical staining, flow cytometry, single cell RNA sequencing, whole exome sequencing, nested PCR sequencing, and whole genome sequencing.
Methods
•Single‑center case series of IEC-EC cases
•Suspected IEC‑EC identified by new enteritis/diarrhea prompting endoscopy with infectious evaluation per institutional standard of care.
•Compare cases of verified IEC-EC (with CAR T-cell infiltration, n = 9) to cases of post-cilta-cel enterocolitis not otherwise specified (EC-NOS, n = 8)
•All clinical details and treatments extracted from EHR.
•Biopsies reviewed with camelid (CAR) IHC. CAR+ IEC defined as >20% camelid+ infiltrates.
•COMET analysis used of camelid IHC by multiparametric fluorescent profiling and algorithmic counting of cells for camelid detection
•Clonality assessed in all cases by multiple methods.
Conclusions
•CAR+ IEC‑EC after cilta‑cel occurs in a measurable minority of patients and is associated with substantial morbidity and contribution to NRM.
•Biopsies frequently show dense CAR+ infiltrates and clonal/oligoclonal T‑cell populations, supporting a CAR‑driven lymphoproliferative process that mimics indolent GI T-cell lymphoma.
•Early endoscopy and biopsy with IHC and flow cytometry to confirm infiltrate is crucial
•T‑cell directed approaches (e.g., cyclophosphamide) may reduce CAR burden and symptoms, leading to durable remission. Careful balancing of infection risk and disease control should be considered.
Key Points:
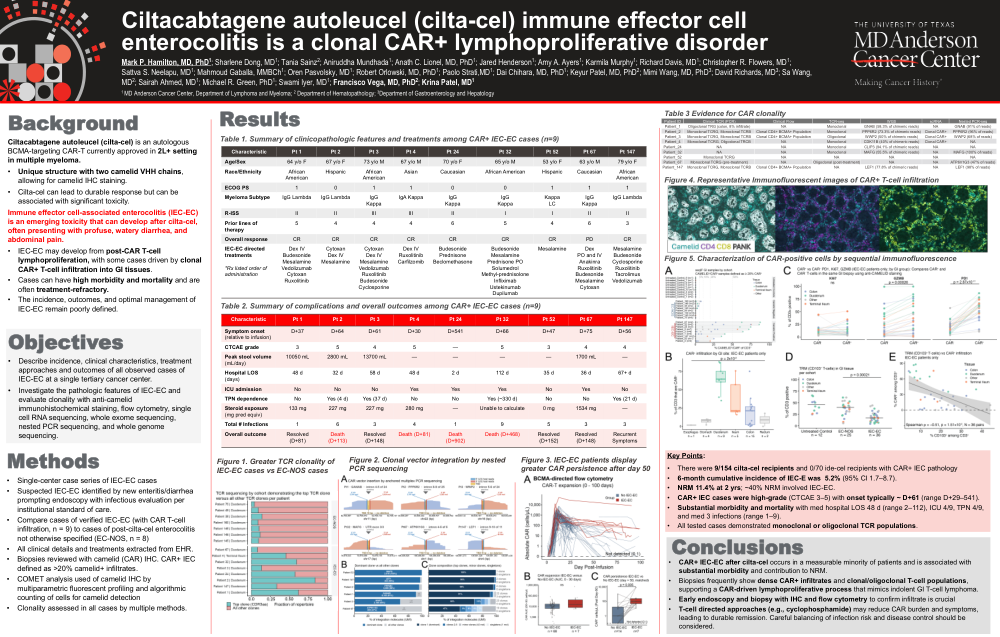
•There were 9/154 cilta‑cel recipients and 0/70 ide-cel recipients with CAR+ IEC pathology
•6‑month cumulative incidence of IEC‑E was 5.2% (95% CI 1.7–8.7).
•NRM 11.4% at 2 yrs; ~40% NRM involved IEC‑EC.
•CAR+ IEC cases were high‑grade (CTCAE 3–5) with onset typically ~ D+61 (range D+29–541).
•Substantial morbidity and mortality with med hospital LOS 48 d (range 2–112), ICU 4/9, TPN 4/9, and med 3 infections (range 1–9).
•All tested cases demonstrated monoclonal or oligoclonal TCR populations.