1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

AML - 616
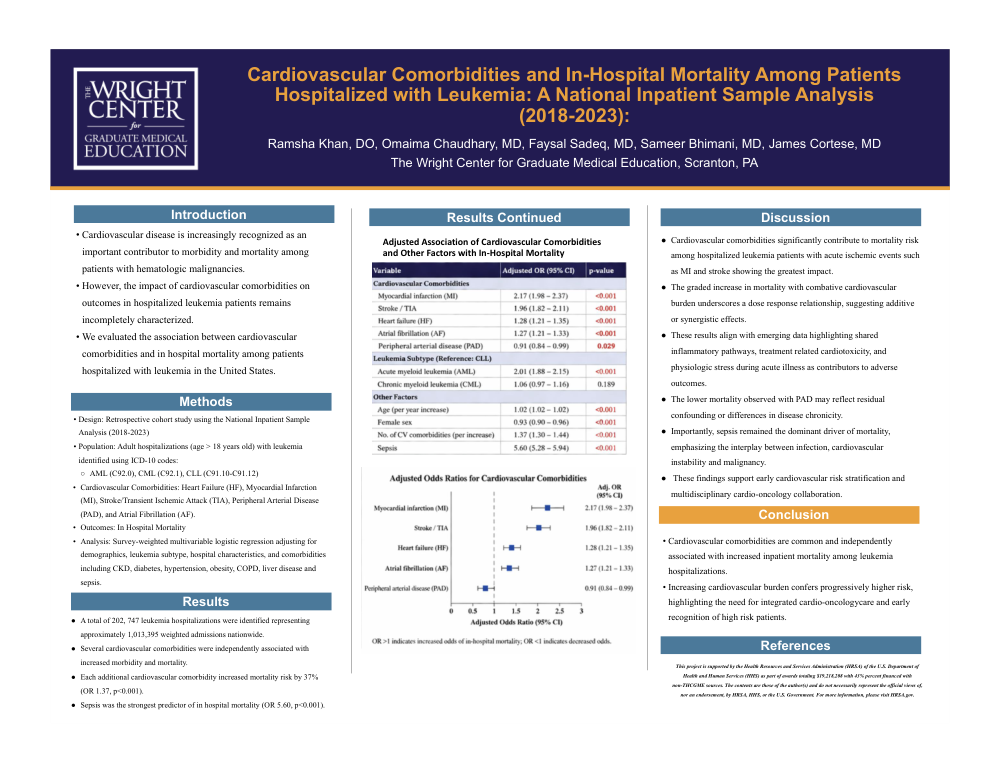
Cardiovascular Comorbidities and In-Hospital Mortality Among Patients Hospitalized With Leukemia: A National Inpatient Sample Analysis, 2018-2023
Poster Presenter
Authors
Part of Topic
Acute Myeloid Leukemia (AML)
-
Cardiovascular disease is increasingly recognized as an important contributor to morbidity and mortality among patients with hematologic malignancies.
-
However, the impact of cardiovascular comorbidities on outcomes in hospitalized leukemia patients remains incompletely characterized.
-
We evaluated the association between cardiovascular comorbidities and in hospital mortality among patients hospitalized with leukemia in the United States.
-
Design: Retrospective cohort study using the National Inpatient Sample Analysis (2018-2023)
-
Population: Adult hospitalizations (age > 18 years old) with leukemia identified using ICD-10 codes:
-
AML (C92.0), CML (C92.1), CLL (C91.10-C91.12)
-
Cardiovascular Comorbidities: Heart Failure (HF), Myocardial Infarction (MI), Stroke/Transient Ischemic Attack (TIA), Peripheral Arterial Disease (PAD), and Atrial Fibrillation (AF).
-
Outcomes: In Hospital Mortality
-
Analysis: Survey-weighted multivariable logistic regression adjusting for demographics, leukemia subtype, hospital characteristics, and comorbidities including CKD, diabetes, hypertension, obesity, COPD, liver disease and sepsis.
-
A total of 202, 747 leukemia hospitalizations were identified representing approximately 1,013,395 weighted admissions nationwide.
-
Several cardiovascular comorbidities were independently associated with increased morbidity and mortality.
-
Each additional cardiovascular comorbidity increased mortality risk by 37% (OR 1.37, p<0.001).
-
Sepsis was the strongest predictor of in hospital mortality (OR 5.60, p<0.001).
-
Cardiovascular comorbidities significantly contribute to mortality risk among hospitalized leukemia patients with acute ischemic events such as MI and stroke showing the greatest impact.
-
The graded increase in mortality with combative cardiovascular burden underscores a dose response relationship, suggesting additive or synergistic effects.
-
These results align with emerging data highlighting shared inflammatory pathways, treatment related cardiotoxicity, and physiologic stress during acute illness as contributors to adverse outcomes.
-
The lower mortality observed with PAD may reflect residual confounding or differences in disease chronicity.
-
Importantly, sepsis remained the dominant driver of mortality, emphasizing the interplay between infection, cardiovascular instability and malignancy.
-
These findings support early cardiovascular risk stratification and multidisciplinary cardio-oncology collaboration.
-
Cardiovascular comorbidities are common and independently associated with increased inpatient mortality among leukemia hospitalizations.
-
Increasing cardiovascular burden confers progressively higher risk, highlighting the need for integrated cardio-oncologycare and early recognition of high risk patients.
-
-
-
-