1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

IBCL - 552
Administering Tafasitamab, Lenalidomide and Rituximab for Follicular Lymphoma: a Single Institution Experience From the Phase 3 inMIND Study
Poster Presenter
Authors
Part of Topic
Indolent B-Cell Lymphoma (IBCL)
Video
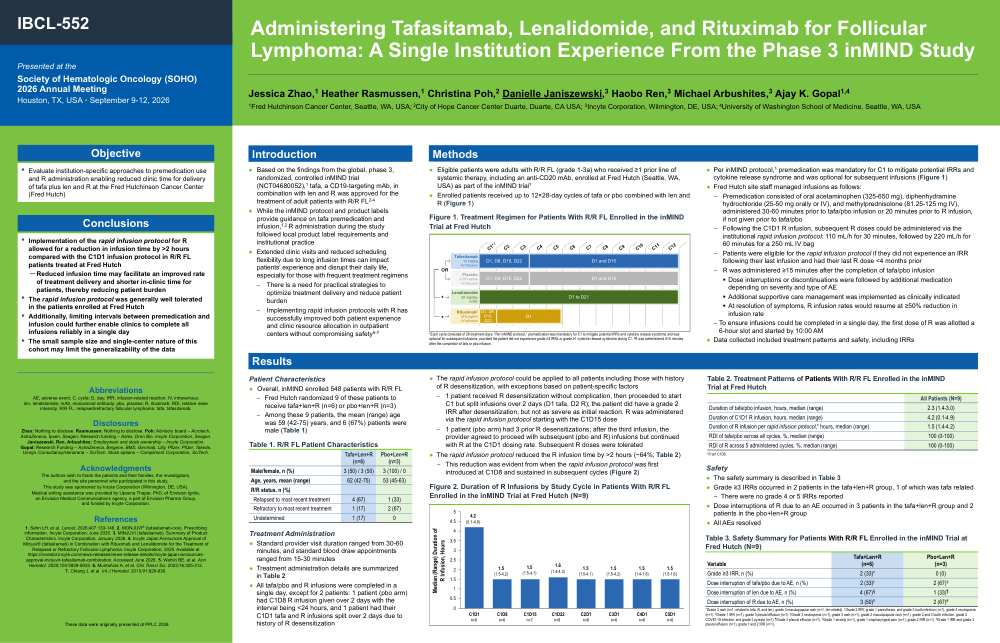
CONTEXT: Based on inMIND, tafasitamab with lenalidomide and rituximab was approved for treatment of adults with relapsed/refractory follicular lymphoma (R/R FL). While the inMIND protocol and product labels provided guidance on tafasitamab premedication and infusion, rituximab administration followed local product label requirements and institutional practice, creating variability. Practical strategies are therefore needed to optimize treatment delivery and reduce patient burden. We describe institution-specific approaches enabling reduced clinic time for administration of tafasitamab, lenalidomide, and rituximab at the Fred Hutchinson (Fred Hutch) Cancer Center.
DESIGN: Fred Hutch (Seattle, WA, USA) was one of 210 sites enrolling adult patients with R/R FL (grade 1–3a) who received ≥1 prior systemic therapy, including an anti-CD20 mAb. Patients received up to 12×28-day cycles of tafasitamab (12 mg/kg IV) or placebo, plus lenalidomide (20 mg/day orally) and rituximab (375 mg/m² IV). Premedication was mandatory in Cycle 1 and optional thereafter, if no grade ≥2 infusion-related reactions (IRRs) occurred. Rituximab was administered ≥15 minutes after completion of tafasitamab/placebo infusion.
RESULTS: Of 548 patients enrolled, 9 were treated at Fred Hutch (tafasitamab+lenalidomide+rituximab, n=6; placebo+lenalidomide+rituximab, n=3). Oral acetaminophen (325–650 mg), diphenhydramine hydrochloride (25–50 mg IV), and methylprednisolone (81.25–125 mg IV) premedications were administered 30–60 minutes prior to tafasitamab/placebo infusion. Median tafasitamab/placebo infusion duration was 2.3 hours. Median rituximab infusion time (Cycle 1 Day 1, 4.2 hours) reduced to 1.5 hours with a rapid infusion protocol in subsequent cycles. This protocol was feasible even in patients with prior rituximab desensitization. Median relative dose intensity for both tafasitamab/placebo and rituximab across administered cycles was 100%. Grade 3 IRR (rash) due to rituximab and tafasitamab was reported in 1 patient; no grade 4/5 IRRs were reported. All AEs resolved and nearly all infusions were completed in a single day.
CONCLUSIONS: Experience from Fred Hutch demonstrates that reduced infusion durations for tafasitamab/placebo and rituximab delivered by the rapid infusion protocol described allowed for meaningful reduction in clinic time of >2 hours after Cycle 1 Day 1. Limiting intervals between pretreatment procedures and infusion would further enable completing all infusions reliably in a single day.