1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

AML - 409
Early vs Late Granulocyte Colony-Stimulating Factor Initiation and Hospital Length of Stay in Adult Inpatients With Severe Neutropenia: A Retrospective Cohort Study
Poster Presenter
Authors
Part of Topic
Acute Myeloid Leukemia (AML)
Early vs. Late G-CSF Initiation and Hospital Length of Stay in Severe Neutropenia
Severe neutropenia (ANC <500 cells/µL) drives infection, prolonged hospitalization, and healthcare utilization in oncology inpatients. G-CSF is well established for prophylaxis, but guidance is limited regarding when to initiate G-CSF after hospitalization for severe neutropenia when treatment is indicated.
Aim: Among adult inpatients with severe neutropenia already treated with G-CSF, determine whether initiation within 24 hours of admission (“early”) is associated with shorter hospital length of stay and lower 30-day readmission compared with initiation more than 24 hours after admission (“late”).
Methods: Single-center retrospective cohort using EHR data from 2018–2025. The primary cohort included 100 adults with ANC <500 cells/µL who received at least one G-CSF dose. Early initiation was defined as ≤24 hours after admission (n=81) and late initiation as >24 hours (n=19). The primary outcome was hospital length of stay. Secondary and safety outcomes included 30-day readmission, in-hospital mortality, and discharge ANC.
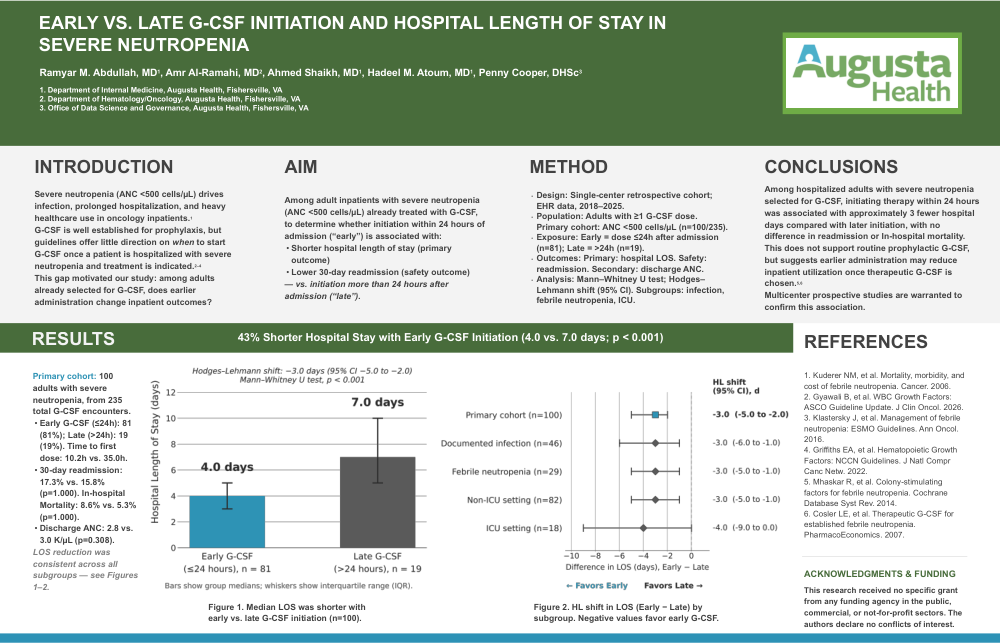
Results: Median hospital length of stay was 4.0 days with early G-CSF versus 7.0 days with late G-CSF. Hodges–Lehmann shift: −3.0 days (95% CI −5.0 to −2.0); Mann–Whitney U test, p<0.001. Thirty-day readmission was 17.3% versus 15.8%, in-hospital mortality was 8.6% versus 5.3%, and discharge ANC was 2.8 versus 3.0 K/µL. Point estimates favored early G-CSF across prespecified subgroups.
Conclusions: Among hospitalized adults with severe neutropenia selected for G-CSF treatment, initiation within 24 hours was associated with approximately 3 fewer hospital days compared with later initiation, without a statistically significant difference in 30-day readmission or in-hospital mortality. Multicenter prospective studies are warranted to confirm this association.