1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

AML - 121
A Rare Case of ZBTB16-RARA Fusion Acute Myeloid Leukemia Mimicking APL: Diagnostic Challenges and Successful CLIA + Venetoclax Therapy
Poster Presenter
Authors
Part of Topic
Acute Myeloid Leukemia (AML)
A Rare Case of AML with ZBTB16-RARA (PLZF-RARA) Fusion: Diagnostic Challenges and Morphologic Remission with CLIA + Venetoclax
Gamaliel Monge-Ruiz, MD, MPH¹, Gabriela Torres-Torres, MD², Patricia Dávila-Cardona, MD², Pedro Rivas-Vega, MD², Carolina Machado-De La Torre, MD¹,
Brian Virella-Berio, MD¹, Alexis M. Cruz Chacón, MD²
¹Department of Internal Medicine, San Juan City Hospital, San Juan, PR ²Department of Hematology/Oncology, San Juan City Hospital, San Juan, PR
BACKGROUND
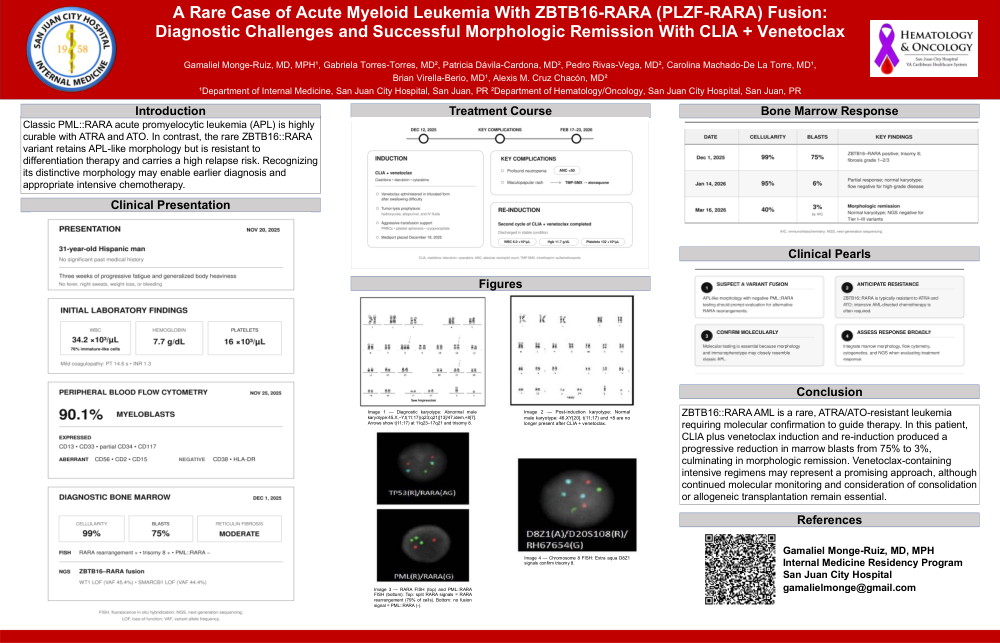
Classic APL (PML::RARA) is highly curable with ATRA + ATO. ZBTB16-RARA (t(11;17)) is a rare variant (~1% of RARA-rearranged AML) with APL-like morphology but ATRA/ATO resistance due to PLZF repressive domains. Intensive chemotherapy yields CR rates of 55–88% with high relapse risk. Round non-lobulated nuclei, hypergranulation, scarce Auer rods, and crystalline inclusions can suggest the variant early (Dowse & Ireland, Blood 2017).
CASE PRESENTATION
31-year-old Hispanic man; no significant past medical history. Transferred November 20, 2025 from Hospital Auxilio Mutuo Bayamón after 3 weeks of fatigue and 1 week of generalized body heaviness. Denied fever, night sweats, weight loss, and bleeding.
Admission laboratories: WBC 34.2–36.4 × 10³/µL with ~76% immature-like cells. Hemoglobin 7.5–7.7 g/dL after 2 PRBC. Platelets 10–16 × 10³/µL. Mild coagulopathy (INR 1.3).
Peripheral-blood flow (November 24, 2025 — BM25-2084): 90.1% myeloblasts: CD13+, CD33+, CD117+, CD34 partial (~42%); aberrant CD56, CD2, CD15; CD38− and HLA-DR−.
Diagnostic marrow (December 1, 2025 — BM25-2114): 99% cellular, 75% blasts, reticulin fibrosis grade 1–2/3. Blasts with granular cytoplasm, some indented or bilobed nuclei, rare Auer rods. FISH: RARA rearrangement + (79%), trisomy 8 +, PML::RARA −. Karyotype: 45,X,−Y,t(11;17)(q23;q21)[13]/47,idem,+8[7]. NGS: ZBTB16-RARA fusion; WT1 LOF (VAF 45.4%); SMARCB1 LOF (VAF 44.4%). FLT3, NPM1, IDH1/2, and CEBPA not detected.
TREATMENT COURSE
ZBTB16-RARA is ATRA/ATO-resistant. Plan: intensive CLIA (cladribine, idarubicin, cytarabine) plus venetoclax.
Supportive measures: hydroxyurea 1 g PO every 8 hours; allopurinol and 0.9% NS for TLS prophylaxis; transfuse for hemoglobin >7 g/dL and platelets >20K (raised to >60K before access); cryoprecipitate if fibrinogen <150 mg/dL. Venetoclax crushed after swallowing difficulty (written waiver). Central line December 10, 2025. Mediport December 18, 2025.
Induction — December 12, 2025: CLIA + venetoclax. Complicated by ANC <50 and a maculopapular rash (TMP-SMX switched to atovaquone). Multiple PRBC, platelet apheresis, and cryoprecipitate transfusions.
Re-induction — February 17–23, 2026: second CLIA + venetoclax cycle completed. Discharged stable: WBC 6.0, hemoglobin 11.7 g/dL, platelets 132K.
SERIAL MARROW RESPONSE
Dec 1, 2025: cellularity 99%, blasts 75%. ZBTB16-RARA+, trisomy 8, fibrosis grade 1–2/3.
Jan 14, 2026: cellularity 95%, blasts 6%. Partial response. Karyotype 46,XY[20]. Flow negative for high-grade disease.
Mar 16, 2026: cellularity 40%, blasts 3% by IHC. Morphologic remission. NGS negative.
FIGURES
Diagnostic karyotype showed 45,X,−Y,t(11;17)(q23;q21)[13]/47,idem,+8[7], with arrows marking the t(11;17) at 11q23 and 17q21 and the +8 clone. After CLIA plus venetoclax, the karyotype normalized to 46,XY[20], and the prior t(11;17) and trisomy 8 were no longer detected. Interphase FISH confirmed an extra D8Z1 signal consistent with trisomy 8, a RARA rearrangement in 79% of nuclei, and no PML::RARA fusion, excluding classic t(15;17) APL.
DISCUSSION
Molecular testing is required. APL-like cases need urgent FISH and NGS for the RARA partner. ZBTB16-RARA is intrinsically ATRA/ATO-resistant; misclassification delays effective intensive therapy.
Morphology can raise early suspicion. Round non-lobulated nuclei, dense granules, few or no Auer rods, and crystalline inclusions differ from classic APL and should trigger testing beyond PML::RARA (Dowse & Ireland, Blood 2017).
Venetoclax plus intensive chemotherapy is a rational option. Blasts fell 75% → 6% → 3%, with karyotype normalization and NGS clearance after CLIA + venetoclax induction and re-induction.
Supportive care enabled delivery of therapy. Transfusions, TLS and infection prophylaxis, delayed but successful access placement, and crushed venetoclax allowed full-intensity treatment.
CONCLUSIONS
Confirm the RARA partner before choosing ATRA/ATO. CLIA + venetoclax achieved morphologic remission. Serial marrows showed 75% → 6% → 3% blasts. Venetoclax-based intensive therapy is a practical option while targeted agents are studied. Continue molecular follow-up; consider consolidation or transplant.
REFERENCES
Lo-Coco F, et al. N Engl J Med. 2013;369:111-121.
Grimwade D, et al. Blood. 2000;96:1297-1308.
Dowse RT, Ireland RM. Blood. 2017;129(14):2038. Yin CC, et al. B
lood Cancer J. 2021;11:168. DiNardo CD, et al.
Lancet. 2020;395:1817-1824.