516 posters, 59 topics, 63 sessions, 1,127 authors, 352 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
2026 SOAP Annual Meeting
April 29 - May 3, 2026 | Montreal, Quebec Canada

2339994
New-onset Peripartum Cardiomyopathy with Focal Pulmonary Edema Masked as Pneumonia Leads to Acute Decompensation in Labor Necessitating Urgent Cesarean Delivery
Poster Presenter
Authors
Payton Marshall, Ben Deverett, David Stahl, Igor Feinstein, Julio-Santiago Perez, Emily Stockert
Affiliations
Part of Topic
OB EMERGENCIES
New-onset Peripartum Cardiomyopathy with Focal Pulmonary Edema Masked as Pneumonia Leads to Acute Decompensation in Labor Necessitating Urgent Cesarean Delivery
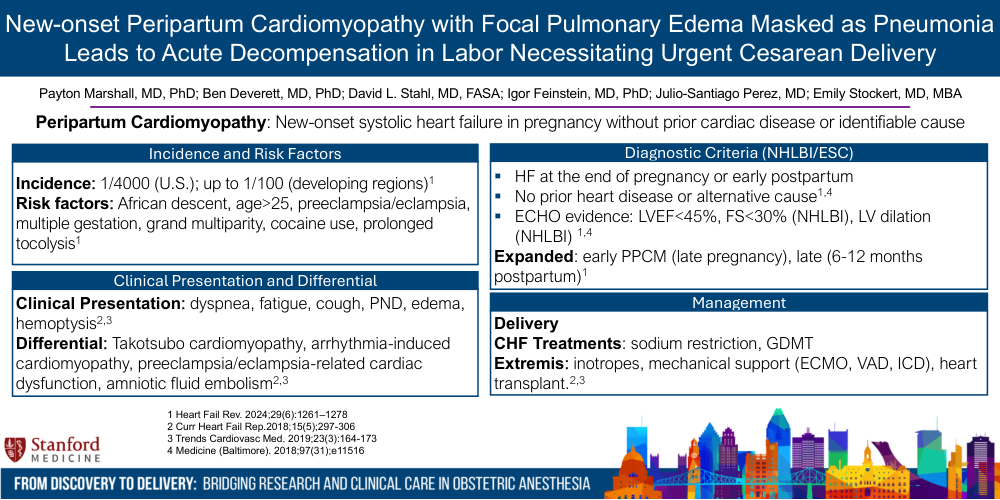
Payton Marshall, MD, PhD; Ben Deverett, MD, PhD; David L. Stahl, MD, FASA; Igor Feinstein, MD, PhD; Julio-Santiago Perez, MD; Emily Stockert, MD, MBA
Peripartum Cardiomyopathy: New-onset systolic heart failure in pregnancy without prior cardiac disease or identifiable cause
Incidence and Risk Factors
Incidence: 1/4000 (U.S.); up to 1/100 (developing regions)1
Risk factors: African descent, age>25, preeclampsia/eclampsia, multiple gestation, grand multiparity, cocaine use, prolonged tocolysis1
Clinical Presentation and Differential
Clinical Presentation: dyspnea, fatigue, cough, PND, edema, hemoptysis2,3
Differential: Takotsubo cardiomyopathy, arrhythmia-induced cardiomyopathy, preeclampsia/eclampsia-related cardiac dysfunction, amniotic fluid embolism2,3
Diagnostic Criteria (NHLBI/ESC)
- HF at the end of pregnancy or early postpartum
- No prior heart disease or alternative cause1,4
- ECHO evidence: LVEF<45%, FS<30% (NHLBI), LV dilation (NHLBI) 1,4
Expanded: early PPCM (late pregnancy), late (6-12 months postpartum)1
Management
Delivery
CHF Treatments: sodium restriction, GDMT
Extremis: inotropes, mechanical support (ECMO, VAD, ICD), heart transplant.2,3
Clinical Presentation: 39-year-old G4P2 with HTN, GDM, asthma presents at 37w gestation with mild dyspnea on exertion
Initial Workup and Intrapartum Course
- CXR: Bilateral interstitial opacities reflecting pulmonary edema
- CTPE (Right): Focal ground glass opacities concerning for atypical PNA
- Started on amoxicillin/azithromycin
- ECHO: Global hypokinesis, LVEF 31%, Moderate MR
Decision to proceed with induction of labor given mild symptoms
- Contraction pain managed with neuraxial analgesia
- Acute decompensation and hemodynamic instability norepinephrine gtt
- Worsening pulmonary edema Initiation of diuretics
Maternal intolerance of labor induction remote from delivery, decision to proceed with cesarean section under carefully titrated neuraxial anesthesia
- Epi + Dobutamine for vasoactive support
- Delivery of vigorous neonate with APGAR 8 (1min) and 8 (5min)
- Ventricular bigeminy throughout case into postpartum period
Postpartum
CVICU Admission, diuresis, euglycemic DKA
- ECHO: LVEF 29%, Severe MR w/ flow reversal in right pulmonary vein
- Discharged on GDMT (spironolactone, sacubitril/valsartan, empagliflozin, furosemide, carvedilol)
- LifeVest, Ziopatch
Teaching Points
In This Case
- CTPE with findings of pneumonia due to focal nature, despite being pulmonary edema on CXR
- Acute MR resulted in flow reversal into the right pulmonary vein creating focal opacities
- Labor analgesia with plain epidural (institutional standard dosing) unmasked hemodynamic instability
- Delivery resulted in rapid discontinuation of support, however EF remained low requiring GDMT, LifeVest, Ziopatch
For Treatment of PPCM
- While most patients diagnosed in first trimester, presentation can be as late as delivery
- Even low dose epidural can unmask a well compensated hemodynamic instability
- Delivery often leads to rapid improvement of symptoms
- While most patients fully recover, chronic cardiac pathology is possible
|