875 posters, 25 topics, 3,440 authors, 1,061 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
SAGES 2026 Annual Meeting Emerging Technology Session
March 25-28, 2026 | Tampa, FL, USA

P817
Clinical and Cost Analysis of Robotic vs. Laparoscopic Cholecystectomy Stratified by Tokyo Guidelines Severity
Part of Topic
Robotics / Advanced Technologies
Introduction
Robot-assisted cholecystectomy (RC) and laparoscopic cholecystectomy (LC) are the most
common surgical approaches to treat acute cholecystitis. The 2018 Tokyo Guidelines is a widely
used grading system for acute cholecystitis. This study aims to compare the utilization of RC
and LC across Tokyo Guidelines severity grades and to establish a foundation for further
analysis of associated operative and economic outcomes.
Methods
This retrospective study analyzed 171 cholecystectomy cases, 95 RC and 76 LC from Kings
County Hospital between December 2019 to October 2022. Patients with traumatic abdominal
injuries or Whipple procedures were excluded from the study. Cholecystitis severity was then
graded using the Tokyo Guidelines. Demographic and clinical characteristics were comparable
between groups.
Results
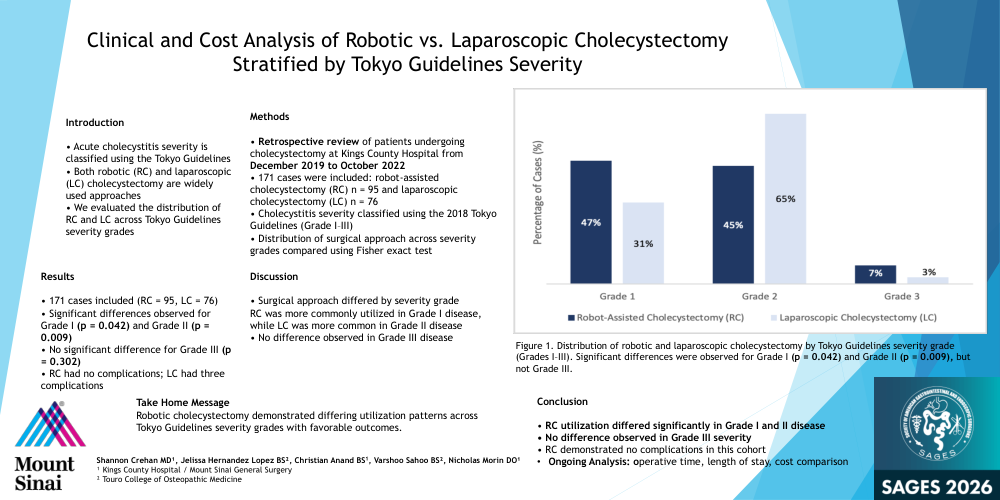
Of the 76 LC cases, 24 were classified as Grade 1, 50 as Grade 2, and 2 as Grade 3 according
to the Tokyo Guidelines. Among the 95 robotic-assisted cholecystectomy (RC) cases, 45 were
Grade 1, 43 were Grade 2, and 7 were Grade 3. Fisher’s exact tests were performed on raw
case counts to compare the distribution of surgical approaches within each severity grade. A
statistically significant difference in surgical approach was observed for both Grade 1 (p =
0.042) and Grade 2 (p = 0.009). No statistically significant difference was found for Grade 3
cases (p = 0.302).
Conclusion
The use of robot-assisted cholecystectomy in Grade 1 and Grade 2 cholecystitis was
statistically significant when compared to laparoscopic cholecystectomy. No significant
difference was observed in surgical approach for Grade 3 cases even though RC was more
commonly utilized in this severity grade. RC was associated with no reported complications,
while three complications occurred in LC cases: gallbladder fossa hematoma, surgical site
infection, and intraoperative liver laceration. Ongoing analysis will evaluate operative time,
hospital length of stay, and cost differences between RC and LC.