816 posters, 24 topics, 3,314 authors, 1,012 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
SAGES 2026 Annual Meeting Emerging Technology Session
March 25-28, 2026 | Tampa, FL, USA

P129
Spontaneous Splenic Rupture Causing Hemorrhagic Shock in an Anticoagulated Elderly Patient: A Case Report and Review of Management Challenges
Part of Topic
Acute Care
Introduction
-
Spontaneous splenic rupture (SSR) is a rare but life‑threatening cause of intra‑abdominal hemorrhage, distinct from traumatic splenic injury.
-
Anticoagulation with DOACs, especially in elderly patients with renal dysfunction and polypharmacy, increases the risk of major visceral bleeding.
-
This case highlights SSR causing hemorrhagic shock in a 74‑year‑old on apixaban and the challenges of balancing thrombotic and bleeding risks.
Case Presentation
-
74‑year‑old woman with atrial fibrillation on apixaban, CAD, CKD, diabetes, hemolytic anemia, and hypertension.
-
Presented with 1 day of worsening abdominal pain, near‑syncope, home BP 70/54, no trauma history.
-
ED: hypotension, hemoglobin 5.8 g/dL, lactate 5.9 mmol/L, acute kidney injury.
-
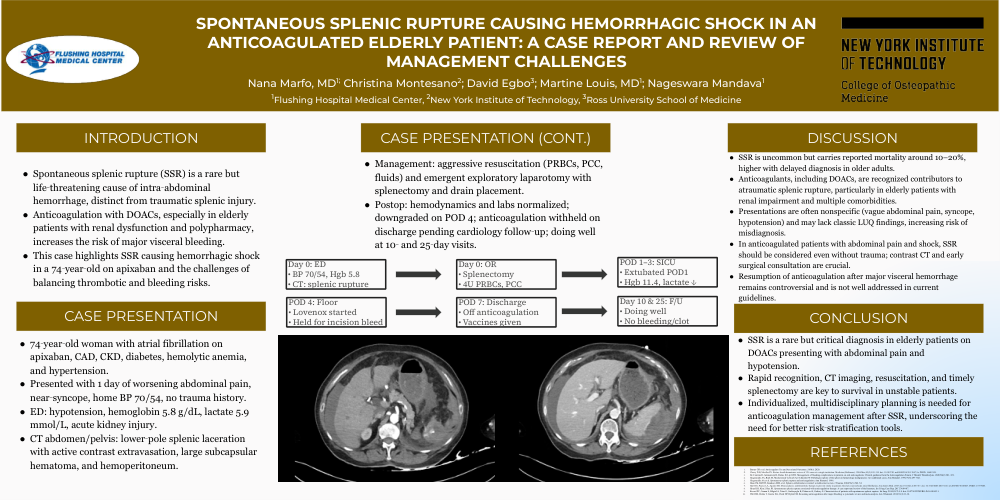
CT abdomen/pelvis: lower‑pole splenic laceration with active contrast extravasation, large subcapsular hematoma, and hemoperitoneum.
-
Management: aggressive resuscitation (PRBCs, PCC, fluids) and emergent exploratory laparotomy with splenectomy and drain placement.
-
Postop: hemodynamics and labs normalized; downgraded on POD 4; anticoagulation withheld on discharge pending cardiology follow‑up; doing well at 10‑ and 25‑day visits.
Discussion
-
SSR is uncommon but carries reported mortality around 10–20%, higher with delayed diagnosis in older adults.
-
Anticoagulants, including DOACs, are recognized contributors to atraumatic splenic rupture, particularly in elderly patients with renal impairment and multiple comorbidities.
-
Presentations are often nonspecific (vague abdominal pain, syncope, hypotension) and may lack classic LUQ findings, increasing risk of misdiagnosis.
-
In anticoagulated patients with abdominal pain and shock, SSR should be considered even without trauma; contrast CT and early surgical consultation are crucial.
-
Resumption of anticoagulation after major visceral hemorrhage remains controversial and is not well addressed in current guidelines.
Conclusion / Take‑home
-
SSR is a rare but critical diagnosis in elderly patients on DOACs presenting with abdominal pain and hypotension.
-
Rapid recognition, CT imaging, resuscitation, and timely splenectomy are key to survival in unstable patients.
-
Individualized, multidisciplinary planning is needed for anticoagulation management after SSR, underscoring the need for better risk‑stratification tools.