2,281 posters, 63 videos, 56 audios, 43 topics, 18 sessions, 6,174 authors, 2,323 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2025
June 23 - 25, 2025 | ExCeL London, UK
EP.0217
CASE SERIES: CAESEREAN SCAR ECTOPIC PREGNANCY
Part of Topic
Early pregnancy complications/early pregnancy and acute gynaecology
CASE SERIES: CAESEREAN SCAR ECTOPIC PREGNANCY
KRISHNAVENI G RAMAN, SIVAPRAKASAM MANJAMBIGAI
GRANGE UNIVERSITY HOSPITAL, ABUHB, NEWPORT,
UNITED KINGDOM
Objective: Caesarean scar ectopic pregnancy (CSP) is defined as implantation into the myometrial defect occurring at the site of the previous uterine incision. prevalence 1 in 2000 pregnancies ,may be ongoing potentially viable pregnancies or miscarriages within the scar, associated with severe maternal morbidity and mortality. (RCOG GTG 21/2016).
First line of diagnosis-Transvaginal Scan (TVS) supplemented by Abdominal scan. Second line – MRI
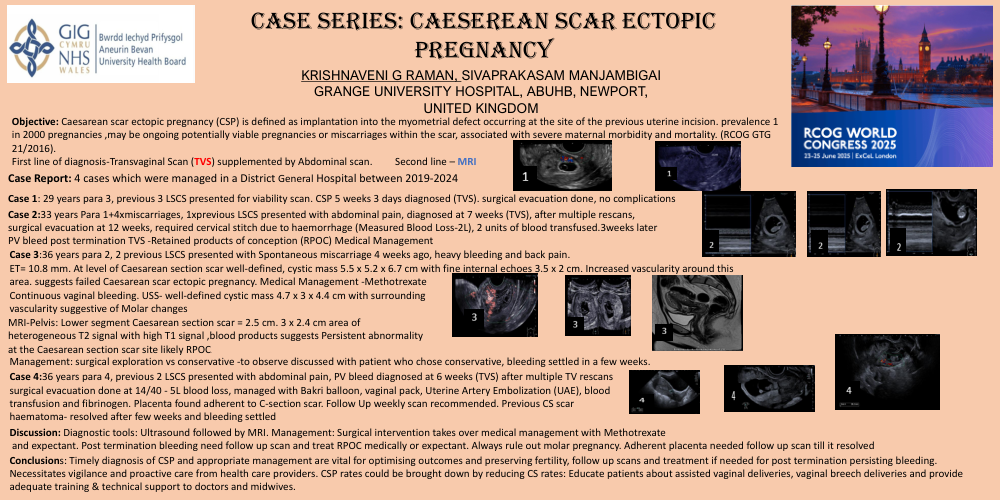
Case Report: 4 cases which were managed in a District General Hospital between 2019-2024.
Case 1: 29 years para 3, previous 3 LSCS presented for viability scan. CSP 5 weeks 3 days diagnosed (TVS). surgical evacuation done, no complications.
Case 2:33 years Para 1+4xmiscarriages, 1xprevious LSCS presented with abdominal pain, diagnosed at 7 weeks (TVS), after multiple rescans,
surgical evacuation at 12 weeks, required cervical stitch due to haemorrhage (Measured Blood Loss-2L), 2 units of blood transfused.3weeks later
PV bleed post termination TVS -Retained products of conception (RPOC) Medical Management.
Case 3:36 years para 2, 2 previous LSCS presented with Spontaneous miscarriage 4 weeks ago, heavy bleeding and back pain.
ET= 10.8 mm. At level of Caesarean section scar well-defined, cystic mass 5.5 x 5.2 x 6.7 cm with fine internal echoes 3.5 x 2 cm. Increased vascularity around this area. suggests failed Caesarean scar ectopic pregnancy. Medical Management -Methotrexate.Continuous vaginal bleeding. USS- well-defined cystic mass 4.7 x 3 x 4.4 cm with surrounding vascularity suggestive of Molar changes.MRI-Pelvis: Lower segment Caesarean section scar = 2.5 cm. 3 x 2.4 cm area of heterogeneous T2 signal with high T1 signal ,blood products suggests Persistent abnormality at the Caesarean section scar site likely RPOC.Management: surgical exploration vs conservative -to observe discussed with patient who chose conservative, bleeding settled in a few weeks.
Case 4:36 years para 4, previous 2 LSCS presented with abdominal pain, PV bleed diagnosed at 6 weeks (TVS) after multiple TV rescans surgical evacuation done at 14/40 - 5L blood loss, managed with Bakri balloon, vaginal pack, Uterine Artery Embolization (UAE), blood transfusion and fibrinogen. Placenta found adherent to C-section scar. Follow Up weekly scan recommended. Previous CS scar haematoma- resolved after few weeks and bleeding settled
Discussion: Diagnostic tools: Ultrasound followed by MRI. Management: Surgical intervention takes over medical management with Methotrexate
and expectant. Post termination bleeding need follow up scan and treat RPOC medically or expectant. Always rule out molar pregnancy. Adherent placenta needed follow up scan till it resolved.
Conclusions: Timely diagnosis of CSP and appropriate management are vital for optimising outcomes and preserving fertility, follow up scans and treatment if needed for post termination persisting bleeding.
Necessitates vigilance and proactive care from health care providers. CSP rates could be brought down by reducing CS rates: Educate patients about assisted vaginal deliveries, vaginal breech deliveries and provide adequate training & technical support to doctors and midwives.