2,281 posters, 63 videos, 56 audios, 43 topics, 18 sessions, 6,174 authors, 2,323 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2025
June 23 - 25, 2025 | ExCeL London, UK
EP.0146
Two years experience of Manual Vacuum Aspiration in a District General Hospital.
Poster Presenter
Authors
Affiliations
Part of Topic
Early pregnancy complications/early pregnancy and acute gynaecology
Background;
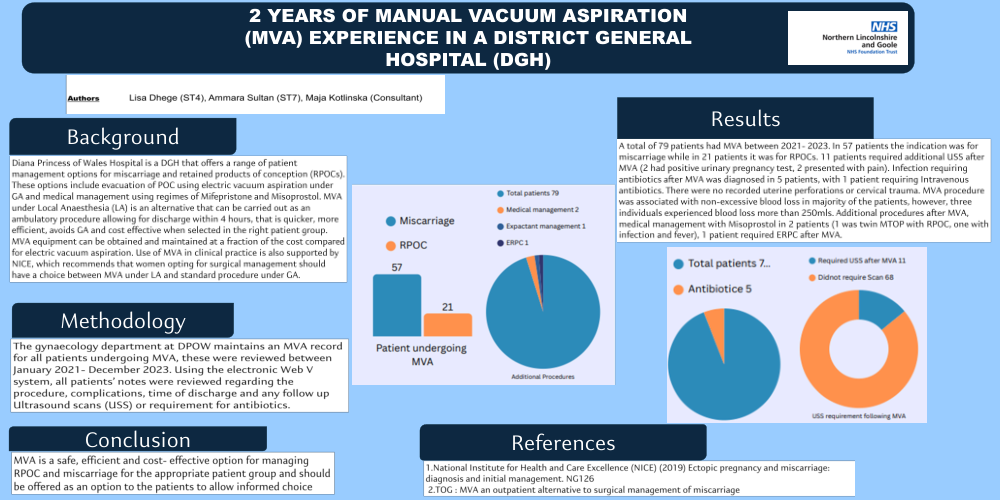
Diana Princess of Wales Hospital is a DGH that offers a range of patient management options for miscarriage and retained products of conception (RPOCs). These options include evacuation of POC using electric vacuum aspiration under GA and medical management using regimes of Mifepristone and Misoprostol. MVA under Local Anaesthesia (LA) is an alternative that can be carried out as an ambulatory procedure allowing for discharge within 4 hours, that is quicker, more efficient, avoids GA and cost effective when selected in the right patient group. MVA equipment can be obtained and maintained at a fraction of the cost compared for electric vacuum aspiration. Use of MVA in clinical practice is also supported by NICE, which recommends that women opting for surgical management should have a choice between MVA under LA and standard procedure under GA.
Results:
A total of 79 patients had MVA between 2021- 2023. In 57 patients the indication was for miscarriage while in 21 patients it was for RPOCs. 11 patients required additional USS after MVA (2 had positive urinary pregnancy test, 2 presented with pain). Infection requiring antibiotics after MVA was diagnosed in 5 patients, with 1 patient requiring Intravenous antibiotics. There were no recorded uterine perforations or cervical trauma. MVA procedure was associated with non-excessive blood loss in majority of the patients, however, three individuals experienced blood loss more than 250mls.Additional procedures after MVA, medical management with Misoprostol in 2 patients (1 was twin MTOP with RPOC, one with infection and fever), 1 patient required ERPC after MVA.
Methods:
The gynaecology department at DPOW maintains an MVA record for all patients undergoing MVA, these were reviewed between January 2021- December 2023. Using the electronic Web V system, all patients’ notes were reviewed regarding the procedure, complications, time of discharge and any follow up Ultrasound scans (USS) or requirement for antibiotics.
Conclusion:
MVA is a safe, efficient and cost- effective option for managing RPOC and miscarriage for the appropriate patient group and should be offered as an option to the patients to allow informed choice.
References:
1.National Institute for Health and Care Excellence (NICE) (2019) Ectopic pregnancy and miscarriage: diagnosis and miscarriage.NG 126
2.TOG MVA an outpatient alternative of surgical management of miscarriage.