2,281 posters, 63 videos, 56 audios, 43 topics, 18 sessions, 6,174 authors, 2,323 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2025
June 23 - 25, 2025 | ExCeL London, UK
EP.1279
Post-caesarean candida peritonitis complicated by cardiogenic pulmonary oedema
Poster Presenter
Authors
Shaimaa Badr, Srabani Mukherjee, Fatimah Al-Rufaye, Fatema Zohora
Affiliations
Part of Topic
Hot topics (emerging research/issues) in obstetrics
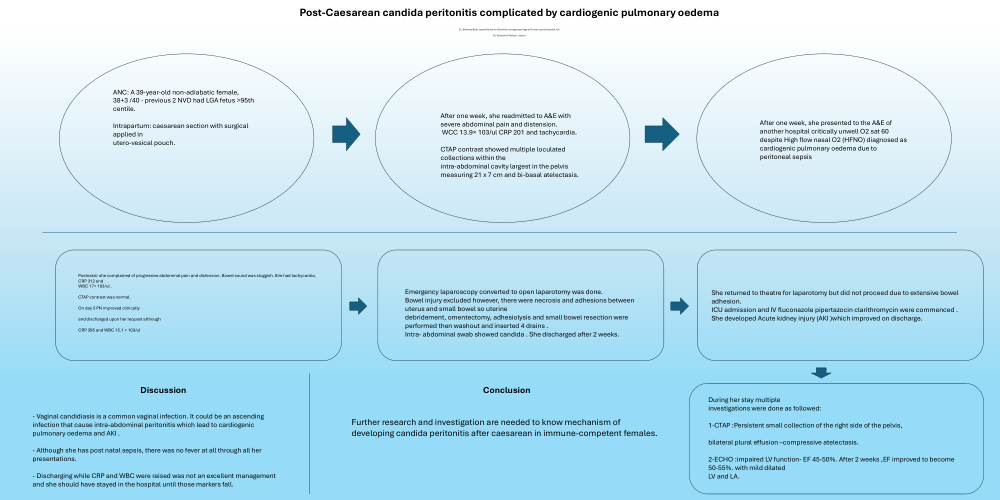
ANC: A 39-year-old non-adiabatic female, 38+3 /40 - previous 2 NVD had LGA fetus >95th centile. Intrapartum: caesarean section with surgical applied in utero-vesical pouch
After one week, she readmitted to A&E with severe abdominal pain and distension. WCC 13.9× 10³/ul CRP 201 and tachycardia. CTAP contrast showed multiple loculated collections within the intra-abdominal cavity largest in the pelvis measuring 21 x 7 cm and bi-basal atelectasis
After one week, she presented to the A&E of another hospital critically unwell O2 sat 60 despite High flow nasal O2 (HFNO) diagnosed as cardiogenic pulmonary oedema due to peritoneal sepsis
Postnatal: she complained of progressive abdominal pain and distension. Bowel sound was sluggish. She had tachycardia, CRP 312 and WBC 17× 103/ul . CTAP contrast was normal. On day 5 PN improved clinically and discharged upon her request although CRP 395 and WBC 15.1 × 10³/u
Emergency laparoscopy converted to open laparotomy was done. Bowel injury excluded however, there were necrosis and adhesions between uterus and small bowel so uterine debridement, omentectomy, adhesiolysis and small bowel resection were performed then washout and inserted 4 drains . Intra- abdominal swab showed candida . She discharged after 2 weeks
She returned to theatre for laparotomy but did not proceed due to extensive bowel adhesion. ICU admission and IV fluconazole pipertazocin clarithromycin were commenced . She developed Acute kidney injury (AKI )which improved on discharge
During her stay multiple investigations were done as followed: 1-CTAP :Persistent small collection of the right side of the pelvis, bilateral plural effusion –compressive atelectasis. 2-ECHO :impaired LV function- EF 45-50%. After 2 weeks ,EF improved to become 50-55%. with mild dilated LV and LA
Discussion- Vaginal candidiasis is a common vaginal infection. It could be an ascending infection that cause intra-abdominal peritonitis which lead to cardiogenic pulmonary oedema and AKI .- Although she has post natal sepsis, there was no fever at all through all her presentations.- Discharging while CRP and WBC were raised was not an excellent management and she should have stayed in the hospital until those markers fall.
Conclusion Further research and investigation are needed to know mechanism of developing candida peritonitis after caesarean in immune-competent females