2,281 posters, 63 videos, 56 audios, 43 topics, 18 sessions, 6,174 authors, 2,323 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2025
June 23 - 25, 2025 | ExCeL London, UK
EP.1140
The rare, dare & dire; Unusual cases of VTE in pregnancy & puerperium.
Poster Presenter
Authors
Affiliations
Part of Topic
High risk pregnancy
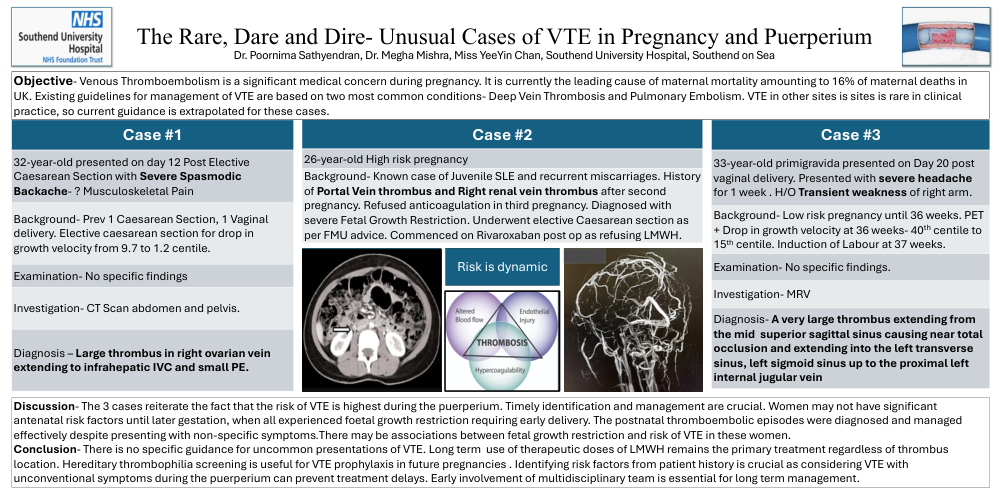
The Rare, Dare and Dire- Unusual Cases of VTE in Pregnancy and Puerperium
Dr. Poornima Sathyendran, Dr. Megha Mishra, Miss YeeYin Chan, Southend University Hospital, Southend on Sea
Objective- Venous Thromboembolism is a significant medical concern during pregnancy. It is currently the leading cause of maternal mortality amounting to 16% of maternal deaths in UK. Existing guidelines for management of VTE are based on two most common conditions- Deep Vein Thrombosis and Pulmonary Embolism. VTE in other sites is sites is rare in clinical practice, so current guidance is extrapolated for these cases.
Case #1
32-year-old presented on day 12 Post Elective Caesarean Section with Severe Spasmodic Backache- ? Musculoskeletal Pain.
Background- Prev 1 Caesarean Section, 1 Vaginal delivery. Elective caesarean section for drop in growth velocity from 9.7 to 1.2 centile.
Examination- No specific findings
Investigation- CT Scan abdomen and pelvis.
Diagnosis – Large thrombus in right ovarian vein extending to infrahepatic IVC and small PE.
Case #2
26-year-old High risk pregnancy
Background- Known case of Juvenile SLE and recurrent miscarriages. History of Portal Vein thrombus and Right renal vein thrombus after second pregnancy. Refused anticoagulation in third pregnancy. Diagnosed with severe Fetal Growth Restriction. Underwent elective Caesarean section as per FMU advice. Commenced on Rivaroxaban post op as refusing LMWH.
Case #3
33-year-old primigravida presented on Day 20 post vaginal delivery. Presented with severe headache for 1 week . H/O Transient weakness of right arm.
Background- Low risk pregnancy until 36 weeks. PET + Drop in growth velocity at 36 weeks- 40th centile to 15th centile. Induction of Labour at 37 weeks.
Examination- No specific findings.
Investigation- MRV
Diagnosis- A very large thrombus extending from the mid superior sagittal sinus causing near total occlusion and extending into the left transverse sinus, left sigmoid sinus up to the proximal left internal jugular vein
Discussion- The 3 cases reiterate the fact that the risk of VTE is highest during the puerperium. Timely identification and management are crucial. Women may not have significant antenatal risk factors until later gestation, when all experienced foetal growth restriction requiring early delivery. The postnatal thromboembolic episodes were diagnosed and managed effectively despite presenting with non-specific symptoms.There may be associations between fetal growth restriction and risk of VTE in these women.
Conclusion- There is no specific guidance for uncommon presentations of VTE. Long term use of therapeutic doses of LMWH remains the primary treatment regardless of thrombus location. Hereditary thrombophilia screening is useful for VTE prophylaxis in future pregnancies . Identifying risk factors from patient history is crucial as considering VTE with unconventional symptoms during the puerperium can prevent treatment delays. Early involvement of multidisciplinary team is essential for long term management.