2,281 posters, 63 videos, 56 audios, 43 topics, 18 sessions, 6,174 authors, 2,323 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2025
June 23 - 25, 2025 | ExCeL London, UK
EP.1104
Silent fundal uterine rupture in unscarred term uterus- A rare Case Report
Poster Presenter
Authors
Affiliations
Part of Topic
High risk pregnancy
Silent fundal uterine rupture in unscarred term uterus- A rare Case Report
Professor Dr. Drakhshan Nauman
Professor of Gynae/Obs, Akhtar Saeed Medical and Dental college, Lahore, Pakistan
Objectives:
Uterine rupture can lead to serious feto maternal morbidiy and mortality. Diagnosis of silent uterine rupture in an unscarred not labouring uterus is challenging due to lack of any specific signs or symptoms. Although very rare yet a catastrophic event in obstetrics. The literature suggests an incidence of 1 in 5700 to 1 in 50000 pregnancies. Therefore it is mandatory to identify risk factors associated with silent uterine rupture.
Case Report:
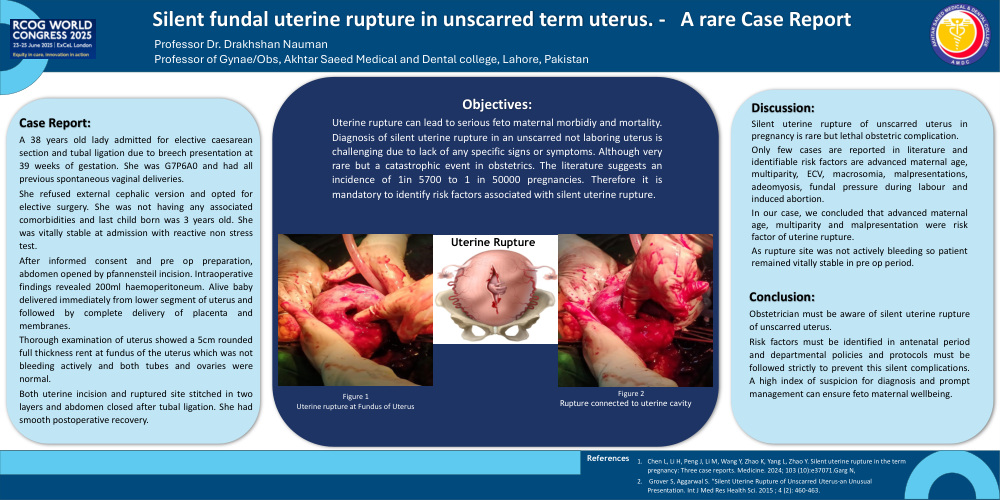
A 38 years old lady admitted for elective caesarean section and tubal ligation due to breech presentation at 39 weeks of gestation. She was G7P6A0 and had all previous spontaneous vaginal deliveries. She refused external cephalic version and opted for elective surgery. She was not having any associated comorbidities and last child born was 3 years old. She was vitally stable at admission with reactive non stress test. After informed consent and pre op preparation, abdomen opened by pfannensteil incision. Intraoperative findings revealed 200ml haemoperitoneum. Alive baby delivered immediately from lower segment of uterus, followed by complete delivery of placenta and membranes. Thorough examination of uterus showed a 5cm rounded full thickness rent at fundus of the uterus which was not bleeding actively and both tubes and ovaries were normal. Uterine scar and ruptured site stitched in 2 layers with vicryl 1 and abdomen closed after tubal ligation. She had smooth postoperative recovery.
Discussion:
Silent uterine rupture of unscarred uterus in pregnancy is rare but lethal obstetric complication. Only few cases are reported in literature and identifiable risk factors are advanced maternal age, multiparity, ECV, macrosomia, malpresentations, adenomyosis, fundal pressure during labour and induced abortion.
In our case, we concluded that advanced maternal age, multiparity and malpresentation were risk factor of silent uterine rupture. As rupture site was not actively bleeding so patient remained vitally stable in antenatal period.
Conclusion:
Obstetrician must be aware of silent uterine rupture of unscarred uterus. Risk factors must be identified in antenatal period and departmental policies and protocols must be followed strictly to prevent this silent complications. A high index of suspicion for diagnosis and prompt management can ensure feto maternal wellbeing.
References:
- Chen L, Li H, Peng J, Li M, Wang Y, Zhao K, Yang L, Zhao Y. Silent uterine rupture in the term pregnancy: Three case reports. Medicine. 2024; 103 (10):e37071.
- Garg N, Grover S, Aggarwal S. “Silent Uterine Rupture of Unscarred Uterus-an Unusual Presentation. Int J Med Res Health Sci. 2015 ; 4 (2): 460-463.