2,281 posters, 63 videos, 56 audios, 43 topics, 18 sessions, 6,174 authors, 2,323 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2025
June 23 - 25, 2025 | ExCeL London, UK
EP.1079
Diagnostic Dilemma in a Primigravida with Severe Refractory Anemia – A case report
Poster Presenter
Authors
Affiliations
Part of Topic
High risk pregnancy
Objective
To understand the evaluation and management of anemia in pregnancy refractory to iron therapy
Case history
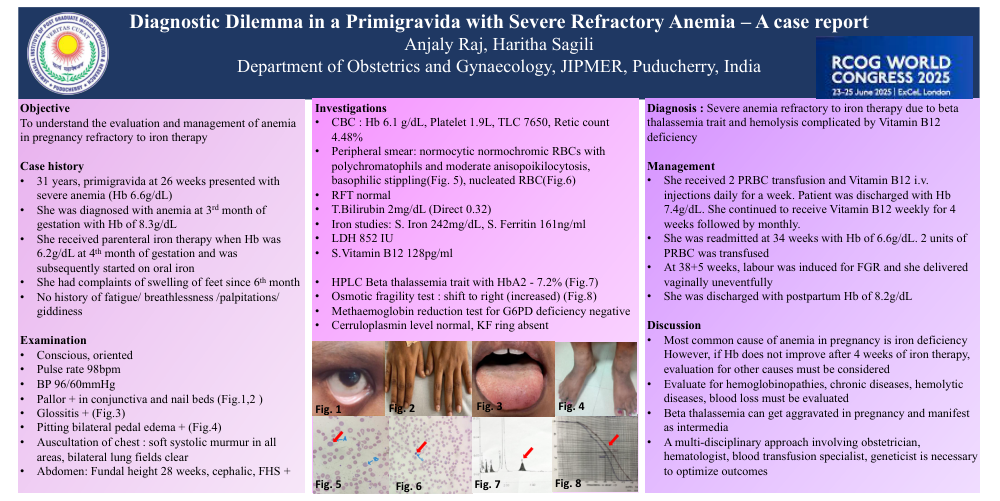
31 years, primigravida at 26 weeks presented with severe anemia (Hb 6.6g/dL). She was diagnosed with anemia at 3rd month of gestation with Hb of 8.3g/dL. She received parenteral iron therapy when Hb was 6.2g/dL at 4th month of gestation and was subsequently started on oral iron. She had complaints of swelling of feet since 6th month. No history of fatigue/ breathlessness /palpitations/ giddiness.
Examination
Conscious, oriented. Pulse rate 98bpm. BP 96/60mmHg
Pallor + in conjunctiva and nail beds (Fig.1,2 )
Glossitis + (Fig.3)
Pitting bilateral pedal edema + (Fig.4)
Auscultation of chest : soft systolic murmur in all areas, bilateral lung fields clear
Abdomen: Fundal height 28 weeks, cephalic, FHS +
Investigations
CBC : Hb 6.1 g/dL, Platelet 1.9L, TLC 7650, Retic count 4.48%
Peripheral smear: normocytic normochromic RBCs with polychromatophils and moderate anisopoikilocytosis, basophilic stippling(Fig. 5), nucleated RBC(Fig.6)
RFT normal
T.Bilirubin 2mg/dL (Direct 0.32)
Iron studies: S. Iron 242mg/dL, S. Ferritin 161ng/ml
LDH 852 IU
S.Vitamin B12 128pg/ml
HPLC Beta thalassemia trait with HbA2 - 7.2% (Fig.7)
Osmotic fragility test : shift to right (increased) (Fig.8)
Methaemoglobin reduction test for G6PD deficiency negative
Cerruloplasmin level normal, KF ring absent
Diagnosis : Severe anemia refractory to iron therapy due to beta thalassemia trait and hemolysis complicated by Vitamin B12 deficiency
Management
She received 2 PRBC transfusion and Vitamin B12 i.v. injections daily for a week. Patient was discharged with Hb 7.4g/dL. She continued to receive Vitamin B12 weekly for 4 weeks followed by monthly. She was readmitted at 34 weeks with Hb of 6.6g/dL. 2 units of PRBC was transfused. At 38+5 weeks, labour was induced for FGR and she delivered vaginally uneventfully. She was discharged with postpartum Hb of 8.2g/dL.
Discussion
Most common cause of anemia in pregnancy is iron deficiency However, if Hb does not improve after 4 weeks of iron therapy, evaluation for other causes must be considered. Evaluate for hemoglobinopathies, chronic diseases, hemolytic diseases, blood loss must be evaluated. Beta thalassemia can get aggravated in pregnancy and manifest as intermedia. A multi-disciplinary approach involving obstetrician, hematologist, blood transfusion specialist, geneticist is necessary to optimize outcomes.