1,830 posters, 67 videos, 75 audios, 29 topics, 22 sessions, 4,727 authors, 1,697 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2023
June 12 - 14, 2023 | London, UK

EP.0791
Occult endometrial cancer: an unfortunate coincidence?
Poster Presenter
Authors
Affiliations
Part of Topic
Gynae Oncology
Occult Endometrial Cancer: An Unfortunate Coincidence? Dr Megan Wright, Miss Sue Ward
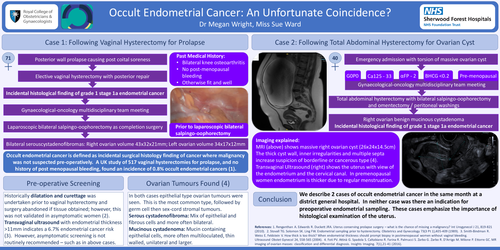
Case 1: Following Vaginal Hysterectomy for Prolapse
71 Posterior wall prolapse causing post coital soreness
Elective vaginal hysterectomy with posterior repair
Incidental histological finding of grade 1 stage 1a endometrial cancer
Gynaecological-oncology multidisciplinary team meeting
Laparoscopic bilateral salpingo-oophorectomy as completion surgery
Bilateral serouscystadenofibromas: Right ovarian volume 43x32x21mm; Left ovarian volume 34x17x12mm
Past Medical History: • Bilateral knee osteoarthritis • No post-menopausal bleeding • Otherwise fit and well
Prior to laparoscopic bilateral salpingo-oophorectomy
Occult endometrial cancer is defined as incidental surgical histology finding of cancer where malignancy was not suspected pre-operatively. A UK study of 517 vaginal hysterectomiesfor prolapse, and no history of post menopausal bleeding, found an incidence of 0.8% occult endometrial cancers (1).
Pre-operative Screening
Historically dilatation and curettage was undertaken prior to vaginal hysterectomy and surgery abandoned if tissue obtained; however, this was not validated in asymptomatic women (2). Transvaginal ultrasound with endometrial thickness >11mm indicates a 6.7% endometrial cancer risk (3). However, asymptomatic screening is not routinely recommended – such as in above cases.
Ovarian Tumours Found (4)
In both cases epithelial type ovarian tumours were seen. This is the most common type, followed by germ cell then sex-cord stromal tumours. Serous cystadenofibroma: Mix of epithelial and fibrous cells and more often bilateral. Mucinous cystadenoma: Mucin containing epithelial cells, more often multiloculated, thin walled, unilateral and larger.
Case 2: Following Total Abdominal Hysterectomy for Ovarian Cyst
40 Emergency admission with torsion of massive ovarian cyst
G0P0 Ca125 - 33 αFP - 2 ΒHCG <0.2 Pre-menopausal
Gynaecological-oncology multidisciplinary team meeting
Total abdominal hysterectomy with bilateral salpingo-oophorectomy and omentectomy / peritoneal washings
Right ovarian benign mucinous cystadenoma Incidental histological finding of grade 1 stage 1a endometrial cancer
Imaging explained: MRI (above) shows massive right ovarian cyst (26x24x14.5cm) The thick cyst wall, inner irregularities and multiple septa increase suspicion of borderline or cancerous type (4). Transvaginal Ultrasound (right) shows the uterus with view of the endometrium and the cervical canal. In premenopausal women endometrium is thicker due to regular menstruation.
Conclusion
We describe 2 cases of occult endometrial cancer in the same month at a district general hospital. In neither case was there an indication for preoperative endometrial sampling. These cases emphasize the importance of histological examination of the uterus. References: 1. Renganthan A. Edwards R. Duckett JRA. Uterus conserving prolapse surgery – what is the chance of missing a malignancy? Int Urogynecol J 21, 819-821 (2010). 2. Stovall TG. Solomon SK. Ling FW. Endometrial sampling prior to hysterectomy. Obstetrics and Gynecology 73(3 Pt 1),405-409 (1989). 3. Smith-Bindman R. Weiss E. Feldstein V. How thick is too thick? When endometrial thickness should prompt biopsy in postmenopausal women without vaginal bleeding. Ultrasound Obstet Gynecol 24, 558-565 (2004). 4. Foti PV. Attinà G. Spadola S. Caltabiano R. Farina R. Palmucci S. Zarbo G. Zarbo R. D'Arrigo M. Milone P. Ettorre GC. MR imaging of ovarian masses: classification and differential diagnosis. Insights Imaging. 7(1),21-41 (2016)