1,830 posters, 67 videos, 75 audios, 29 topics, 22 sessions, 4,727 authors, 1,697 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2023
June 12 - 14, 2023 | London, UK

EP.0767
Intrapartum posterior uterine wall rupture in an unscarred uterus
Poster Presenter
Authors
Affiliations
Part of Topic
Labour Ward Management
Intrapartum Posterior Uterine Wall Rupture in a Unscarred Uterusd Uterus
OBJECTIVE:
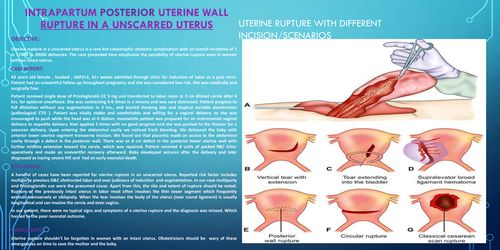
Uterine rupture in a unscarred uterus is a rare but catastrophic obstetric complication with an overall incidence of 1 in 17000 to 20000 deliveries. The case presented here emphasize the possibility of uterine rupture even in women with an intact uterus.
CASE REPORT:
43 years old female , booked , G6P3+2, 41+ weeks admitted through clinic for induction of labor as a post term. Patient had an uneventful follow up throughout pregnancy and she was considered low risk. She was medically and surgically free.
Patient received single dose of Prostaglandin E2 3 mg and transferred to labor room at 3 cm dilated cervix after 4 hrs. for epidural anesthesia. She was contracting 5-6 times in a minute and was very distressed. Patient progress to full dilatation without any augmentation in 3 hrs., and started showing late and atypical variable deceleration (pathological CTG ). Patient was vitally stable and comfortable and willing for a vaginal delivery so she was encouraged to push while the head was at 0 station, meanwhile patient was prepared for an instrumental vaginal delivery to expedite delivery. Kiwi applied 3 times with no good progress and she was pushed to the theater for a cesarean delivery. Upon entering the abdominal cavity we noticed fresh bleeding. We delivered the baby with anterior lower uterine segment transverse incision. We found out that placenta made an access to the abdominal cavity through a defect in the posterior wall. There was an 8 cm defect in the posterior lower uterine wall with further midline extension toward the cervix, which was repaired. Patient received 4 units of packed RBC intra-operatively and made an uneventful recovery afterward. Baby developed seizures after the delivery and later diagnosed as having severe HIE and had an early neonatal death.
DISCUSSION:
A handful of cases have been reported for uterine rupture in an unscarred uterus. Reported risk factor includes multiparty previous D&C obstructed labor and over judicious of induction and augmentation. In our case multiparty and Prostaglandin use were the presumed cause. Apart from this, the site and extent of rupture should be noted. Rupture of the previously intact uterus in labor most often involves the thin lower segment which frequently extends transversely or obliquely. When the tear involves the body of the uterus (near round ligament) is usually longitudinal and can involve the cervix and even vagina.
In our patient, there were no typical signs and symptoms of a uterine rupture and the diagnosis was missed. Which has led to the poor neonatal outcome.
CONCLUSION:
Uterine rupture shouldn’t be forgotten in women with an intact uterus. Obstetricians should be wary of these emergencies on time to save the mother and the baby.