1,830 posters, 67 videos, 75 audios, 29 topics, 22 sessions, 4,727 authors, 1,697 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2023
June 12 - 14, 2023 | London, UK

PP.0229
Secondary subfertility as the initial presentation of acromegaly
Poster Presenter
Part of Topic
Reproductive Medicine/Assisted Reproduction
Secondary subfertility as the initial presentation of acromegaly – A Case Report Matthew Cannings MBChB 1 , Maya N Thomas MBChB 2 , Rukshini Puvanendran MBBS 3 1. The Dudley Group NHS Foundation Trust, 2. Royal Wolverhampton NHS Trust 3. Family Medicine Service, KK Women’s and Children’s Hospital, Singapore
Introduction
Acromegaly is a rare condition with an annual incidence of 0.2-1.1 cases per 100,000 people with evidence of significant diagnostic delay. Although infertility is commonly seen in women with acromegaly, it seldom thought of as a differential.
Learning outcomes:
1) To highlight an interesting case in which infertility was the first presentation of acromegaly
2) To highlight the commonality of infertility amongst women with acromegaly, raise clinical suspicion and thereby reduce diagnostic delay
Case Summary
• Here we present the case of a 35-year-old lady, married with 1 child, conceived age 19
• Living in Singapore
• Initial complaint of secondary infertility age 25 – underwent extensive work up before being diagnosed with acromegaly 10 years later
First Presentation (Age 25)
• First presented age 25 having tried to conceive unsuccessful for 5 years. Had one child at age 19
• Regular menstrual periods, no menorrhagia, dysmenorrhea, or dyspareunia
• Work up included US pelvis which showed a polyp, subsequent hysterosalpingography and laparoscopy.
• The outcome suggesting endometriosis
• Tx: Unsuccessfully trialled on clomifene. Nil surgical intervention. Patient declined further gynaecology follow up
Second Presentation (Age 33)
• Age 33 returned to the women’s hospital with intermenstrual bleeding
• PMH: • diagnosed as hypertensive at age 30, stabilised on lisinopril and amlodipine • History of headaches – referred to neurology, defaulted
• Tx: Underwent hysteroscopy and D&C – endometrial polyp was removed
Case Summary -Final presentation (Age 35)
• Referred to the weight management clinic - BMI 35 kg/m2,
• PMH: Hypertensive; Impaired fasting glucose; ongoing headaches (no red flags, no visual field defect)
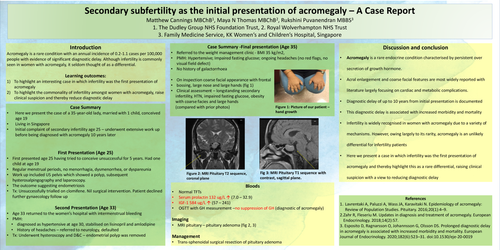
• No history of galactorrhoea • On inspection coarse facial appearance with frontal • bossing, large nose and large hands (fig 1)
• Clinical assessment – longstanding secondary infertility, HTN, impaired fasting glucose, obesity with coarse facies and large hands (compared with prior photos)
Bloods
• Normal TFTs
• Serum prolactin 132 ug/L (7.0 – 32.9)
• IGF-1 584 ug/L (57 – 241)
• OGTT with GH measurement –no suppression of GH (diagnostic of acromegaly)
Imaging
• MRI pituitary – pituitary adenoma (fig 2, 3)
Management
• Trans-sphenoidal surgical resection of pituitary adenoma
Discussion and conclusion
• Acromegaly is a rare endocrine condition characterised by persistent over secretion of growth hormone.
• Acral enlargement and coarse facial features are most widely reported with literature largely focusing on cardiac and metabolic complications.
• Diagnostic delay of up to 10 years from initial presentation is documented
• This diagnostic delay is associated with increased morbidity and mortality
• Infertility is widely recognised in women with acromegaly due to a variety of mechanisms. However, owing largely to its rarity, acromegaly is an unlikely differential for infertility patients
• Here we present a case in which infertility was the first presentation of acromegaly and thereby highlight this as a rare differential, raising clinical suspicion with a view to reducing diagnostic delay