1,830 posters, 67 videos, 75 audios, 29 topics, 22 sessions, 4,727 authors, 1,697 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2023
June 12 - 14, 2023 | London, UK

PP.0119
Study comparing oral Nifedipine and Intravenous Labetalol in hypertensive crisis in pregnancy
Poster Presenter
Part of Topic
High Risk Pregnancy
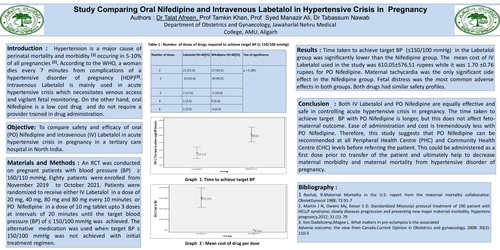
Introduction : Hypertension is a major cause of perinatal mortality and morbidity [1]occuring in 5-10% of all pregnancies [2]. According to the WHO, a woman dies every 7 minutes from complications of a hypertensive disorder of pregnancy (HDP)[3]. Intravenous Labetalol is mainly used in acute hypertensive crisis which necessitates venous access and vigilant fetal monitoring. On the other hand, oral Nifedipine is a low cost drug and do not require a provider trained in drug administration.
Objective: To compare safety and efficacy of oral (PO) Nifedipine and intravenous (IV) Labetalol in acute hypertensive crisis in pregnancy in a tertiary care hospital in North India.
Materials and Methods : An RCT was conducted on pregnant patients with blood pressure (BP) ≥ 160/110 mmHg. Eighty patients were enrolled from November 2019 to October 2021. Patients were randomized to receive either IV Labetalol in a dose of 20 mg, 40 mg, 80 mg and 80 mg every 10 minutes or PO Nifedipine in a dose of 10 mg tablet upto 3 doses at intervals of 20 minutes until the target blood pressure (BP) of ≤ 150/100 mmHg was achieved. The alternative medication was used when target BP ≤ 150/100 mmHg was not achieved with initial treatment regimen.
Results : Time taken to achieve target BP (≤150/100 mmHg) in the Labetalol group was significantly lower than the Nifedipine group. The mean cost of IV Labetalol used in the study was 610.05±576.51 rupees while it was 1.70 ±0.76 rupees for PO Nifedipine. Maternal tachycardia was the only significant side effect in the Nifedipine group. Fetal distress was the most common adverse effects in both groups. Both drugs had similar safety profiles.
Conclusion : Both IV Labetalol and PO Nifedipine are equally effective and safe in controlling acute hypertensive crisis in pregnancy. The time taken to achieve target BP with PO Nifedipine is longer, but this does not affect feto-maternal outcome. Ease of administration and cost is tremendously less with PO Nifedipine. Therefore, this study suggests that PO Nifedipine can be recommended at all Peripheral Health Centre (PHC) and Community Health Centre (CHC) levels before referring the patient. This could be administered as a first dose prior to transfer of the patient and ultimately help to decrease maternal morbidity and maternal mortality from hypertensive disorder of pregnancy.