1,830 posters, 67 videos, 75 audios, 29 topics, 22 sessions, 4,727 authors, 1,697 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2023
June 12 - 14, 2023 | London, UK

PP.0089
Managing Type 1 Diabetic Pregnancy with Prior Myocardial Infarction
Poster Presenter
Authors
Affiliations
Part of Topic
Maternal Medicine
Management of a Type 1 Diabetic Pregnancy with Prior Myocardial Infarction
INTRODUCTION:
Cardiovascular disease is estimated to occur in 0.4% - 4.1% of pregnant women. In recent years, several papers have been published on Myocardial Infarction (MI) in pregnancy, however, less attention has been paid to the management of pregnant women with history of MI or stable angina pectoris.
CASE BACKGROUND:
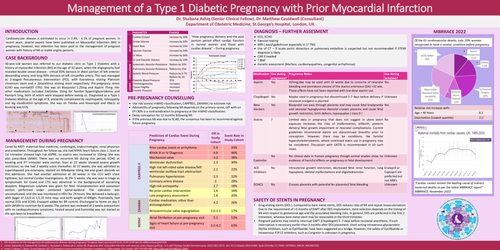
40-year-old woman was referred to our diabetic clinic as Type 1 Diabetes with a history of myocardial infarction (MI) at the age of 32 years, when the angiography had revealed double vessel disease - critical 60% stenosis in distal portion of left anterior descending artery, and long 90% stenosis of left circumflex artery. This was managed as 2-staged Percutaneous Intervention (PCI), with Everolimus eluting Platinum chromium stent and a Zotarolimus eluting stent respectively. Pre-pregnancy stress ECHO was normal(EF 57%). She was on Bisoprolol 1.25mg and Aspirin 75mg. Her other medications included Ezetimibe 10mg for familial hypertriglyceridemia and Ramipril 5mg, both of which were stopped before seeing us. Diagnosed as a Type 1 Diabetes Mellitus at the age of 8, presently complicated by nephropathy, retinopathy and leg claudication symptoms. She was on Tresiba and Novorapid and Hba1c at booking was 61%.
MANAGEMENT DURING PREGNANCY:
Cared by MDT: maternal-fetal medicine, cardiologist, endocrinologist, renal physician and anesthetist. Throughout her follow-up, she had NYHA heart failure class 1. Scan at 1st trimester showed high risk ASPRE, so aspirin was increased to 150mg. She was also prescribed LMWH. There was no recurrent MI during this period, ECHO at booking and 2nd trimester were normal. Scan at 22 weeks showed severe growth restriction, so she had 2 weekly scans thereafter. At 27 weeks, she was admitted as superimposed pre-eclampsia, started on Nifedipine 10mg bid and given steroids on this admission. She had another admission at 28 weeks in the CCU with chest tightness, but normal Cardiac Investigations. At 29+ 5 weeks, she was seen in triage as symptomatic for Covid and CTG was abnormal in the background of worsening dopplers. Magnesium sulphate was given for fetal neuroprotection and caesarean section performed under combined spinal-epidural. The operation was uncomplicated, and she was monitored in HDU for 24 hours. She delivered a baby girl, with Apgar of 2,6,9 at 1,5,10 mins resp. and birth weight of 690gm. Postnatally, had normal ECG and ECHO, Enalapril added for BP control. Discharged to home on day 5 with LMWH to continue for 6 weeks. The patient was reviewed at 2 weeks postpartum with no cardiopulmonary symptoms; healed wound and Ezetimibe was not started as she was keen to breastfeed.
PRE-PREGNANCY COUNSELLING:
DIAGNOSIS – FURTHER ASSESMENT: